Related Experiment Video
Updated: Aug 18, 2026


An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
Uterine and vaginal effects of unopposed ultralow-dose transdermal estradiol
Susan R Johnson1, Bruce Ettinger, Judith L Macer
1Department of Obstetrics and Gynecology, Roy J. and Lucille A. Carver College of Medicine, University of Iowa, Iowa City 52242, USA. susan-johnson@uiowa.edu

Objective:
To investigate uterine effects of unopposed ultralow-dose transdermal estradiol administered to postmenopausal women for 2 years.
Methods:
Postmenopausal women (n = 417), aged 60-80 years, with a uterus and with bone mineral density that was normal for age (z score >or=-2.0) were randomly assigned to receive unopposed transdermal estradiol (14 microg per day) or identical placebo patch. We evaluated effects on endometrial histology, vaginal bleeding, and vaginal epithelial cell maturation.
Results:
At baseline, estradiol and placebo groups were similar in age (67 +/- 5 years) and in median baseline serum estradiol level (4.8 pg/mL, interquartile range 2.7, 8.0 pg/mL). In the estradiol group, median estradiol level increased to 8.6 pg/mL, (interquartile range 4.4, 13.9 pg/mL, P < .001). In the estradiol group, focal atypical endometrial hyperplasia developed in 1 woman, and adenosarcoma of the uterus developed in 1 woman. The placebo group had no endometrial hyperplasia. Endometrial proliferation occurred in 8.5% of the estradiol group and in 1.1% of the placebo group (P = .06). Incidence of vaginal bleeding was 12.4% in the estradiol group and 8.6% in the placebo group (P = .3). Vaginal epithelial cells showed greater maturation in the estradiol group than in the placebo group (P < .001) but less than typically observed with standard doses of estrogen.
Conclusion:
During 2 years of treatment with ultralow-dose unopposed estradiol, treatment and placebo groups had similar rates of endometrial hyperplasia, endometrial proliferation, and vaginal bleeding. This therapy apparently causes little or no endometrial stimulation.
Level Of Evidence:
I.
Related Concept Videos
 01:21
Intrauterine Drug Delivery Systems
 01:22
Birth Control Methods
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:18
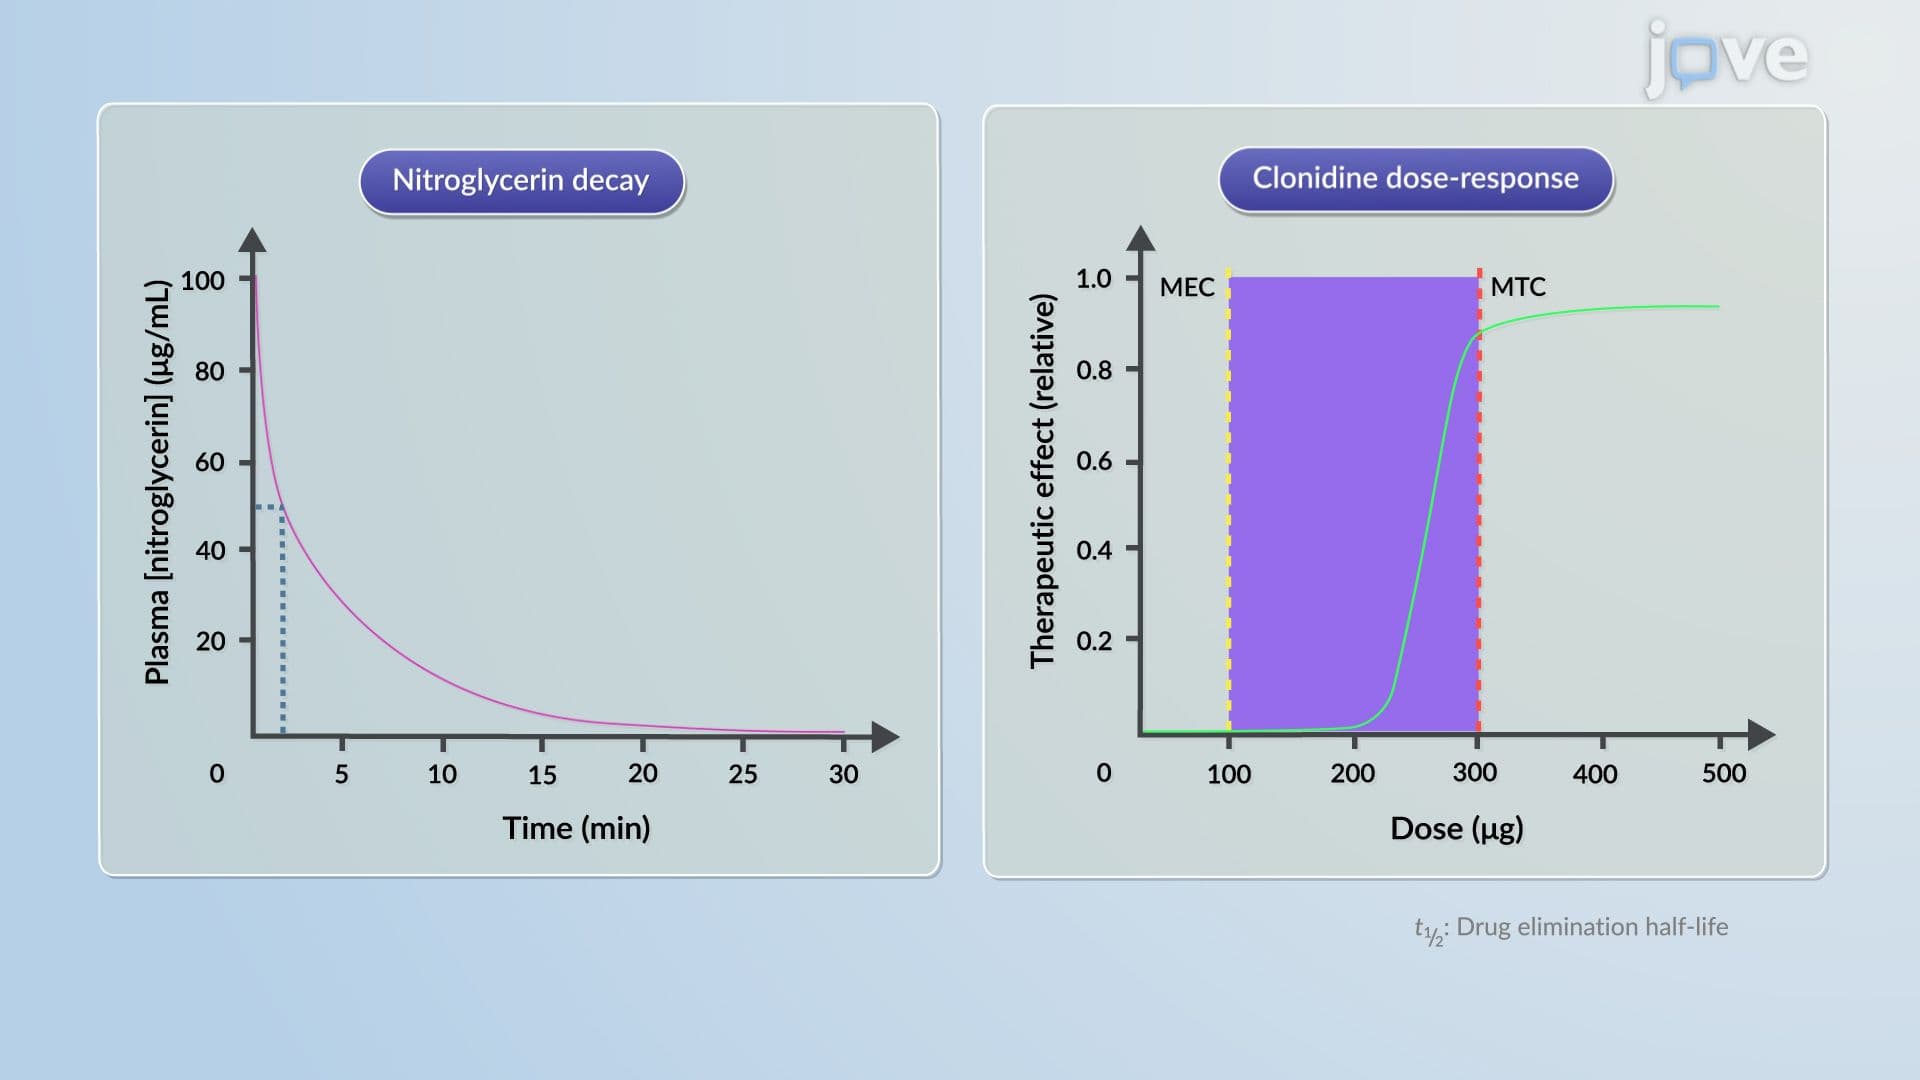
Transdermal Drug Delivery Systems
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:27
Ovarian Cycle