Related Experiment Video
Updated: Aug 18, 2026
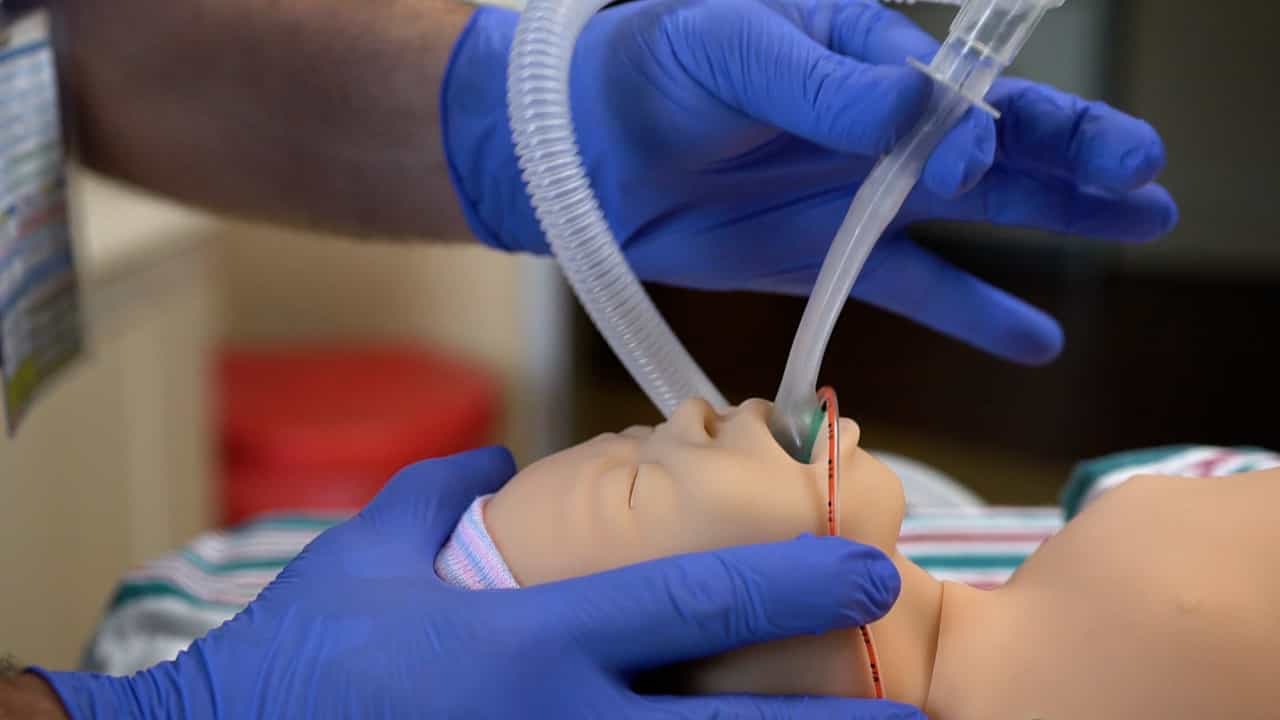

Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
Laryngeal oedema in neonatal apnoea and bradycardia syndrome (a pilot study)
Danièle Vermeylen1, Patricia Franco, Yves Hennequin
1Neonatal Intensive Care Unit, Erasmus Hospital, Free University of Brussels (ULB), Brussels, Belgium. dvermeyl@ulb.ac.be

Insights
Laryngeal edema may cause recurrent apneas, bradycardias, and desaturations in preterm infants. Corticosteroid treatment, diagnosed via fiberoptic endoscopy, effectively resolves these breathing events.
Area of Science:
- Neonatal Medicine
- Pediatric Pulmonology
- Otolaryngology
Background:
- Preterm infants often experience recurrent apneas, bradycardias, and desaturations (ABD) despite standard treatments.
- These events pose a risk for transient brain hypoxia and potential neurological injury.
- The underlying causes of persistent ABD in otherwise healthy preterm infants require further investigation.
Purpose of the Study:
- To investigate the role of laryngeal edema as a cause of recurrent ABD in preterm infants.
- To evaluate the efficacy of corticosteroid treatment for laryngeal edema-induced ABD.
- To assess the diagnostic utility of fiberoptic laryngeal endoscopy.
Main Methods:
- Twelve preterm infants with recurrent ABD underwent fiberoptic laryngeal endoscopy.
- Laryngeal examination was performed at a median postconceptional age of 34 weeks.
- Infants were treated with inhaled corticosteroids, with some also receiving oral dexamethasone.
Main Results:
- All infants presented with severe laryngeal edema, indicative of potential obstructive breathing.
- Corticosteroid treatment led to clinical improvement in all infants.
- Recurrence of ABD was observed in 25% of infants after dexamethasone cessation, with no immediate side effects noted.
Conclusions:
- Laryngeal edema is a potential cause of recurrent ABD in preterm newborns.
- Esophageal reflux and feeding tubes may contribute to laryngeal edema.
- Atraumatic fiberoptic fibroscopy is a viable diagnostic tool, and corticosteroids offer an effective treatment.
Purpose:
Some preterm infants in general good health continue to present recurrent apnoeas, bradycardias and desaturations (ABD) despite usual treatments. These events may lead to transitory brain hypoxia and to further neurological injury. The purpose of this study has been to evaluate the role of laryngeal oedema in this symptomatology and to assess corticoid treatment.
Method:
Twelve preterm babies born at a median age of 28.5 weeks (range: 26-35 weeks) already showed signs of ABD at a median age of life of 28.5 days (range: 9-80 days). Fiberoptic laryngeal endoscopy was performed on these babies at a median postconceptional age of 34 weeks (range: 31-38 weeks) to detect a possible involvement of the larynx in their ABD.
Results:
Each patient presented a severe laryngeal oedema compatible with potential obstructive breathing. Half of the cohort (n=6) received inhaled corticosteroids initiated with a short oral dexamethasone treatment for 3 to 5 days (group 1). All the babies improved. The other half (n=6) received only an inhaled topic corticosteroid treatment (group 2). Four of the six babies improved and two needed oral dexamethasone. Laryngoscopic endoscopy was carried out after 1 week of treatment. The picture corresponded with clinical improvement. Recurrence of ABD occurred in 3/12 (25%) of the babies after stopping dexamethasone. No immediate side effects of the procedure or the treatment were observed.
Conclusion:
Laryngeal oedema may be a cause of ABD in preterm newborns. It may arise from oesophageal reflux and/or presence of the feeding tube. It can be diagnosed by atraumatic fiberoptic fibroscopy and successfully treated with corticosteroids.

Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:10
Atelectasis II: Pathophysiology
 01:26
Respiratory Volumes and Capacities I
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: