Related Experiment Video
Updated: Aug 18, 2026


Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Unchanged hypovitaminosis D and secondary hyperparathyroidism in morbid obesity after bariatric surgery
Juan Ybarra1, Joan Sánchez-Hernández, Ignasi Gich
1Department of Endocrinology, Hospital de Sant Pau, Barcelona, Spain. juanybarra@hotmail.com

Background:
Morbidly obese patients have been reported to present with vitamin D insufficiency and secondary hyperparathyroidism. We assessed whether bariatric surgery alters the 25-hydroxyvitamin D (calcidiol) and intact parathyroid hormone (iPTH) levels in patients presenting with morbid obesity.
Methods:
A cross-sectional survey was conducted on 144 patients of whom 80 had not undergone bariatric surgery, while 64 had bariatric surgery at a mean of 36 months previously. Calcidiol levels were defined as being normal (>50 nmol/L), insufficient (2550 nmol/L) and deficient (<25 nmol/L). Mild secondary hyperparathyroidism was defined as iPTH >7.3 pmol/L with simultaneous normal values for creatinine, calcium and phosphorus.
Results:
80% of the patients presented low vitamin D levels and mild secondary hyperparathyroidism. Previous surgery or the presence of diabetes did not influence calcidiol levels. Corrected serum calcium, phosphorus, alkaline phosphatase, iPTH and Calcidiol were similar between subjects with and without surgery.
Conclusions:
Vitamin D deficient states with secondary hyperparathyroidism in the morbidly obese precede and are not significantly affected by bariatric surgery. Hypovitaminosis D with secondary hyperparathyroidism due to low calcidiol bio-availability should be added to the crowded list of sequelae of morbid obesity. While further studies are warranted, it seems advisable to support vitamin D supplementation in the morbidly obese population.
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:27
Hyperthyroidism II: Pathophysiology
 00:59
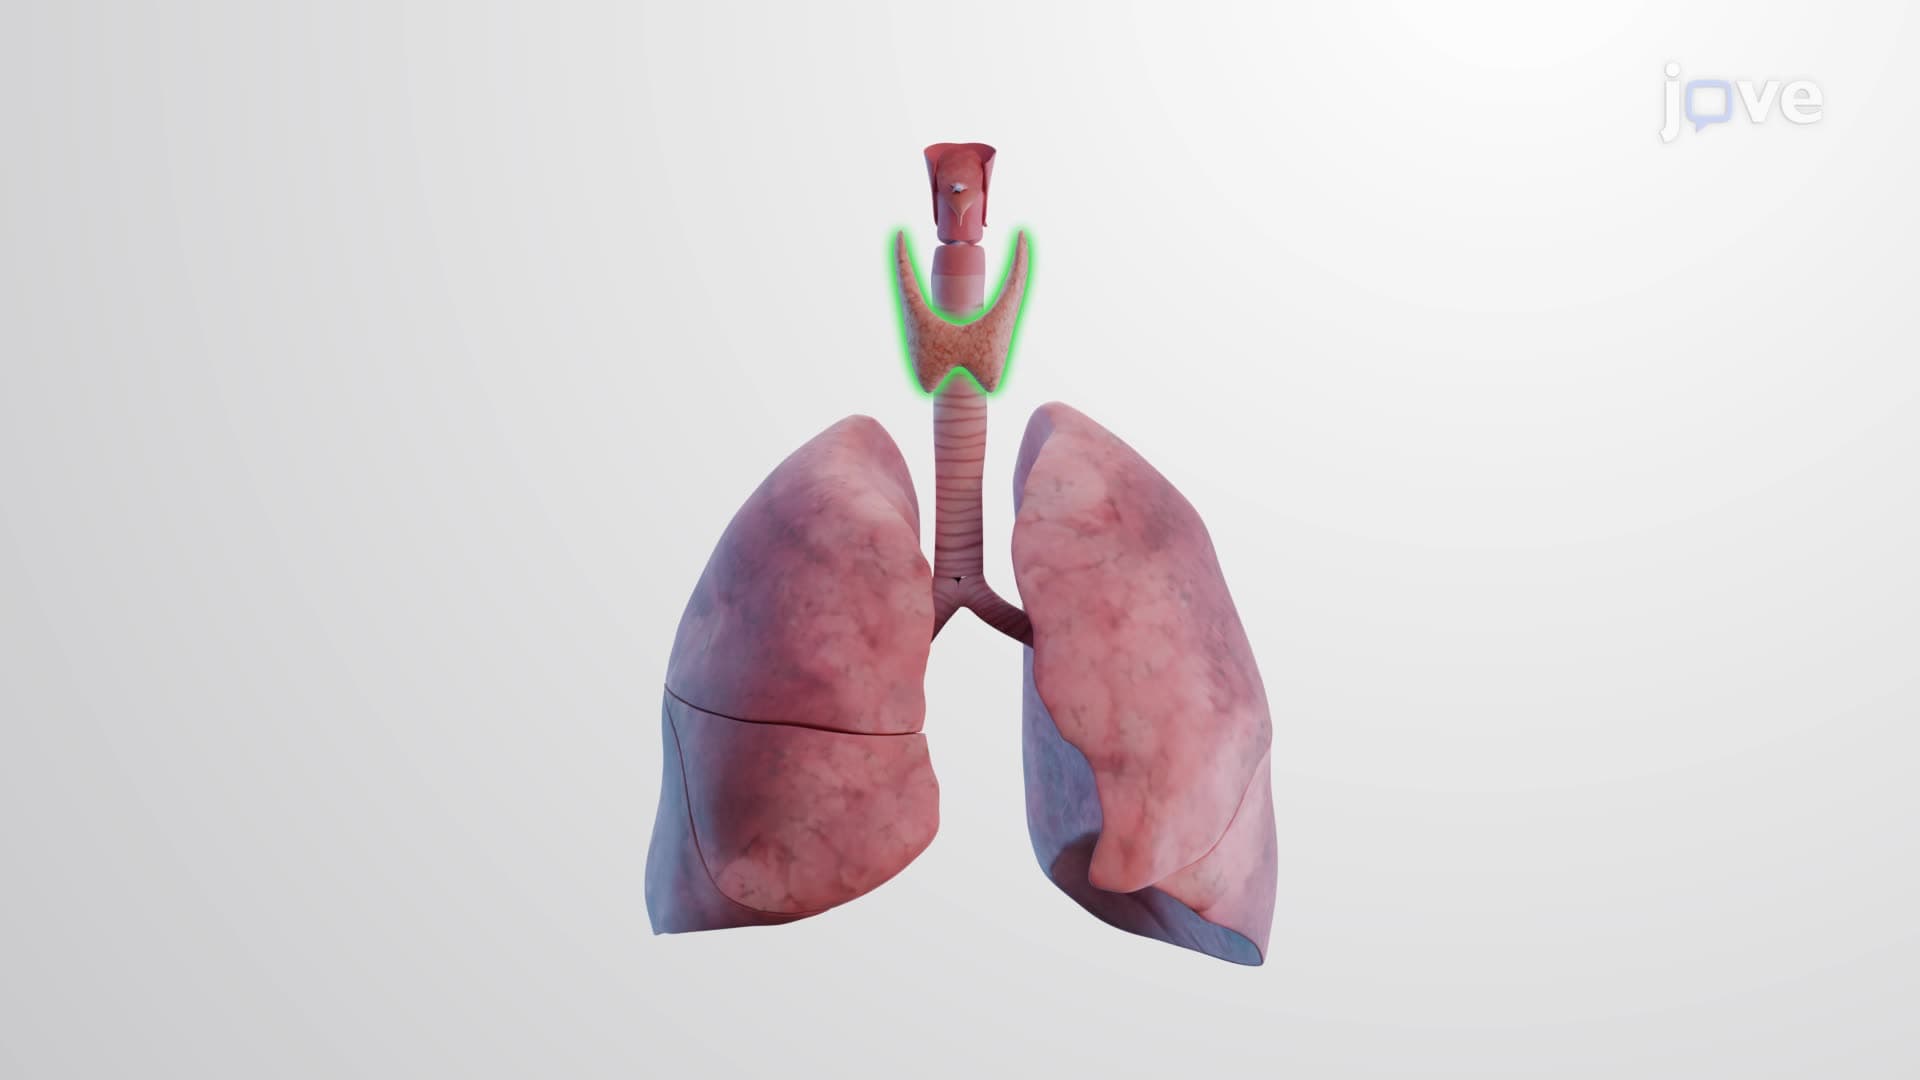
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:21
Skeleton and Calcium Homeostasis
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...