Related Experiment Video
Updated: Jul 31, 2026
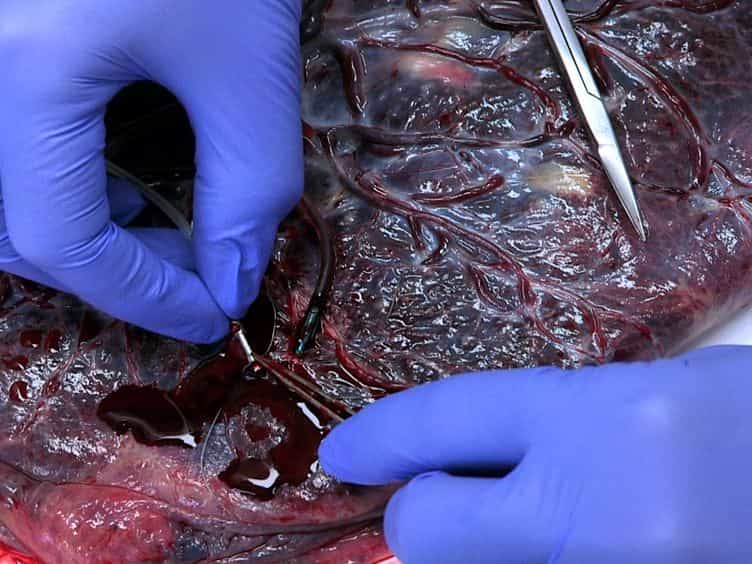
Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Fetoplacental transport and utilization of amino acids in IUGR--a review
T R H Regnault1, J E Friedman, R B Wilkening
1Perinatal Research Center, Department of Pediatrics, Division of Perinatal Medicine, University of Colorado Health Sciences Center, F441, Aurora, CO 80045, USA. tim.regnault@uchsc.edu

Abstract:
Amino acids have multiple functions in fetoplacental development. The supply of amino acids to the fetus involves active transport across and metabolism within the trophoblast. Transport occurs through various amino acid transport systems located on both the maternal and fetal facing membranes, many of which have now been documented to be present in rat, sheep and human placentas. The capacity of the placenta to supply amino acids to the fetus develops during pregnancy through alterations in such factors as surface area and specific time-dependent transport system expression. In intrauterine growth restriction (IUGR), placental surface area and amino acid uptakes are decreased in human and experimental animal models. In an ovine model of IUGR, produced by hyperthermia-induced placental insufficiency (PI-IUGR), umbilical oxygen and essential amino acid uptake rates are significantly reduced in the most severe cases in concert with decreased fetal growth. These changes indicate that severe IUGR is likely associated with a shift in amino acid transport capacity and metabolic pathways within the fetoplacental unit. After transport across the trophoblast in normal conditions, amino acids are actively incorporated into tissue proteins or oxidized. In the sheep IUGR fetus, however, which is hypoxic, hypoglycemic and hypoinsulinemic, there appear to be net effluxes of amino acids from the liver and skeletal muscle, suggesting changes in amino acid metabolism. Potential changes may be occurring in the insulin/IGF-I signaling pathway that includes decreased production and/or activation of specific signaling proteins leading to a reduced protein synthesis in fetal tissues. Such observations in the placental insufficiency model of IUGR indicate that the combination of decreased fetoplacental amino acid uptake and disrupted insulin/IGF signaling in liver and muscle account for decreased fetal growth in IUGR.

Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:07
Teratogenicity
 01:29
Drug Distribution: Plasma Protein Binding
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism