Neurogenic dysphagia resulting from Chiari malformations
Related Experiment Video
Updated: Aug 17, 2026
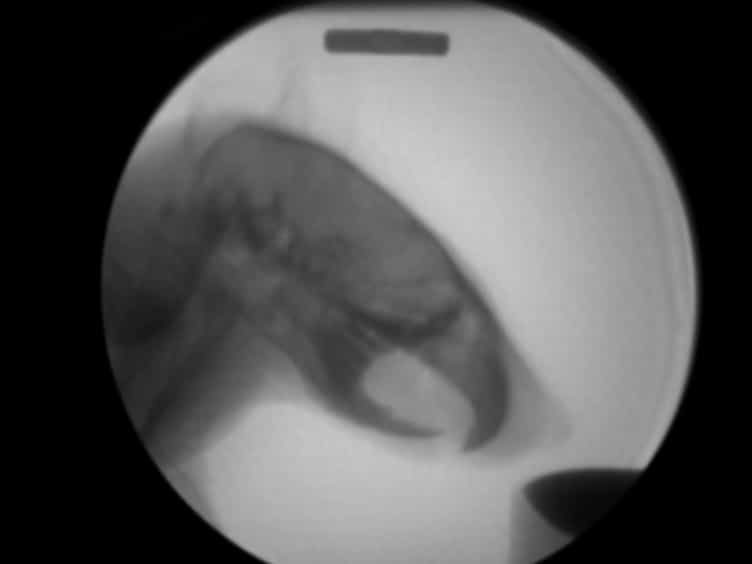
Adapting Human Videofluoroscopic Swallow Study Methods to Detect and Characterize Dysphagia in Murine Disease Models
Published on: March 1, 2015
I F Pollack1, D Pang, S Kocoshis
1Neurological Surgery, University of Pittsburgh School of Medicine, Pennsylvania.

Abstract:
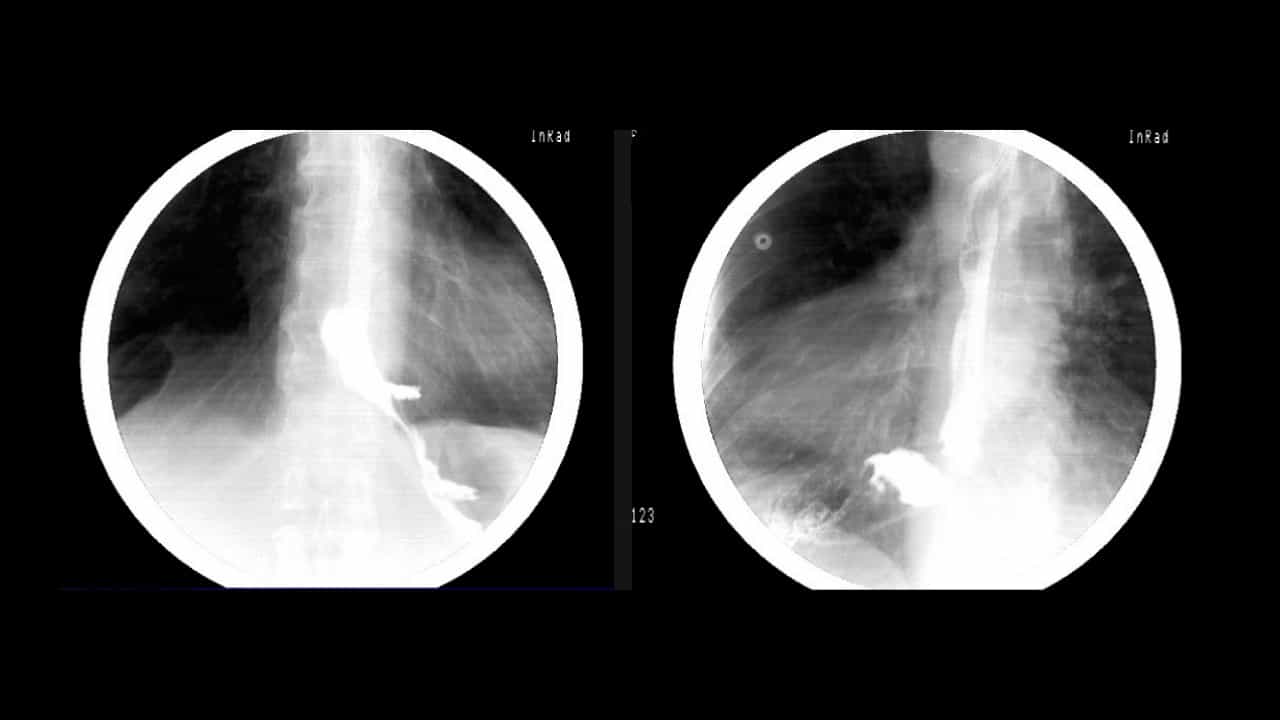
Between 1980 and 1989, 15 of 46 patients (11 children, 4 adults) who underwent suboccipital craniectomy and cervical laminectomy for symptomatic Chiari malformations presented with manifestations of neurogenic dysphagia. Each of these patients had normal swallowing function before the development of dysphagic symptoms. Dysphagia was progressive in all 15 and, in most cases, preceded the onset of other severe brain stem signs. The rate of symptom progression varied depending on the age of the patient. Whereas the six infants (all Chiari II) deteriorated rapidly after the onset of initial symptoms, the five older children (two Chiari I, three Chiari II) and four adults (all Chiari I) showed a more gradual deterioration. In 11 patients with severe dysphagia, barium video esophagograms, pharyngoesophageal motility studies, continuous esophageal pH monitoring, and appropriate scintigraphic studies were useful in defining the scope of the swallowing impairment and determining whether perioperative nasogastric or gastrostomy feedings, gastric fundoplication, and/or tracheostomy were needed to maintain adequate nutrition and avoid aspiration. These patients all had widespread dysfunction of the swallowing mechanism, with a combination of diffuse pharyngoesophageal dysmotility, cricopharyngeal achalasia, nasal regurgitation, tracheal aspiration, and gastroesophageal reflux. The pathophysiology of these swallowing impairments and their relation to the hindbrain malformation is discussed. Postoperative outcome with regard to swallowing function correlated with the severity of preoperative symptoms. The four patients with mild dysphagia showed rapid improvement in swallowing function after surgery. Seven patients with more severe impairment but without other signs of severe brain stem compromise, such as central apnea or complete bilateral vocal cord paralysis, also improved, albeit more slowly. In contrast, the outcome in the four patients who developed other signs of severe brain stem dysfunction before surgery was poor. Early recognition of neurogenic dysphagia and expeditious intervention are therefore crucial in ensuring a favorable neurological outcome.

Related Concept Videos
 01:30
Neurulation
 01:20
Gastrointestinal Motility Disorders
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:27
Esophageal Achalasia
 01:25
Hiatal Hernia
 01:11
Pyloric Obstruction