Related Experiment Video
Updated: Aug 18, 2026


Role of Diffusion MRI Tractography in Endoscopic Endonasal Skull Base Surgery
Published on: July 5, 2021
Sixth and tenth nerve palsy secondary to pseudomonas infection of the skull base
Sonalee Kulkarni1, Andrew Lee, John H Lee
1Department of Ophthalmology, University of Iowa Hospitals and Clinics, 200 Hawkins Drive PFP, Iowa City, IA 52242, USA. andrew-lee@uiowa.edu

Purpose:
To describe skull base osteomyelitis, an uncommon complication of chronic otitis media in the post-antibiotic era, as a cause for diplopia.
Design:
Case report.
Methods:
The records of a patient with skull base osteomyelitis were reviewed.
Results:
A patient presented with a sixth nerve palsy and tenth nerve palsy. Magnetic resonance imaging, bone scan, and gallium scan were helpful in establishing the diagnosis. Cultures grew Pseudomonas. The treatment required long-term intravenous antibiotics.
Conclusions:
Pseudomonas skull-based osteomyelitis can produce a sixth nerve palsy as a result of the involvement of the clivus. Although uncommon in the post-antibiotic era, early recognition, appropriate diagnostic testing, and aggressive systemic antibiotic treatment might prevent permanent neurologic sequel.
Insights
Skull base osteomyelitis, a rare complication of chronic otitis media, can cause double vision (diplopia) due to nerve palsies. Early diagnosis and treatment are crucial to prevent lasting neurological damage.
Area of Science:
- Otolaryngology
- Neurology
- Infectious Diseases
Background:
- Skull base osteomyelitis is an uncommon complication of chronic otitis media.
- This condition can manifest with neurological deficits, including cranial nerve palsies.
- Its occurrence in the post-antibiotic era highlights the need for continued vigilance.
Observation:
- A case report details a patient presenting with diplopia secondary to sixth and tenth cranial nerve palsies.
- Diagnostic imaging, including MRI, bone scan, and gallium scan, was instrumental in identifying skull base osteomyelitis.
- Cultures confirmed Pseudomonas as the causative pathogen.
Findings:
- Pseudomonas skull base osteomyelitis can involve the clivus, leading to sixth nerve palsy.
- The diagnosis was confirmed through a combination of clinical presentation and advanced imaging techniques.
- Treatment involved prolonged intravenous antibiotic therapy.
Implications:
- This case underscores that skull base osteomyelitis remains a potential cause of diplopia, even in the modern antibiotic era.
- Prompt recognition and comprehensive diagnostic workup are essential for effective management.
- Aggressive antibiotic treatment may prevent permanent neurological sequelae in patients with skull base osteomyelitis.
Related Concept Videos
 01:22
Bacterial Meningitis I: Introduction
 01:26
Bacterial Meningitis II: Pathophysiology
 01:26
Brain Abscess l: Introduction
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology
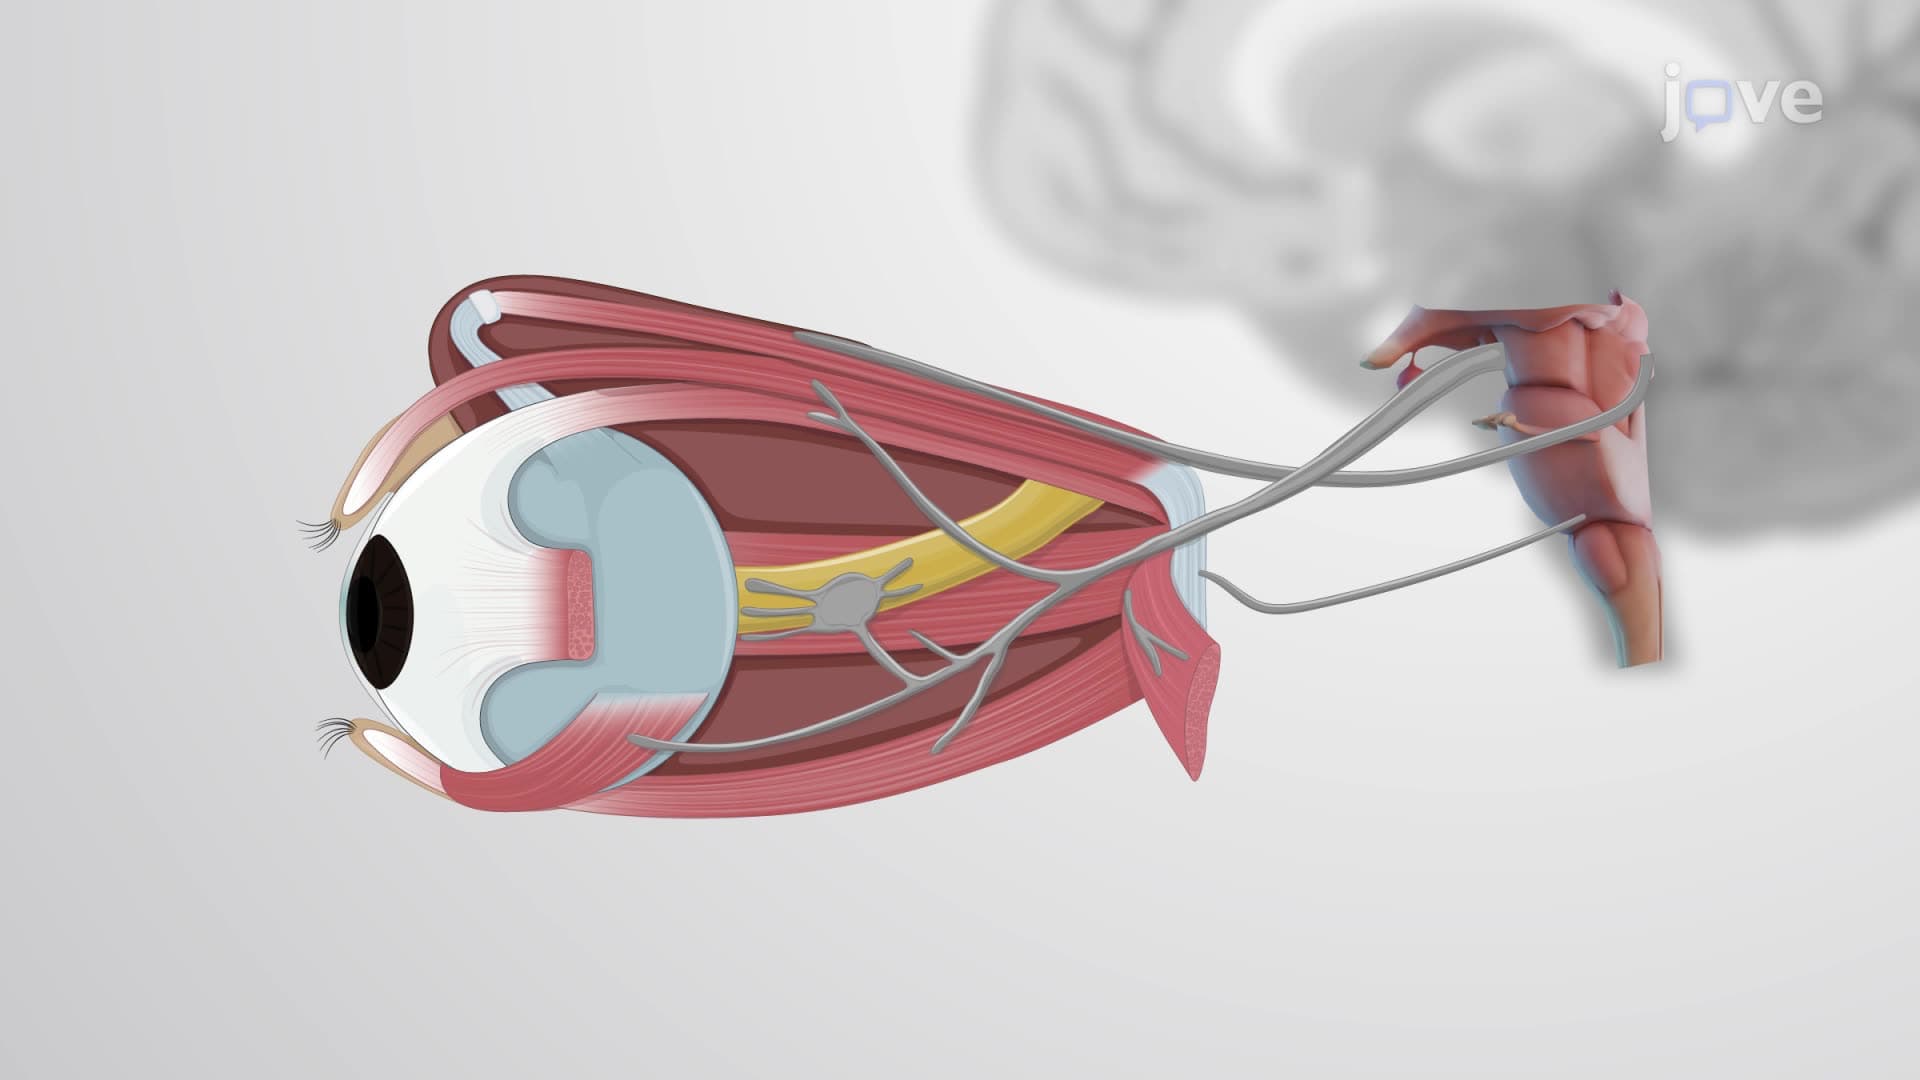 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...