Related Experiment Video
Updated: Aug 18, 2026
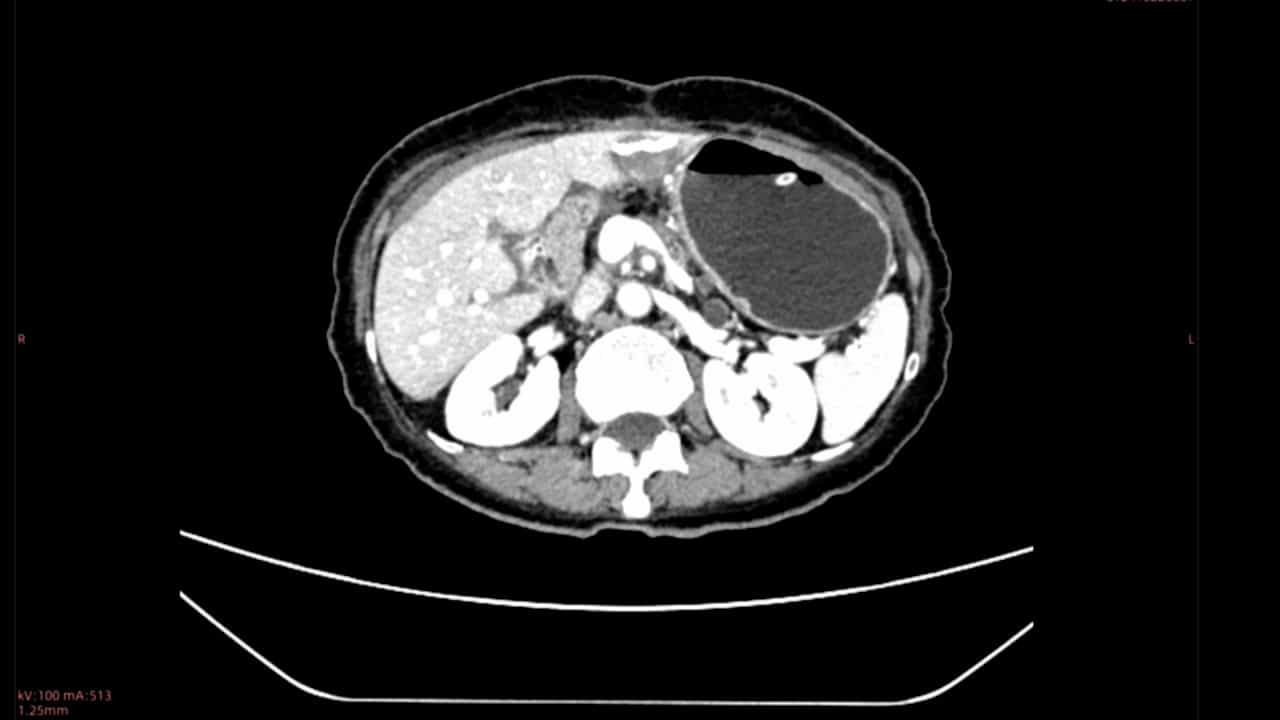

Application of Simplified Stent-bridging Pancreaticogastrostomy in Open Pancreaticoduodenectomy
Published on: March 17, 2026
Gastroparesis after a pylorus-preserving pancreatoduodenectomy
1Department of Surgery and Oncology, Graduate School of Medical Sciences, Kyushu University, Fukuoka, 812-8582, Japan.

Abstract:
Gastroparesis after a pylorus-preserving pancreatoduodenectomy has two main aspects, namely early gastric stasis and subsequent postprandial delayed gastric emptying. Early gastric stasis producing an excessive amount of gastric juice during the immediate postoperative period might be caused by the absence of phase III activity of the gastric migrating motor complex (MMC), and such symptoms usually subside within a month or two. Subsequent postprandial delayed gastric emptying leading to belching, fullness of the stomach, nausea, and vomiting after the resumption of oral intake normally continues for up to 6 months before complete recovery. There are many possible mechanisms to explain these phenomena. The early recovery of phase III of the MMC does not necessarily predict an early relief of postprandial delayed gastric emptying, thus suggesting that these two phenomena are caused by various mechanisms. The phenomena, mechanisms, and treatment strategies for gastroparesis after pylorus-preserving pancreatoduodenectomy are described in this review.
Related Concept Videos
 01:11
Pyloric Obstruction
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: