Related Experiment Video
Updated: Aug 18, 2026
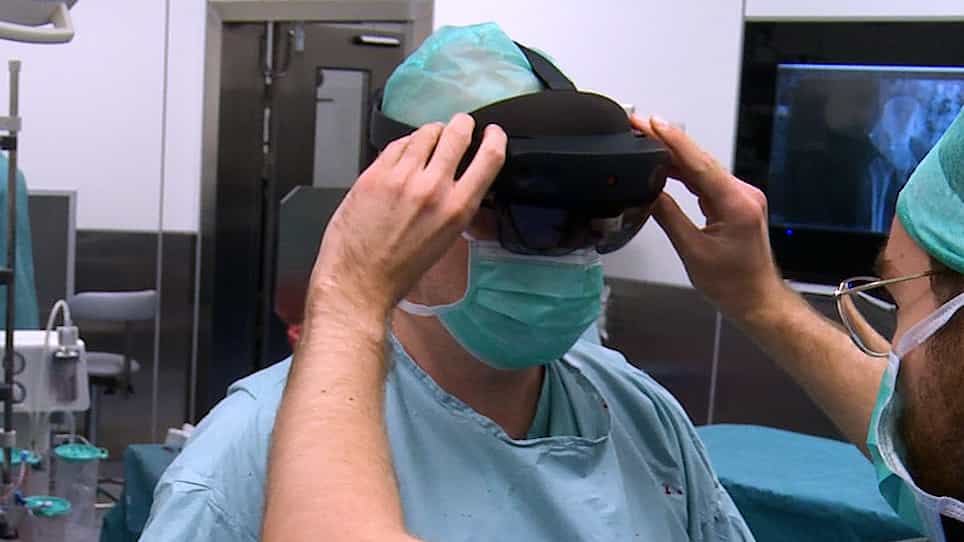

The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Ilizarov hip reconstruction for the late sequelae of infantile hip infection
S Robert Rozbruch1, Dror Paley, Anil Bhave
1International Center for Limb Lengthening, Rubin Institute for Advanced Orthopedics, Sinai Hospital of Baltimore, Maryland, USA.

Insights
Ilizarov hip reconstruction effectively treats infantile hip infection sequelae, improving limb length discrepancy and gait. This surgical technique offers significant clinical and radiographic improvements in young patients.
Area of Science:
- Orthopedic surgery
- Pediatric orthopedics
- Limb reconstruction
Background:
- Infantile hip infection can lead to severe deformities like femoral head absence and limb length discrepancy.
- These sequelae often result in abnormal gait and pain, significantly impacting a child's quality of life.
Purpose of the Study:
- To evaluate the efficacy of Ilizarov hip reconstruction in treating sequelae of infantile hip infection.
- To assess the technique's ability to correct deformities and improve functional outcomes.
Main Methods:
- Retrospective review of eight patients with Type-IV or V hip deformity post-infantile hip infection.
- Ilizarov hip reconstruction involving proximal femoral osteotomy and distal femoral osteotomy with gradual distraction.
- Clinical and radiographic evaluation, including gait analysis and modified Harris hip score.
Main Results:
- Significant improvement in lower-extremity length discrepancy (4.6 cm to 0.7 cm).
- Enhanced modified Harris hip scores (51 to 73) and improved gait parameters (stance-time asymmetry, ground-reaction force).
- Successful correction of pelvic mechanical axis and limb alignment.
Conclusions:
- Ilizarov hip reconstruction is a successful treatment for correcting gait abnormalities and limb length discrepancies in children with sequelae of infantile hip infection.
- Potential for proximal osteotomy site remodeling and recurrent length discrepancy necessitates monitoring in young patients.
Background:
The late sequelae of infantile hip infection include absence of the femoral head and neck, proximal migration of the femur, lower-extremity length discrepancy, abnormal gait, and pain. The Ilizarov hip reconstruction includes an acute valgus and extension osteotomy at the proximal part of the femur combined with gradual distraction for realignment and lengthening at a second, more distal, femoral osteotomy. The purpose of this study was to determine whether this technique can successfully treat the sequelae of infantile hip infection.
Methods:
We performed a retrospective review of a series of eight consecutive patients with a Type-IV or V hip deformity, according to the classification system of Hunka et al., after an infantile hip infection. The patients' mean age at surgery was 11.2 years. All hips were unstable, with a mean of 3.8 cm of proximal migration. A mean valgus angulation of 44 degrees and a mean extension angulation of 19 degrees were created with the proximal osteotomies. Distal femoral lengthening averaged 5.7 cm, and distal femoral varus angular correction averaged 10 degrees. The mean time in the Ilizarov frame was 4.7 months. Outcomes were evaluated clinically and radiographically. The clinical evaluation included gait analysis and the use of a modified Harris hip score.
Results:
At the time of follow-up, at a mean of five years, the mean lower-extremity length discrepancy had improved from 4.6 cm preoperatively to 0.7 cm. The mean modified Harris hip score had improved from 51 points to 73 points (p = 0.007). All extremities were well aligned, with a mean pelvic mechanical axis angle of 89 degrees. The mean deviation of the mechanical axis was 2 mm in a lateral direction. The mean stance-time asymmetry improved from 16% to 5.4% (p = 0.0037), and the mean ground-reaction force (second peak) improved from 102% of body weight to 122% of body weight (p = 0.0005).
Conclusions:
The Ilizarov hip reconstruction can successfully correct a Trendelenburg gait and simultaneously restore knee alignment and correct lower-extremity length discrepancy. When the procedure is performed on a young patient, remodeling of the proximal osteotomy site and development of lower-extremity length discrepancy should be expected and the procedure may need to be repeated.