Related Experiment Video
Updated: Jul 9, 2026


Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
Patterns of saphenous reflux in women with primary varicose veins
Carlos Alberto Engelhorn1, Ana Luiza V Engelhorn, Maria Fernanda Cassou
1Santa Casa de Misericordia, Pontificia Universidade Catolica do Paraná, Brazil.

Objective:
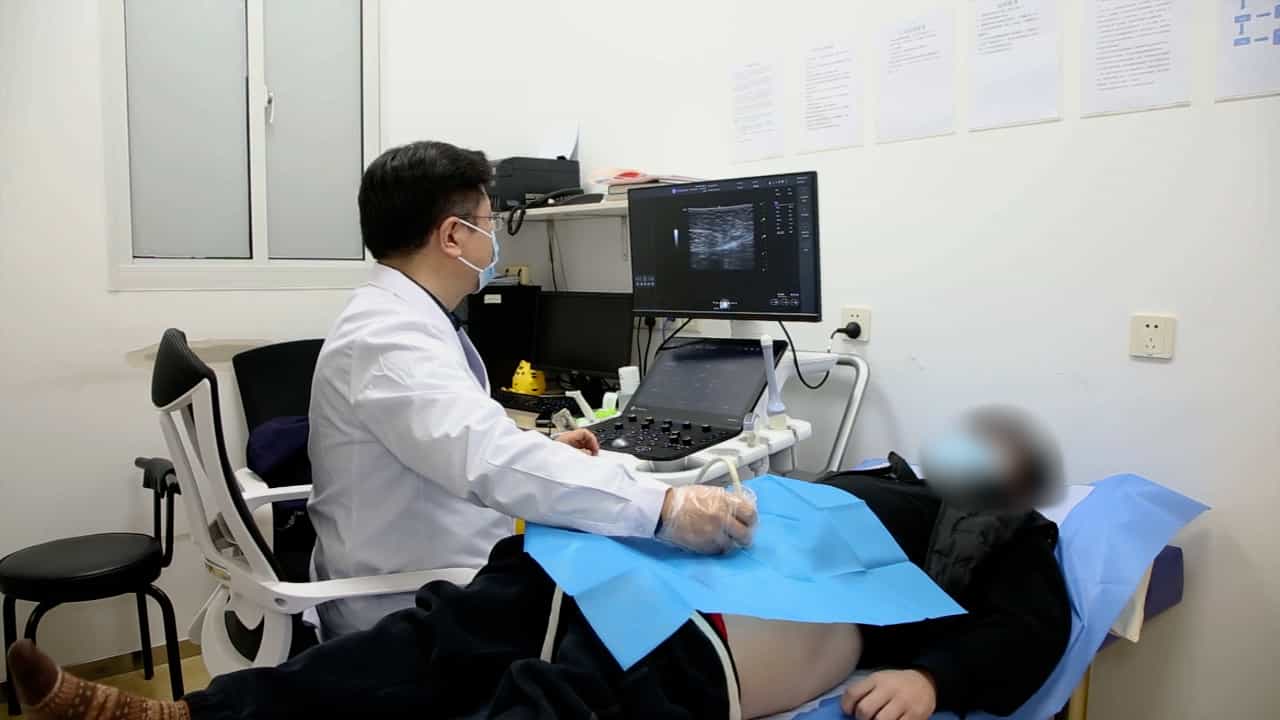
Varicose veins have been linked to great saphenous vein (GSV) reflux and in particular, with reflux at the saphenofemoral junction (SFJ). Early stages of disease, however, may be associated with limited, localized reflux in segments of the GSV and/or small saphenous vein (SSV). Ultrasound mapping of saphenous veins was performed to determine patterns of GSV and SSV reflux in women with simple, primary varicose veins.
Methods:
Ultrasound mapping was performed prospectively in 590 extremities of 326 women with varicose veins (CEAP C 2 class) but without edema, skin changes, or ulcers (C 3 to C 6 ). Average age was 42 +/- 13 (SD) years (range, 8 to 87). Patterns of GSV and SSV reflux, obtained in the upright position, were classified as I: perijunctional, originating from the SFJ or saphenopopliteal junction (SPJ) tributaries into the GSV or SSV; II: proximal, from the SFJ or SPJ to a tributary or perforating vein above the level of the malleoli; III: distal, from a tributary or perforating vein to the paramalleolar GSV or SSV; IV: segmental, from a tributary or perforating vein to another tributary or perforating vein above the malleoli; V; multisegmental, if two or more distinct refluxing segments were detected; and VI: diffused, involving the entire GSV or SSV from the SFJ or SPJ to the malleoli.
Results:
Reflux was detected in 472 extremities (80%): 100 (17%) had reflux in both the GSV and SSV, 353 (60%) had GSV reflux only, and 19 (3%) had SSV reflux only, for a total prevalence of 77% at the GSV and 20% at the SSV. The most common pattern of GSV reflux was segmental (types IV and V) in 342 (58%) of 590; either one segment in 213 (36%) or more than one segment with competent SFJ in 99 (17%), or incompetent SFJ in 30 (5%), followed by distal GSV reflux (type III) in 65 (11%), proximal GSV reflux (type II) in 32 (5%), diffused throughout the entire GSV (type VI) in 10 (2%), and perijunctional (type I) in 4 (<1%). GSV refluxing segments were noted in the SFJ in 72 (12%) and in the thigh in 220 (37%), and leg (or both) in 345 (58%).
Conclusions:
The high prevalence of reflux justifies ultrasound mapping of the saphenous veins in women with primary varicose veins. Correction of SFJ reflux, however, may be needed in

Related Concept Videos
 01:15
Veins of Lower Limbs
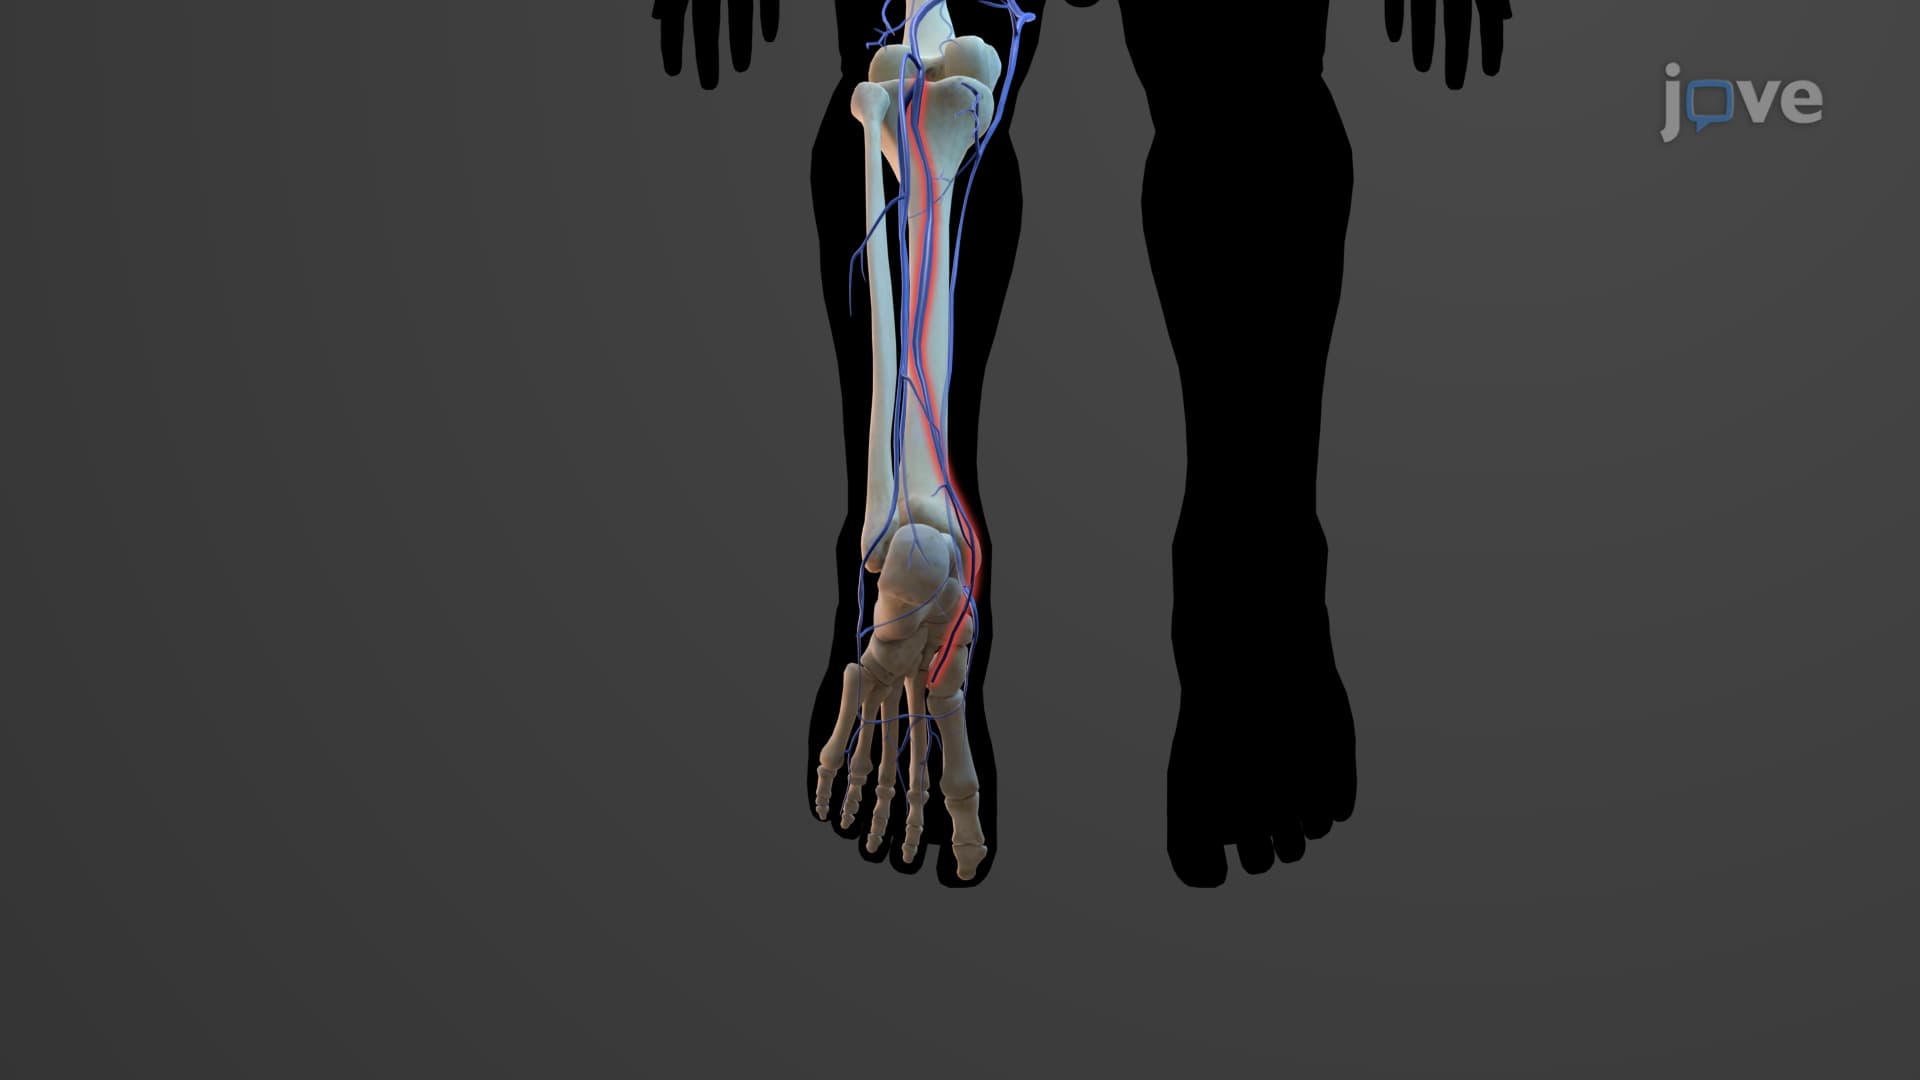
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...
 01:24
Esophageal Varices-I: Introduction
 01:26
Varicose Veins I: Introduction
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies