Related Experiment Video
Updated: Aug 18, 2026
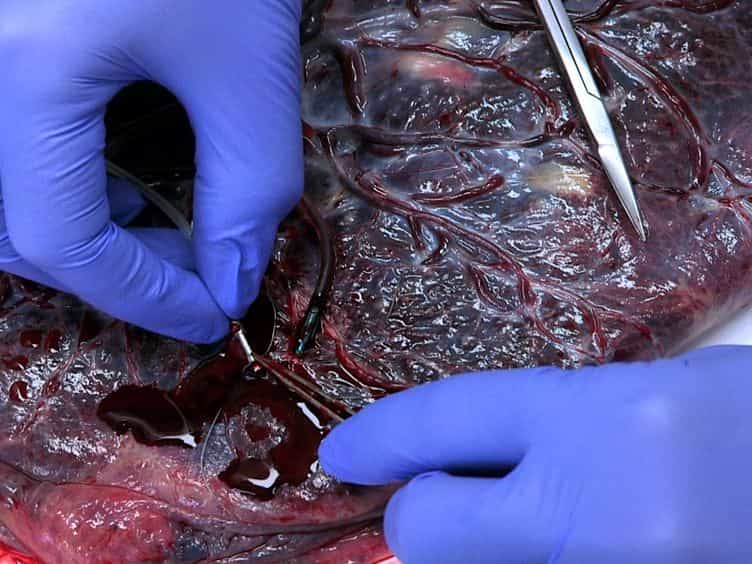
Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Role of P-glycoprotein in transplacental transfer of methadone
Tatiana Nanovskaya1, Ilona Nekhayeva, Nedra Karunaratne
1Department of Obstetrics & Gynecology, University of Texas Medical Branch, 301 University Blvd., Galveston, TX 77555-0587, USA.

Methadone is the therapeutic agent of choice for treatment of the pregnant opiate addict. However, little is known on the factors affecting its concentration in the fetal circulation during pregnancy and how it might relate to neonatal outcome. Therefore, a better understanding of the function of placental metabolic enzymes and transporters should add to the knowledge of the role of the tissue in the disposition of methadone and its relation to neonatal outcome. We hypothesized that the expression and activity of the placental efflux transporter P-glycoprotein (P-gp) would affect the transfer of methadone to the fetal circulation. Data obtained utilizing dual perfusion of placental lobule and monolayers of Be-Wo cell line indicated that methadone is extruded by P-gp. Transfer of methadone to the fetal circuit was increased by 30% in the presence of the P-gp inhibitor GF120918 while the transfer of paclitaxel, a typical substrate of the glycoprotein, was increased by 50%. In the Be-Wo cell line, methadone and paclitaxel uptake was also increased in the presence of the P-gp inhibitor cyclosporin A. Moreover, the expression of P-gp in placental brush-border membranes varied between term placentas. Taken together, these data strongly suggest that the concentration of methadone in the fetal circulation is affected by the expression and activity of P-gp. It is reasonable to speculate that placental disposition of methadone affects its concentration in the fetal circulation. If true, this may also be directly related to the incidence and intensity of neonatal abstinence syndrome (NAS).
Methadone is the therapeutic agent of choice for treatment of the pregnant opiate addict. However, little is known on the factors affecting its concentration in the fetal circulation during pregnancy and how it might relate to neonatal outcome. Therefore, a better understanding of the function of placental metabolic enzymes and transporters should add to the knowledge of the role of the tissue in the disposition of methadone and its relation to neonatal outcome. We hypothesized that the expression and activity of the placental efflux transporter P-glycoprotein (P-gp) would affect the transfer of methadone to the fetal circulation. Data obtained utilizing dual perfusion of placental lobule and monolayers of Be-Wo cell line indicated that methadone is extruded by P-gp. Transfer of methadone to the fetal circuit was increased by 30% in the presence of the P-gp inhibitor GF120918 while the transfer of paclitaxel, a typical substrate of the glycoprotein, was increased by 50%. In the Be-Wo cell line, methadone and paclitaxel uptake was also increased in the presence of the P-gp inhibitor cyclosporin A. Moreover, the expression of P-gp in placental brush-border membranes varied between term placentas. Taken together, these data strongly suggest that the concentration of methadone in the fetal circulation is affected by the expression and activity of P-gp. It is reasonable to speculate that placental disposition of methadone affects its concentration in the fetal circulation. If true, this may also be directly related to the incidence and intensity of neonatal abstinence syndrome (NAS).
More Related Videos

Related Concept Videos
 01:16
Pharmacogenetics of Drug Transporters: P-Glycoprotein and Solute Carrier Transporters
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:06
Carrier-Mediated Transport
Active transport involves two types of membrane-spanning transporters: uptake and efflux. Uptake transporters are expressed in the small...
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:17
Phase II Reactions: Methylation Reactions
The mechanism of methylation unfolds in two stages. The first stage sees a methyltransferase enzyme facilitating the transfer of a methyl group from S-adenosylmethionine (SAM) to the substrate, forming S-adenosylhomocysteine (SAH). The second stage involves further metabolism of SAH into homocysteine, which can be recycled...