Related Experiment Video
Updated: Aug 18, 2026

5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
Altered renal elimination of organic anions in rats with chronic renal failure
Adriana Mónica Torres1, Myriam Mac Laughlin, Angélica Muller
1Farmacología, Facultad de Ciencias Bioquímicas y Farmacéuticas, Universidad Nacional de Rosario, CONICET, Argentina. adtorres@fbioyf.unr.edu.ar

Abstract:
The progress of chronic renal failure (CRF) is characterized by the development of glomerular and tubular lesions. However, little is known about the expression of organic anions renal transporters. The objective of this work was to study, in rats with experimental CRF (5/6 nephrectomy), the expression of the organic anion transporter 1 (OAT1) and organic anion transporter 3 (OAT3) and their contribution to the pharmacokinetics and renal excretion of p-aminohippurate (PAH). Two groups of animals were used: Sham and CRF. Six months after surgery, systolic blood pressure and plasma creatinine concentrations were significantly higher in CRF groups. CRF rats showed a diminution in: the filtered, secreted and excreted load of PAH; the systemic clearance of PAH; the renal OAT1 expression; and the renal Na-K-ATPase activity. No remarkable modifications were observed in the OAT3 expression from CRF kidneys. The diminution in the systemic depuration and renal excretion of PAH may be explained by the decrease in its filtered and secreted load. The lower OAT1 expression in remnant renal mass of CRF rats or/and the lower activity of Na-K-ATPase might justify, at least in part, the diminished secreted load of this organic anion.
Insights
Chronic renal failure (CRF) in rats reduced organic anion transporter 1 (OAT1) expression and Na-K-ATPase activity, impairing p-aminohippurate (PAH) excretion. OAT3 expression remained unchanged, suggesting OAT1
Area of Science:
- Nephrology
- Renal Physiology
- Pharmacokinetics
Background:
- Chronic renal failure (CRF) involves glomerular and tubular damage.
- Organic anion renal transporter expression in CRF is poorly understood.
Purpose of the Study:
- Investigate organic anion transporter 1 (OAT1) and organic anion transporter 3 (OAT3) expression in experimental CRF.
- Determine their role in p-aminohippurate (PAH) pharmacokinetics and renal excretion.
Main Methods:
- Created experimental CRF in rats via 5/6 nephrectomy.
- Compared CRF rats to sham-operated controls six months post-surgery.
- Measured systolic blood pressure, plasma creatinine, PAH handling, OAT1/OAT3 expression, and Na-K-ATPase activity.
Main Results:
- CRF rats exhibited elevated blood pressure and creatinine.
- A significant decrease in PAH filtered, secreted, and excreted loads, and systemic clearance was observed in CRF rats.
- Renal OAT1 expression and Na-K-ATPase activity were reduced in CRF rats, while OAT3 expression showed no significant change.
Conclusions:
- Reduced OAT1 expression and Na-K-ATPase activity in CRF rats contribute to the diminished PAH secretion.
- The impaired PAH excretion in CRF is linked to decreased filtered and secreted loads, primarily due to OAT1 downregulation.

Related Concept Videos
 01:22
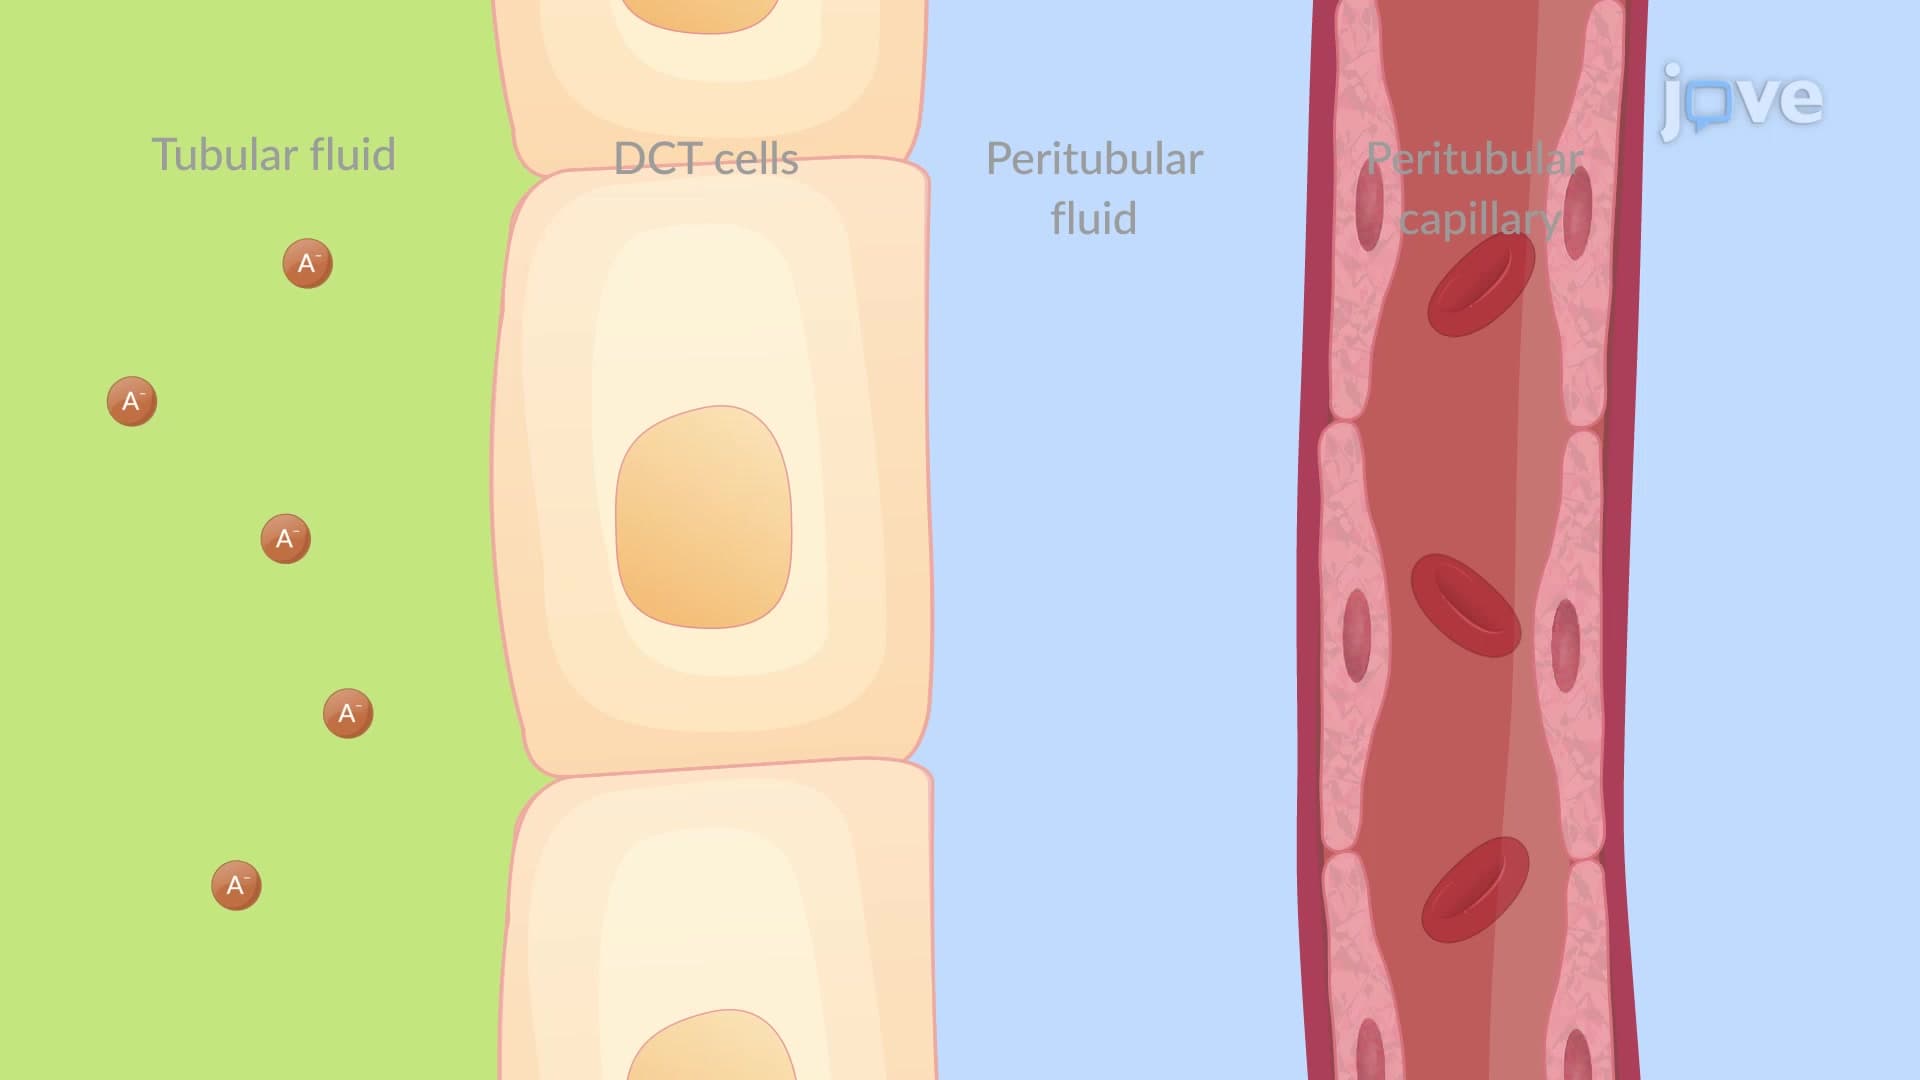
Drug Elimination by Renal Route: Tubular Reabsorption
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a drug,...
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant