Related Experiment Video
Updated: Aug 18, 2026
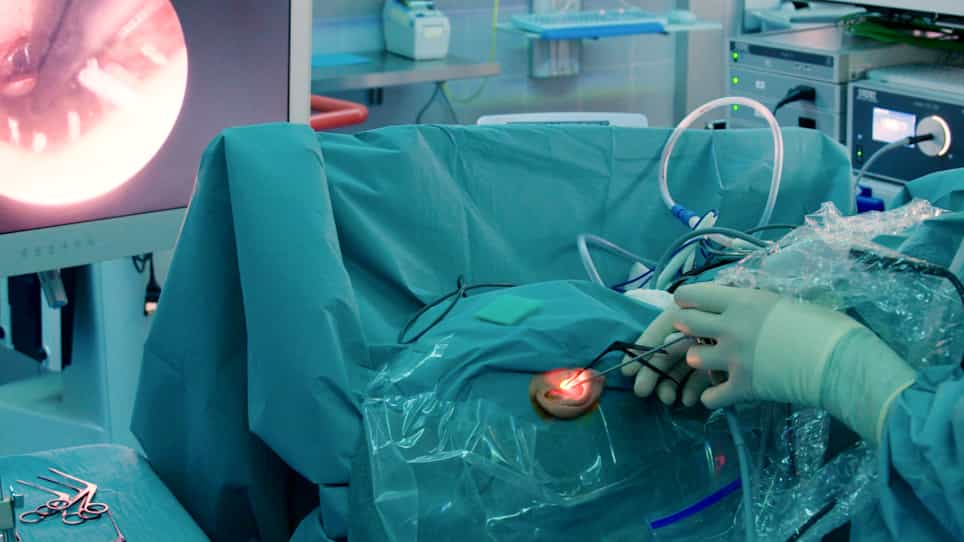

Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
Long-term outcome of atticotomy for cholesteatoma in children
Ari DeRowe1, Gidon Stein, Gadi Fishman
1Department of Otolaryngology-Head and Neck Surgery, Tel-Aviv Sourasky Medical Center, Tel-Aviv, Israel. aderowe@post.tau.ac.il

Insights
Atticotomy (AT) surgery is a less invasive option for pediatric cholesteatoma limited to the attic and middle ear. Long-term outcomes show a dry ear in most cases, with some requiring further surgery for recurrence.
Area of Science:
- Otolaryngology
- Pediatric Surgery
- Medical Devices
Background:
- Cholesteatoma in children requires effective surgical management.
- Atticotomy (AT) is a surgical technique for attic cholesteatoma.
- Evaluating long-term outcomes of AT in pediatric patients is crucial.
Purpose of the Study:
- To assess the long-term results of atticotomy (AT) in children with cholesteatoma.
- To determine the efficacy and safety of AT for pediatric attic cholesteatoma.
Main Methods:
- Retrospective case series of 53 children (5-16 years) undergoing AT for attic and middle ear cholesteatoma (1979-1994).
- AT involved cholesteatoma removal, scutum resection, ossicle excision, and tympanic membrane grafting.
- Mastoid antrum was preserved; outcomes included recurrence, middle ear status, hearing, and reoperation rates.
Main Results:
- Mean follow-up was 5.1 years.
- Eleven percent (21%) of children needed completion canal wall down tympanomastoidectomy for residual/recurrent disease.
- Postoperative hearing improved by 6.1 dB; 98% of ears were dry at final follow-up.
Conclusions:
- Atticotomy (AT) is a viable, less invasive surgical option for selected pediatric cholesteatoma cases confined to the attic and middle ear.
- Careful patient selection is key for successful AT outcomes in children.
- AT demonstrates good long-term results regarding ear dryness and hearing improvement.
Objective:
To evaluate the long-term outcome of atticotomy (AT) surgery for cholesteatoma in children.
Study Design:
Case series, retrospective chart review.
Setting:
General otology practice in a teaching hospital.
Patients:
Fifty-three children aged 5 to 16 years old with cholesteatoma limited to the attic and middle ear who underwent AT between the years 1979 to 1994.
Interventions:
AT consisting of removal of cholesteatoma confined mainly to the attic. The procedure consists of removal of the lateral attic wall (scutum) and involved ossicles with excision of the cholesteatoma and tympanic membrane grafting with temporalis fascia, leaving a small attical cavity. The mastoid antrum was left intact.
Main Outcome Measures:
Disease recurrence, middle ear status, hearing results, and the need for further surgery.
Results:
Mean follow up was 5.1 (+/-3.6) years. Eleven (21%) children required completion canal wall down tympanomastoidectomy because of residual disease or recurrence. The mean preoperative speech recognition threshold was 39.4 +/- 13.4 dB. The mean postoperative speech recognition threshold was 34.5 +/- 15.4, an improvement of 6.1 dB compared with the preoperative level. Last follow-up examination revealed a dry ear in all cases but one.
Conclusions:
In selected cases, AT can be a less invasive option in children with cholesteatoma limited to the attic and middle ear.