Related Experiment Video
Updated: Aug 18, 2026
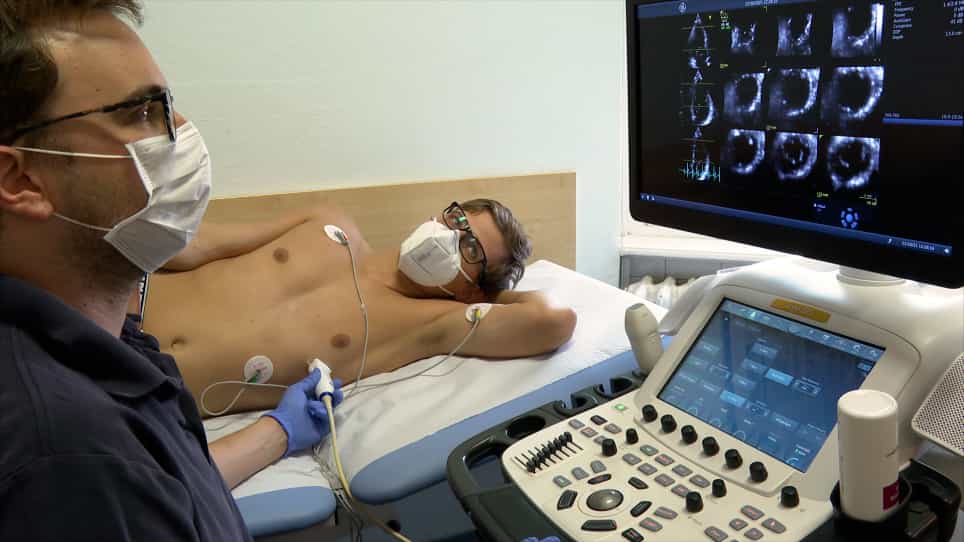

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Left ventricular noncompaction: a pathological study of 14 cases
Allen Burke1, Erik Mont, Robert Kutys
1Department of Cardiovasular Pathology, Armed Forces Institute of Pathology, Washington, DC 20306, USA.

Insights
Left ventricular noncompaction (LVNC) is a cardiomyopathy characterized by a spongy inner layer of the left ventricle. This study details its pathological findings in children, often associated with other cardiac defects and frequently diagnosed post-mortem.
Area of Science:
- Cardiovascular Pathology
- Pediatric Cardiology
- Medical Genetics
Background:
- Left ventricular noncompaction (LVNC) is increasingly recognized as a distinct cardiomyopathy.
- Limited pathological data exists, particularly concerning pediatric cases.
- Understanding LVNC's morphology is crucial for diagnosis and management.
Purpose of the Study:
- To describe the gross and microscopic pathological findings of left ventricular noncompaction (LVNC) in a pediatric cohort.
- To investigate the association of LVNC with congenital heart disease and other cardiac anomalies.
- To highlight diagnostic challenges, especially in autopsy settings.
Main Methods:
- Retrospective analysis of 14 pediatric hearts (13 autopsy, 1 explant) with LVNC.
- Detailed gross examination focusing on ventricular wall morphology and trabeculations.
- Histopathological evaluation including endocardial and myocardial features.
- Correlation of LVNC findings with clinical data and associated cardiac anomalies.
Main Results:
- LVNC was defined by a noncompacted inner layer comprising >50% of LV thickness and poorly developed papillary muscles.
- Common histological features included endocardial fibroelastosis and staghorn-shaped recesses.
- Right ventricular involvement occurred in 6 of 14 cases.
- 8 of 14 cases had associated cardiac anomalies (e.g., VSD, pulmonary stenosis).
- Sudden unexpected death was the primary presentation in 10 cases.
- Diagnosis was rarely suspected antemortem (1/13 autopsy cases).
Conclusions:
- LVNC in children often presents with severe cardiac anomalies and has a high mortality rate, frequently due to sudden death.
- Morphological distinction between isolated and secondary LVNC is not always clear.
- Pathologists play a key role in diagnosing LVNC, often for the first time at autopsy.
Abstract:
Left ventricular noncompaction (LVNC) has been recently proposed as a specific form of cardiomyopathy. There have been few pathological series describing gross and microscopic findings of this entity, especially in children. We present findings of 14 hearts (13 autopsy and 1 explant) with LVNC (isolated and associated with congenital heart disease), defined by poorly developed left ventricular (LV) papillary muscles and a noncompact inner LV myocardial layer comprising more than 50% of the LV thickness. The mean age at death/explant was 3.6 years (median, 2.5 months); there were 6 boys and 8 girls. The symptoms were sudden unexpected death (10) and heart failure (4). The diagnosis was suspected before death in only 1 of 13 autopsy cases. Right ventricular involvement (> 75% ventricular thickness comprised of noncompacted area with recess adjacent to tricuspid valve) was seen in 6 of 14 hearts. One patient had a sibling with pulmonary stenosis, but there was no other known familial cardiomyopathy. Endocardial fibroelastosis was a characteristic histological feature, as well as anastomosing or polypoid endocardial trabeculations, which resulted in staghorn-shaped, endocardial-lined recesses. There was a high rate of other cardiac anomalies, which often coexisted and were not clearly related to the LVNC, present in 8 cases (nonisolated LVNC): ventricular septal defect (4/14), anomalous venous pulmonary veins (1/14), coronary ostial stenosis (1/14), histiocytoid cardiomyopathy (1/14), polyvalvar dysplasia (2/14), and pulmonary stenosis (2/14). In the 6 isolated LVNC, there were 2 malformed atrioventricular valves (1 mitral and 1 tricuspid), which appeared part of the ventricular maldevelopment. There were no differences in histological or gross patterns of the noncompacted regions between the isolated and nonisolated LVNC. LVNC is frequently associated with other cardiac defects, especially when causing sudden death in infants and children. A clear-cut morphological distinction between "isolated" and "secondary" LVNC was not apparent. The pathologist should be aware of the entity because the diagnosis is often first established at autopsy.

Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests