Bullous pemphigoid: from bench to bedside
Related Experiment Video
Updated: Aug 18, 2026
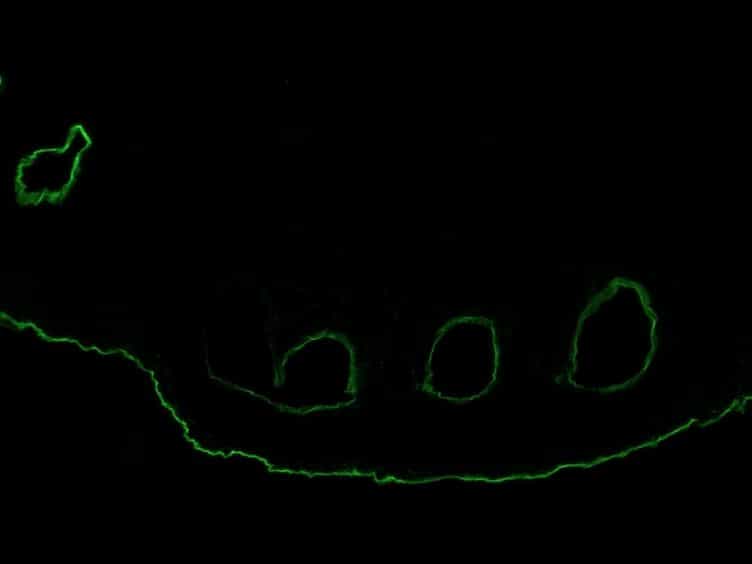
Granulocyte-dependent Autoantibody-induced Skin Blistering
Published on: October 12, 2012
Scott R A Walsh1, David Hogg, P Régine Mydlarski
1Division of Dermatology, University of Toronto, Toronto, Ontario, Canada.

Abstract:
Bullous pemphigoid (BP) is a chronic, autoimmune, blistering disease observed primarily in the elderly population. Several clinical variants have been described, including classic (bullous), localised, nodular, vegetating, erythrodermic, erosive, childhood and drug-induced forms. Autoantibodies target the BP230 and BP180 antigens, located in the hemidesmosomal complex of the skin basement membrane zone. Subsequent complement activation recruits chemical and cellular immune mediators to the skin, ultimately resulting in blister formation. Both autoantibodies and complement may be detected by various immunofluorescent, immune electron microscopy and molecular biology techniques. Recent trials suggest that potent topical corticosteroids should be considered as first-line therapy. Tetracycline with or without nicotinamide may benefit a subset of patients with mild BP. Oral corticosteroids should rarely exceed 0.75 mg/kg/day and corticosteroid-sparing agents may be useful for recalcitrant disease.