Recurrent laryngeal nerve damage and phonetic modifications after total thyroidectomy: surgical malpractice only or predictable sequence?
Related Experiment Video
Updated: Aug 18, 2026
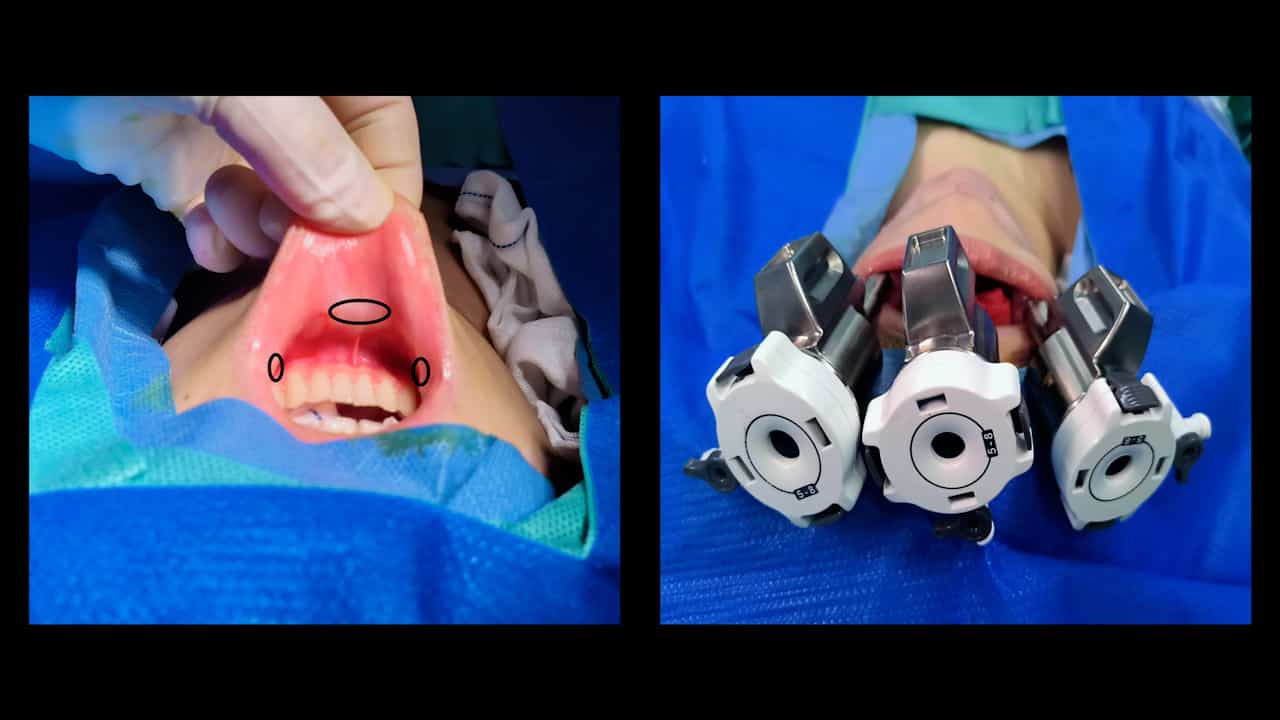
Identification and Protection of the Recurrent Laryngeal Nerve during Transoral Robotic Thyroidectomy
Published on: October 24, 2025
Lodovico Rosato1, Maria Teresa Carlevato, Giorgio De Toma
1Department of Surgery, Endocrine Surgical Unit, Ivrea Hospital, Piazza della Credenza, Ivrea, 2-10015, Italy, presidente@clubdelleuec.it

Abstract:
Modifications of phonation occurring after total thyroidectomy (TT) are usually attributed to surgical malpractice, but other causes of voice impairment even in nonoperated subjects should also be taken into account. This study analyzes 208 patients who underwent TT from January 1, 1999 through December 31, 2001. Follow-up ended on December 31, 2003. Only cases in which the surgeon ruled out the possibility of operative damage to the laryngeal nerves were included. All patients underwent pre- and postoperative clinical and instrumental nose and throat examination (NTE). Preoperatively, 86 patients (41%) showed hoarseness or dysphagia: 4 (2%) monoplegia and 12 (6%) hypomobility of the vocal cords due to impaired function of the recurrent laryngeal nerve (RLN); 6 (3%) cord hypotonia due to impairment of the superior laryngeal nerve (SLN); 34 (16%) dysphagia: and 30 (14%) hoarseness due to other causes. At follow-up 1 month after surgery, 71 patients (34%) had an onset of previously absent signs and symptoms: 8 (4%) had palsy of one vocal cord (2% permanent); 6 (3%) had cord hypomobility (all temporary); 12 (6%) had cord hypotonia due to disease of the SLN, 4 of which (2%) were permanent; 44 patients (21%) had symptoms due to scarring and adhesions between the laryngotracheal axis and the prethyroid muscles and between these and the skin. One patient (0.5%) had a nodular cord lesion that occurred after 3 months. Overall, more than one-third of the patients had preoperative voice modifications or swallowing impairment, around one-third had these problems after TT, and less than one-third were free of pre- and postoperative complications. The surgeon's care to avoid damage to the anatomica integrity of the of laryngeal nerves does not exclude functional problems of the nerves and of laryngeal dynamics. In fact, such problems could be referred to outcomes linked to the operation itself (hematoma, edema, scarring adhesion) or to events that only temporarily follow surgery but must be considered as an unavoidable sequel (e.g., neuritis, viral neuritis, myopathy). The patient should undergo a careful clinical and instrumental NTE to detect conditions prior to surgery, and the information provided by the surgeons should be thorough to allow the patient to be aware of all possible sequels and consequences.
More Related Videos
 07:45
"Sun's Seven-Step Technique" for Endoscopic En-Bloc Resection of Thyroid Cancer via the Chest-Breast Approach
Published on: November 28, 2025
 11:46
Investigation of the Electrophysiological and Thermographic Safety Parameters of Surgical Energy Devices During Thyroid and Parathyroid Surgery in a Porcine Model
Published on: October 13, 2022
Related Concept Videos
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids, corniculates, and...
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques