Variation in the alpha2B-adrenergic receptor gene (ADRA2B) and its relationship to vascular response in vivo
Related Experiment Video
Updated: Aug 18, 2026
Cardiac Response to β-Adrenergic Stimulation Determined by Pressure-Volume Loop Analysis
Published on: May 19, 2021
Mordechai Muszkat1, Daniel Kurnik, Joseph Solus
1Department of Medicine, Division of Clinical Pharmacology, Vanderbilt University School of Medicine, Nashville, Tennessee 37232-6602, USA.

Abstract:
The alpha2B-adrenergic receptor (ADRA2B) plays an important role in vasoconstriction and blood pressure regulation. One common variant in the ADRA2B gene (del 301--303) has been identified, and results in markedly decreased receptor desensitization in vitro but does not alter vascular sensitivity in vivo. Therefore, we fully characterized genetic variations in ADRA2B and related them to phenotype in vivo. We examined 5812 bp of contiguous sequence of ADRA2B (promoter, exonic, and 3'-untranslated region; 3'-UTR) using the polymerase chain reaction to amplify the genomic target followed by bidirectional sequencing (n=68). Haplotypes were inferred using an expectation maximization algorithm. Vasoconstriction in response to increasing doses of the highly selective alpha2-adrenergic receptor agonist, dexmedetomidine (0.01--1000 ng/min) was measured in the dorsal hand vein using a linear variable differential transformer. The dose that produced 50% (ED50) of maximum venoconstriction (Emax) was determined for each subject from the individual dose--response curves. ED50 and Emax were compared in subjects with and without variant alleles and haplotypes of interest. We identified 24 variable sites, 12 in the promoter region, five in the coding region (including two previously described as non-synonymous variants) and seven in the 3'-UTR region. Four haplotypes were inferred, representing approximately 95% of the cohort. One haplotype, characterized by two single nucleotide polymorphisms in the promoter region, and one in the 3'-UTR, occurred in seven of 38 African-Americans, and was associated with a lower Emax, 61.3% [95% confidence interval (CI) 39.5--83.0, n=7] compared to 78.1% (CI 73.8--82.5) in wild-types (n=61) (P=0.02). There was no association between the nine common variants and dexmedetomidine ED50. We have described novel variants and haplotypes of the ADRA2B gene. These do not alter sensitivity to a selective alpha2-adrenergic receptor agonist but some may decrease maximal venoconstriction in vivo.
Related Concept Videos
 01:26
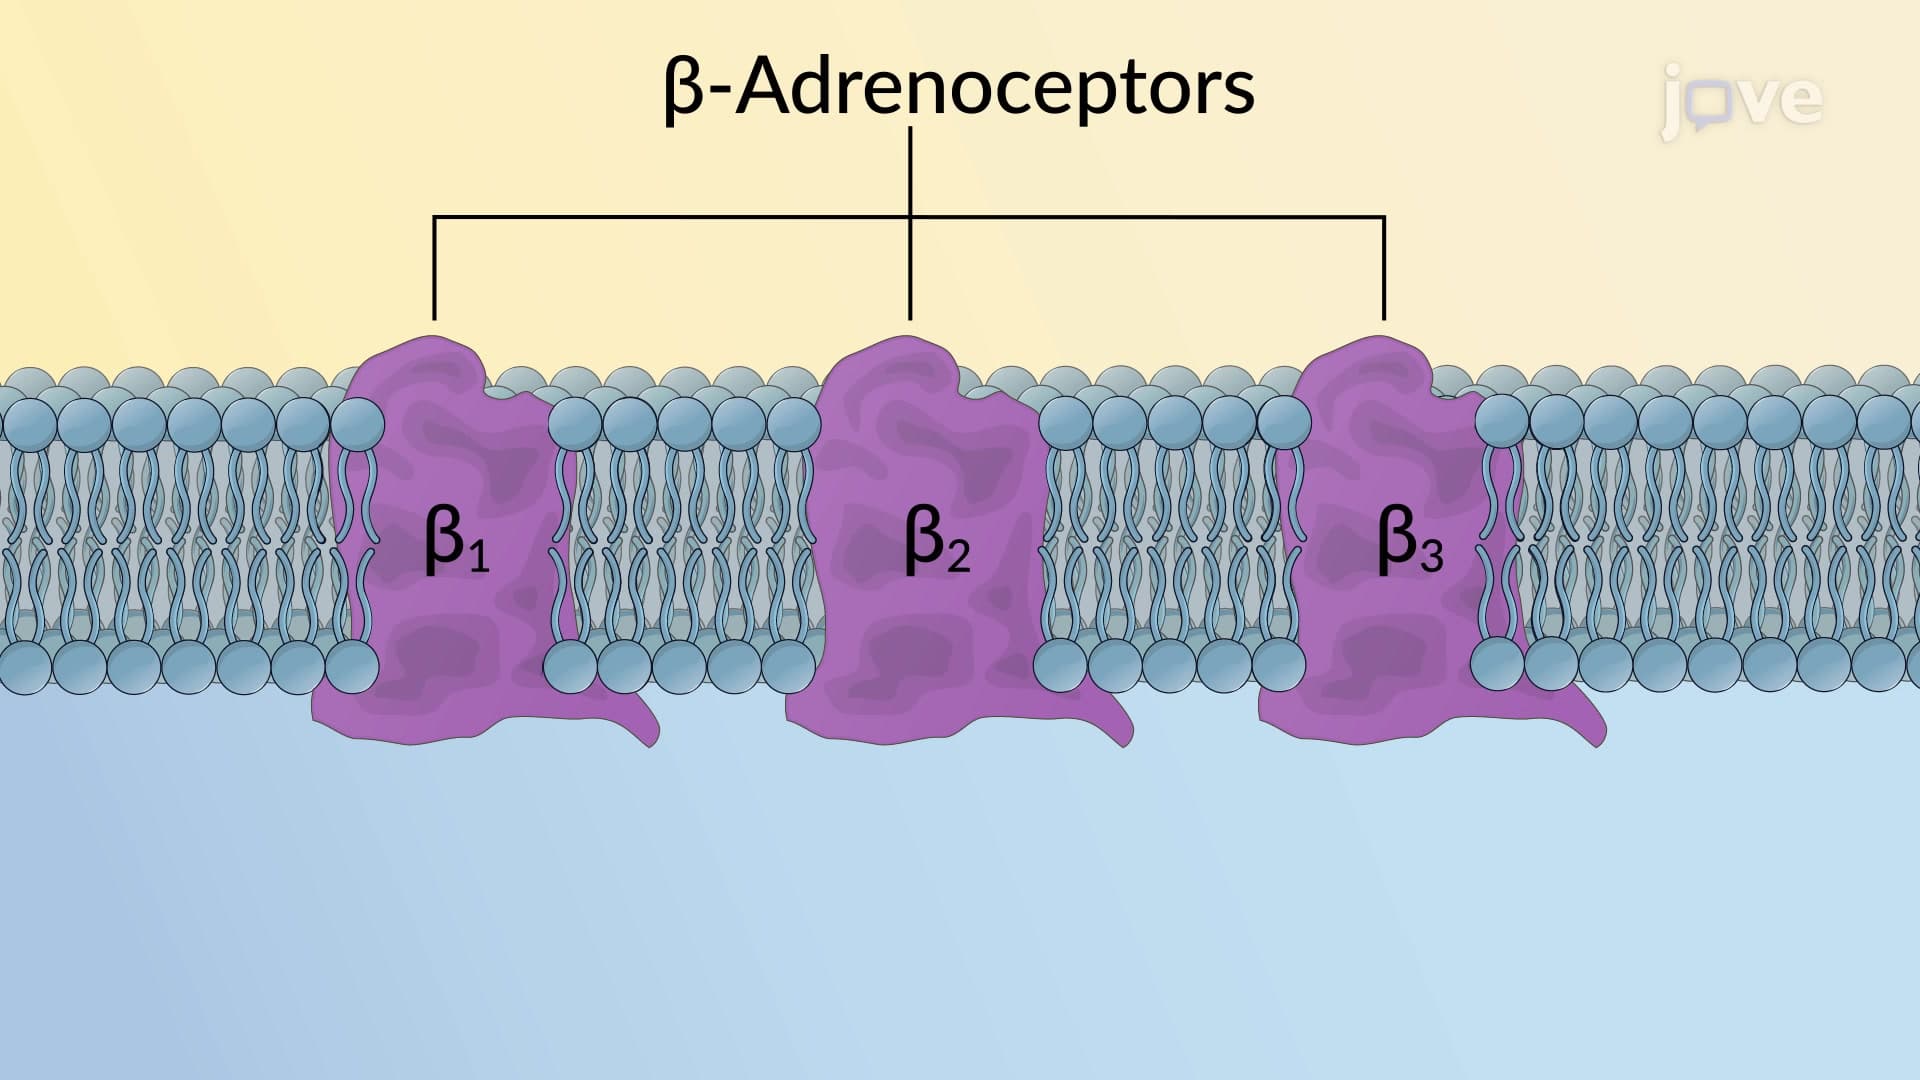
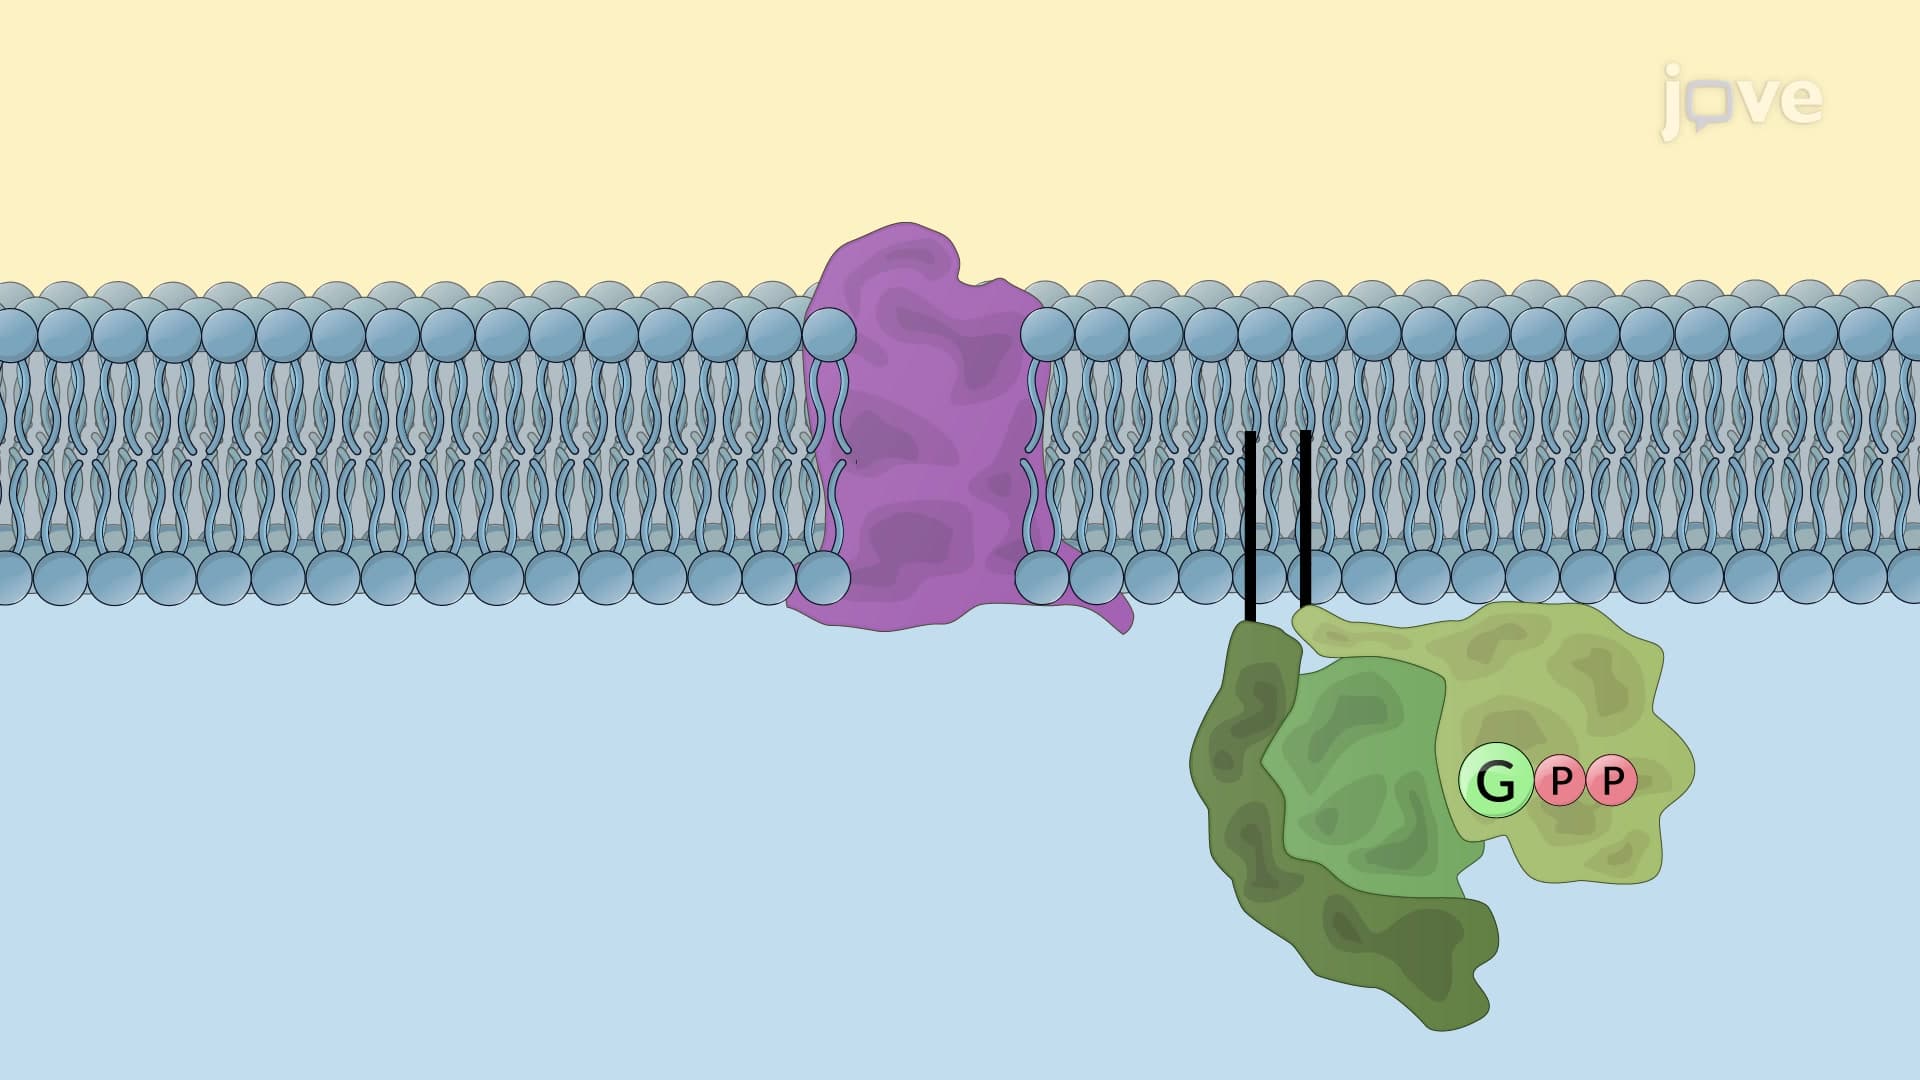
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:31
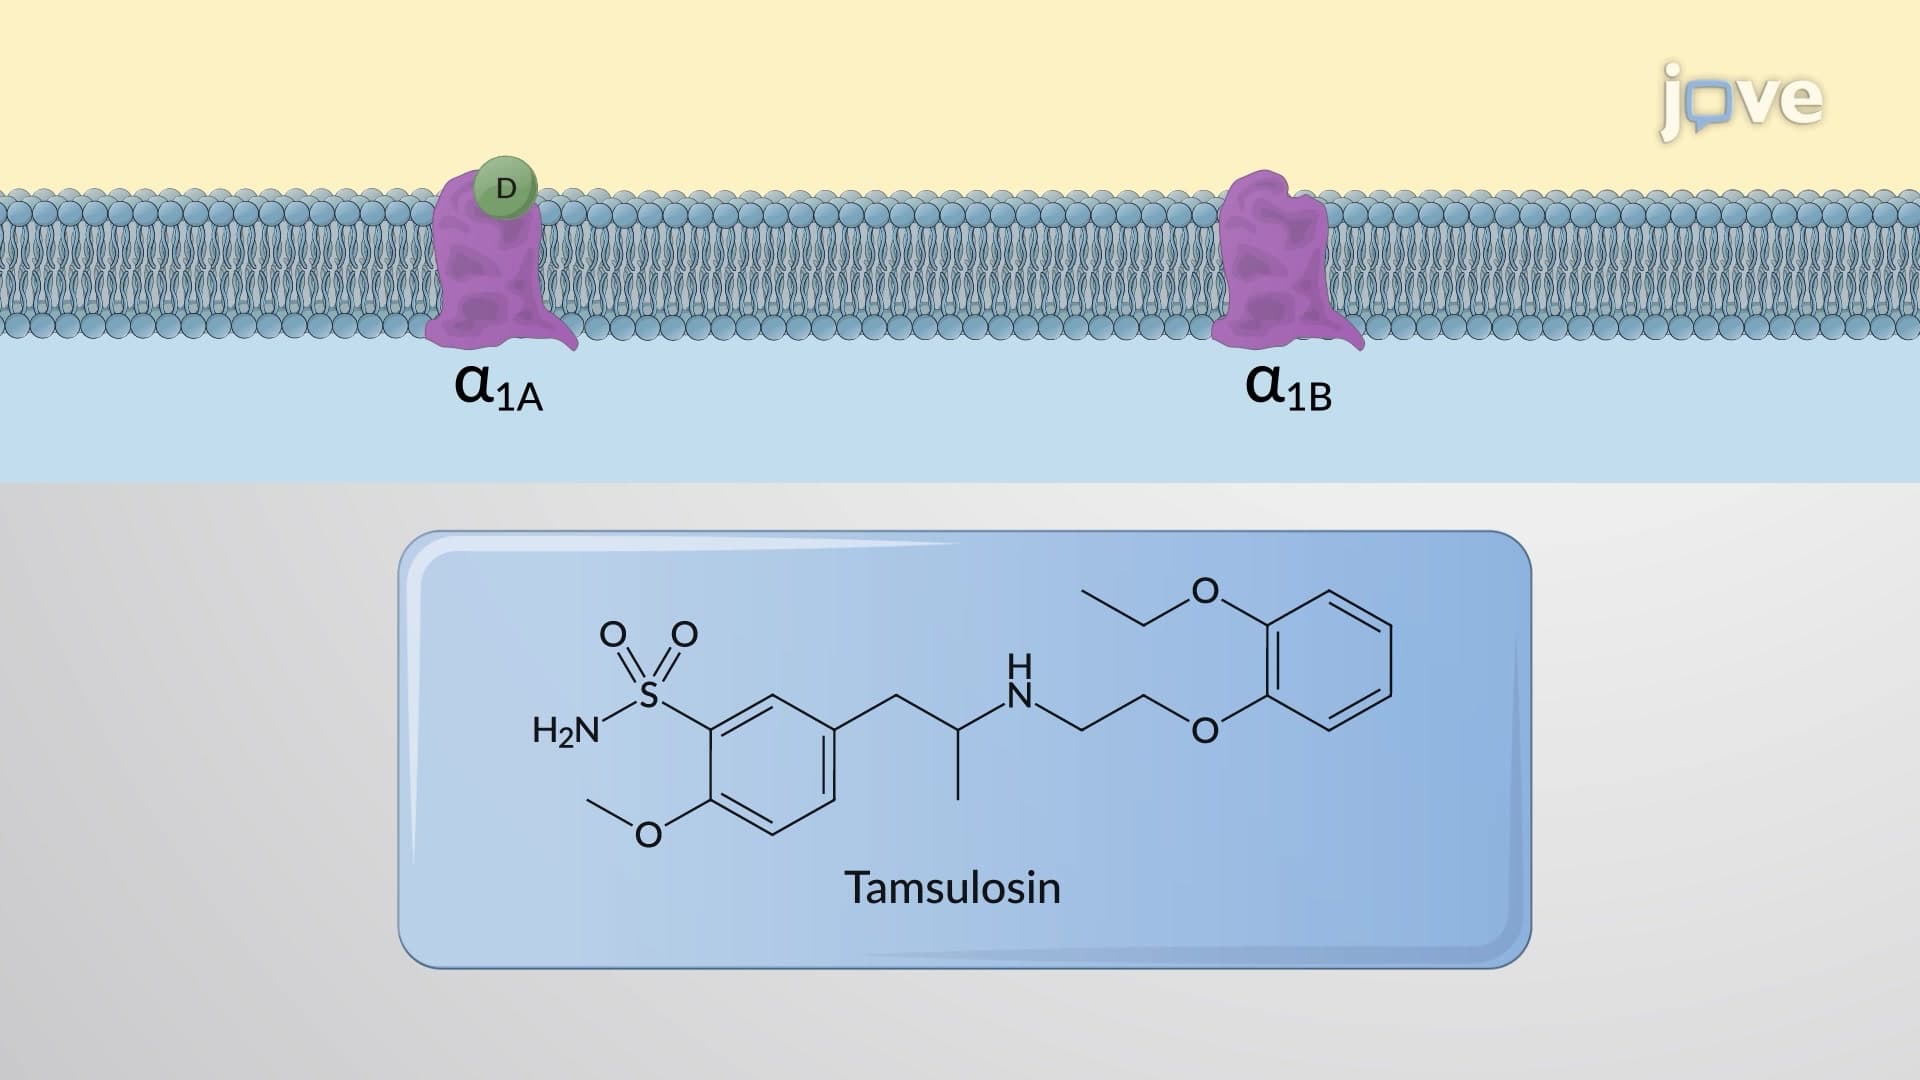
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...