Assessment of drug-induced QT prolongation: to bin or not to bin?

Marek Malik1

  • 1Department of Cardiac and Vascular Sciences, St George's Hospital Medical School, Cranmer Terrace, London SW17 ORE, United Kingdom. m.malik@sghms.ac.uk

Abstract

No abstract available in PubMed .

Related Concept Videos

Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers01:12

Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers

Class III antiarrhythmic drugs are a group of medications that can prolong action potentials in the heart. They achieve this by blocking potassium channels or enhancing inward currents from sodium channels. However, these drugs have a unique property of "reverse use-dependence," which is most pronounced at slower heart rates and can lead to torsades de pointes—a specific type of arrhythmia. However, it is essential to note that excessive QT interval prolongation—a measure of the heart's...
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test01:22

Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test

In clinical practice, the direct measurement of hepatic blood flow to evaluate liver function presents significant challenges due to the intricate and specialized nature of the necessary techniques. Consequently, healthcare professionals often rely on empirical estimates derived from thorough patient examinations and liver function tests to gauge liver health. Among the tools at their disposal, the Child–Pugh and MELD scoring systems stand out for their ability to categorize and assess the...
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers01:22

Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers

Class I antiarrhythmic drugs are used to treat various types of arrhythmias or irregular heart rhythms. These drugs block the sodium (Na+) channels in the cardiac cells, thereby affecting the movement of electrical impulses across the heart. Class I antiarrhythmic drugs are divided into three subgroups: Class IA, Class IB, and Class IC, each with distinct mechanisms of action and effects on the heart.
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
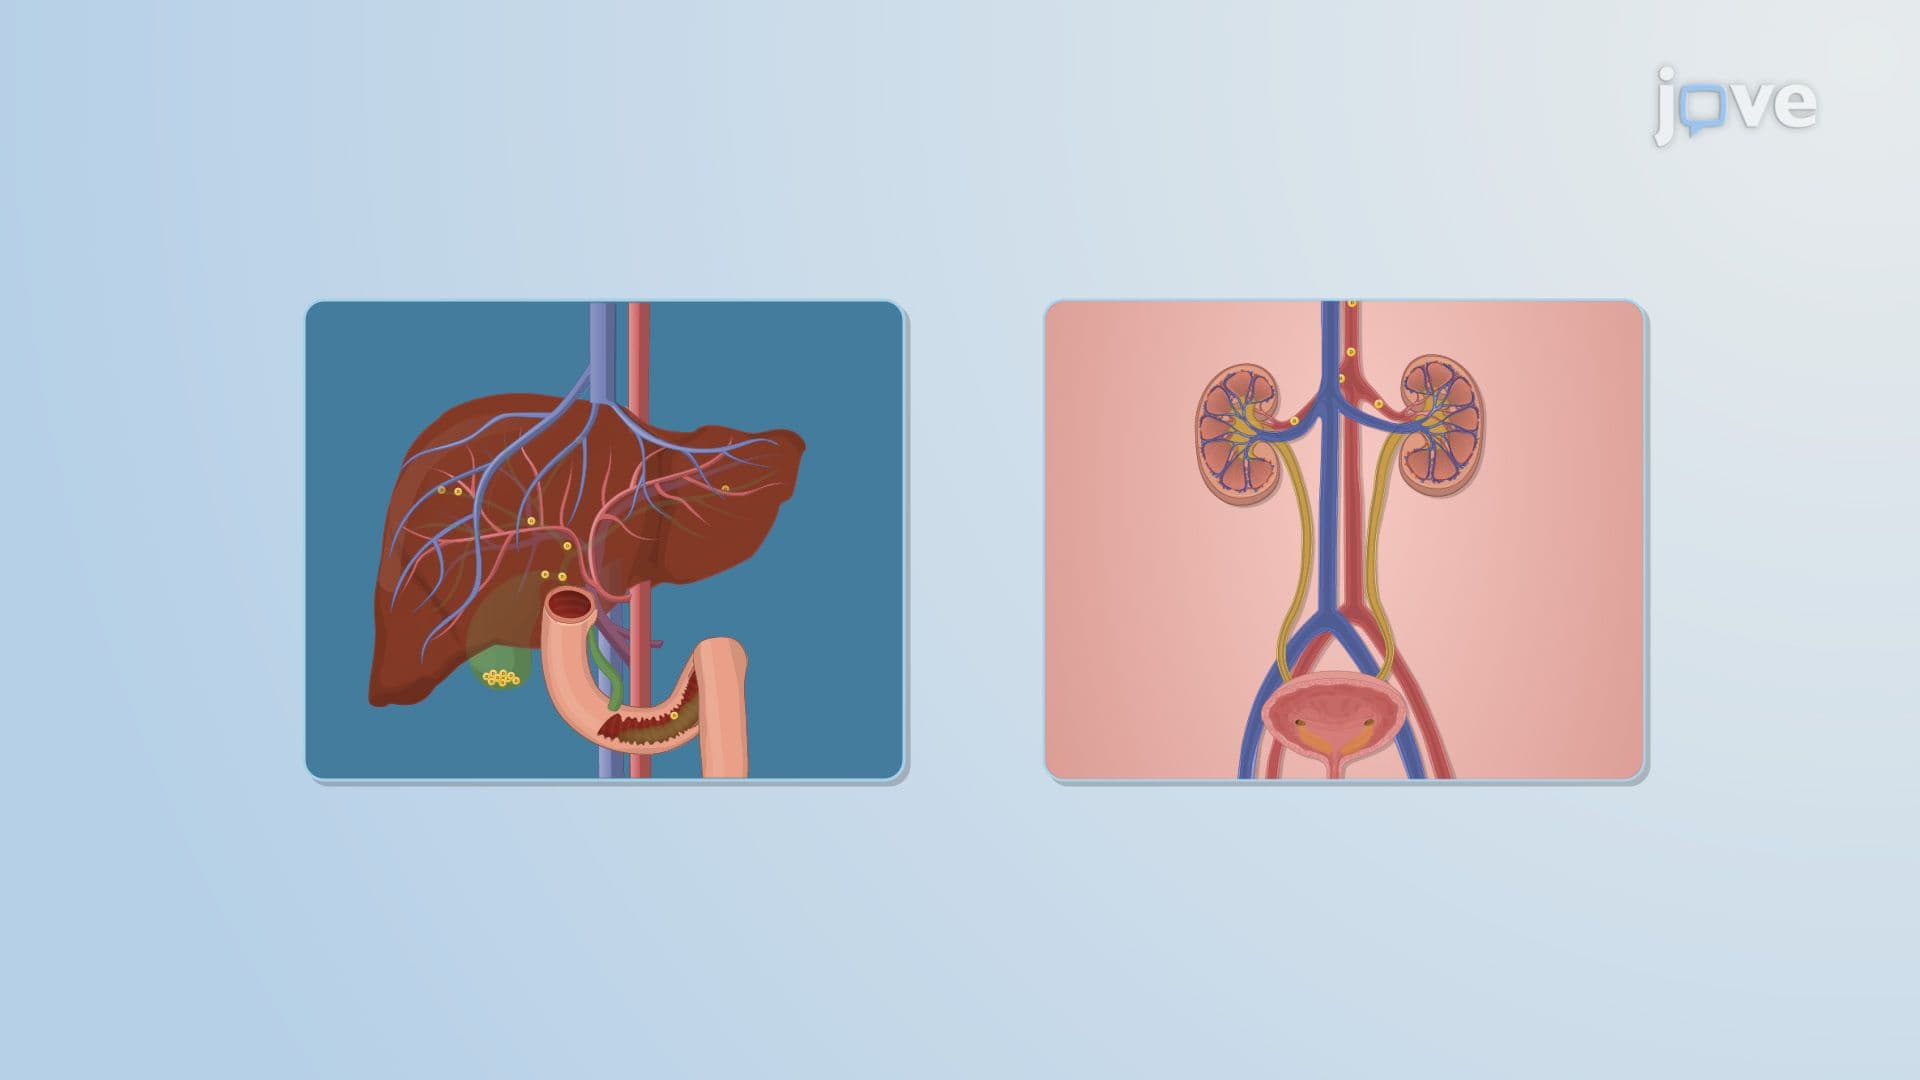
Pharmacokinetic–Pharmacodynamic Relationship: Influence of Elimination Half-Life on Effect Duration01:23

Pharmacokinetic–Pharmacodynamic Relationship: Influence of Elimination Half-Life on Effect Duration

Drug elimination from the body primarily occurs through metabolic and excretion pathways. Hepatic metabolism transforms lipophilic drugs into hydrophilic forms for excretion, typically via enzymatic processes classified as phase I (modification) and phase II (conjugation). Renal excretion eliminates drugs and metabolites through filtration and secretion in the kidneys. Impairment in liver or kidney function can hinder these processes, delaying drug clearance and extending the drug’s half-life.
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers01:24

Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers

Adrenergic stimulation generally impacts cardiac rate and rhythm. Specifically, stimulation of the β-adrenoceptors triggers an increase in intracellular calcium ion influx and pacemaker currents, which may cause arrhythmias. Catecholamines like adrenaline also demonstrate β2-adrenoceptor-mediated hypokalemia, impacting cardiac action potential and disrupting the normal cardiac rhythm. Class II antiarrhythmic drugs are β-adrenoceptor antagonists or β-blockers, which indirectly block calcium...
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment01:08

Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment

Hepatic impairment, characterized by decreased liver function, does not uniformly mandate adjustments in drug dosage. Whether dosage modifications are necessary depends on various factors related to the drug's metabolism and elimination pathways. If a drug is primarily excreted via the kidneys and bypasses significant hepatic processing, if it undergoes minimal metabolic transformation in the liver, or if it is volatile and primarily expelled through the lungs, dose adjustments may not be...
