Related Experiment Video
Updated: Aug 17, 2026
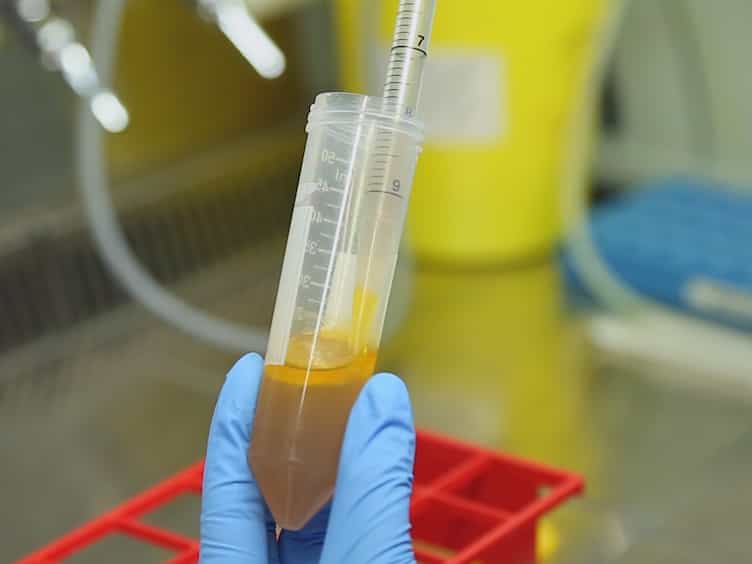
An Ex vivo Model to Study Hormone Action in the Human Breast
Published on: January 8, 2015
Progestins and progesterone in hormone replacement therapy and the risk of breast cancer
Carlo Campagnoli1, Françoise Clavel-Chapelon, Rudolf Kaaks
1Unit of Endocrinological Gynecology, Sant'Anna Gynecological Hospital, Corso Spezia 60, 10126 Torino, Italy. ginendocrinol@oirmsantanna.piemonte.it

Abstract:
Controlled studies and most observational studies published over the last 5 years suggest that the addition of synthetic progestins to estrogen in hormone replacement therapy (HRT), particularly in continuous-combined regimen, increases the breast cancer (BC) risk compared to estrogen alone. By contrast, a recent study suggests that the addition of natural progesterone in cyclic regimens does not affect BC risk. This finding is consistent with in vivo data suggesting that progesterone does not have a detrimental effect on breast tissue. The increased BC risk found with the addition of synthetic progestins to estrogen could be due to the regimen and/or the kind of progestin used. Continuous-combined regimen inhibits the sloughing of mammary epithelium that occurs after progesterone withdrawal in a cyclic regimen. More importantly, the progestins used (medroxyprogesterone acetate and 19-Nortestosterone-derivatives) are endowed with some non-progesterone-like effects, which can potentiate the proliferative action of estrogens. Particularly relevant seem to be the metabolic and hepatocellular effects (decreased insulin sensitivity, increased levels and activity of insulin-like growth factor-I, and decreased levels of SHBG), which contrast the opposite effects induced by oral estrogen.

Related Concept Videos
 01:24
Disorders of the Female Reproductive System
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair growth — and...
 01:22
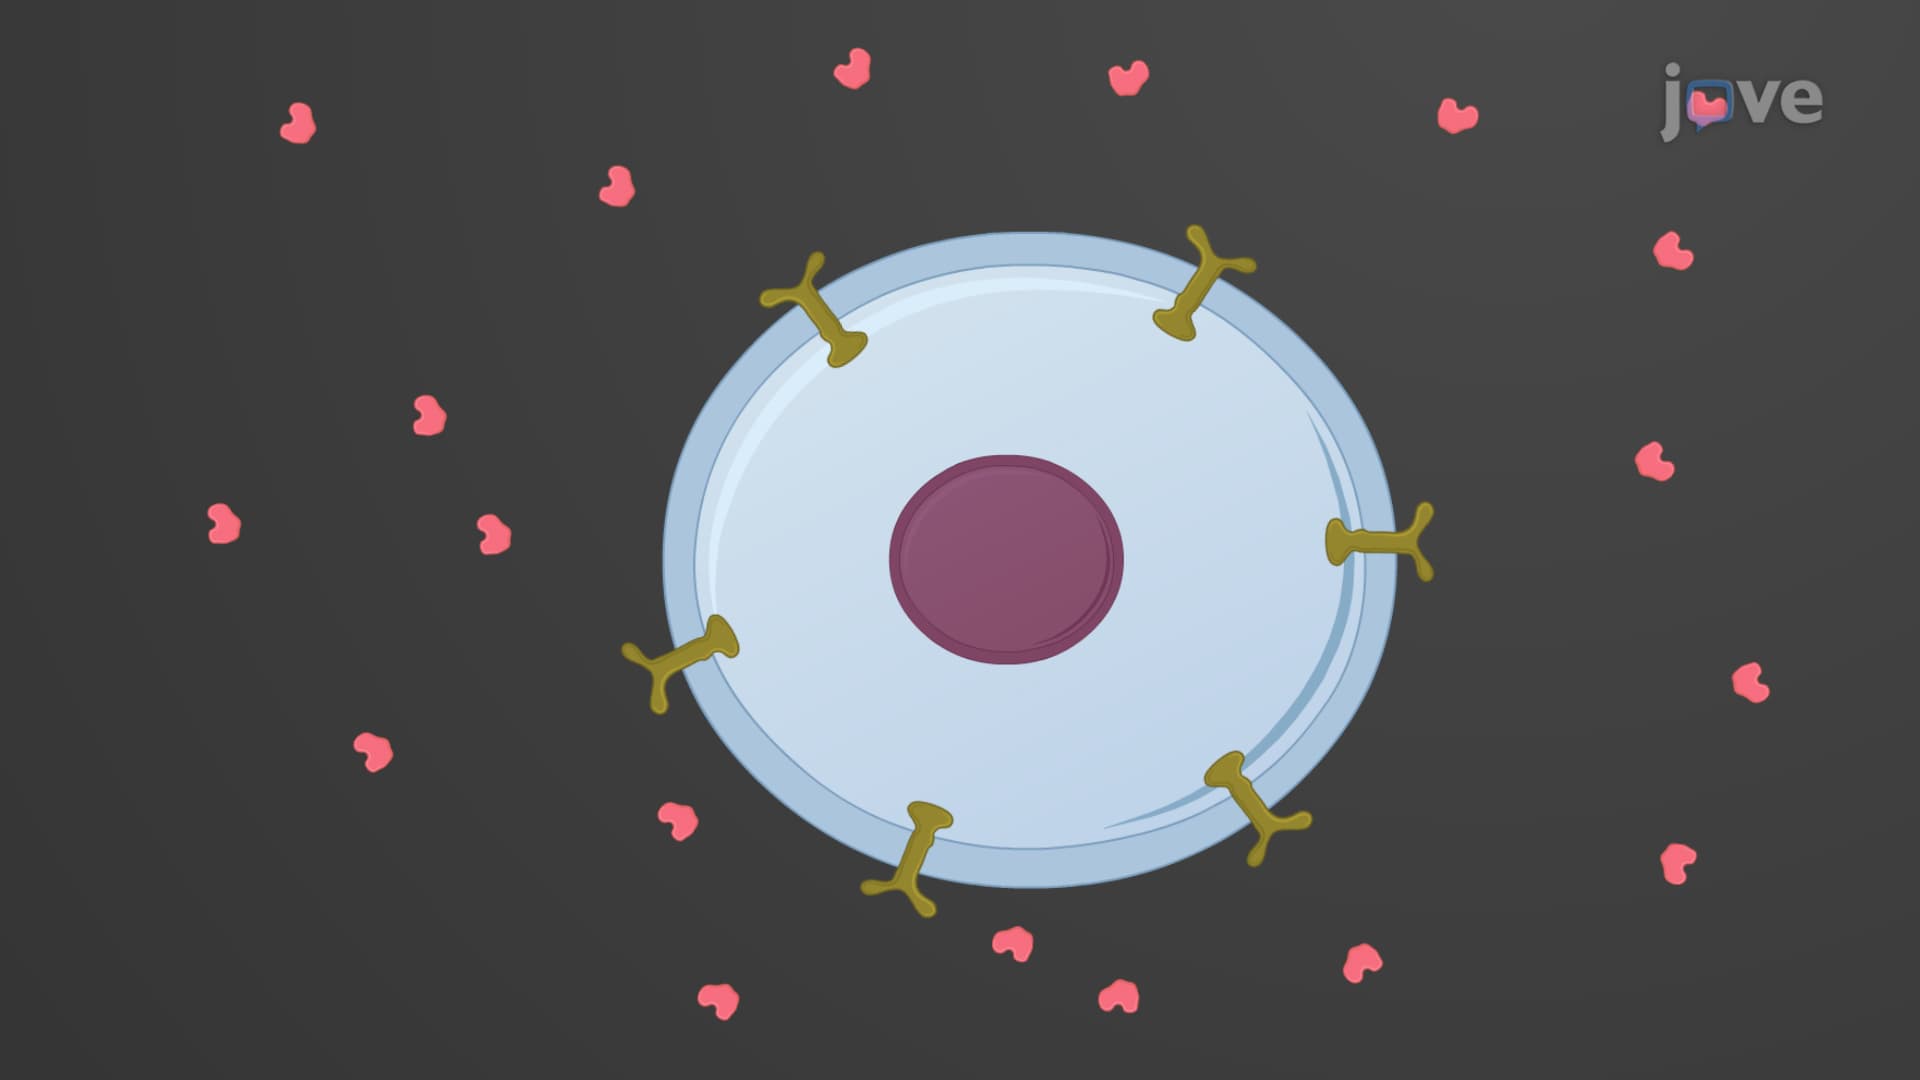
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...