Related Experiment Video
Updated: Aug 17, 2026

Induction of Nephrotic Syndrome in Mice by Retrobulbar Injection of Doxorubicin and Prevention of Volume Retention by Sustained Release Aprotinin
Published on: May 6, 2018
Effect of impaired renal function and haemodialysis on the pharmacokinetics of aprepitant
Arthur J Bergman1, Thomas Marbury, Trisha Fosbinder
1Merck Research Laboratories, West Point, Pennsylvania, USA.

Background:
The neurokinin NK(1)-receptor antagonist aprepitant has demonstrated efficacy in preventing highly emetogenic chemotherapy-induced nausea and vomiting.
Objective:
The objective of the present study was to investigate the effects of impaired renal function on the pharmacokinetics and safety of aprepitant.
Subjects And Methods:
A total of 32 patients and healthy subjects were evaluated in this open-label, two-part study. Pharmacokinetic parameters after a single oral dose of aprepitant 240 mg were measured in eight patients with end-stage renal disease (ESRD) requiring haemodialysis, eight patients with severe renal insufficiency (SRI [24-hour creatinine clearance <30 mL/min/1.73 m(2)]) and 16 healthy and age-, sex- and weight-matched subjects (controls).
Results:
In ESRD patients, the area under the plasma concentration-time curve (AUC) from 0 to 48 hours (AUC(48)) for aprepitant was on average approximately 36% lower than that observed in control subjects (ratio [ESRD patients/healthy controls] of geometric means = 0.64), but the 90% confidence interval 0.52, 0.78 for the ratio of true mean AUC(48) fell within the predefined target interval of 0.5, 2.0. Also in ESRD patients, there was no statistically or clinically significant difference in unbound aprepitant AUC (which may be more clinically relevant than total aprepitant AUC) when compared with healthy control subjects. Aprepitant pharmacokinetic parameters in ESRD patients were clinically similar when haemodialysis was initiated at 4 hours or 48 hours after aprepitant administration. In SRI patients, the ratio (SRI patients/healthy controls) of aprepitant AUC from zero to infinity (AUC(infinity)) geometric mean value was 0.79 with a 90% confidence interval of 0.56, 1.10. On average, in SRI patients the principal aprepitant pharmacokinetic parameters (AUC(infinity), initial maximum plasma concentration [C(max)], time to initial C(max), and apparent elimination half-life) were not statistically different from those obtained in healthy control subjects. Aprepitant was generally well tolerated in both ESRD and SRI patients.
Conclusion:
The results of this study demonstrate that ESRD, haemodialysis and SRI have no clinically meaningful effect on aprepitant pharmacokinetics. Therefore, no dosage adjustment of aprepitant is warranted in SRI or ESRD patients.
Related Concept Videos
 01:08
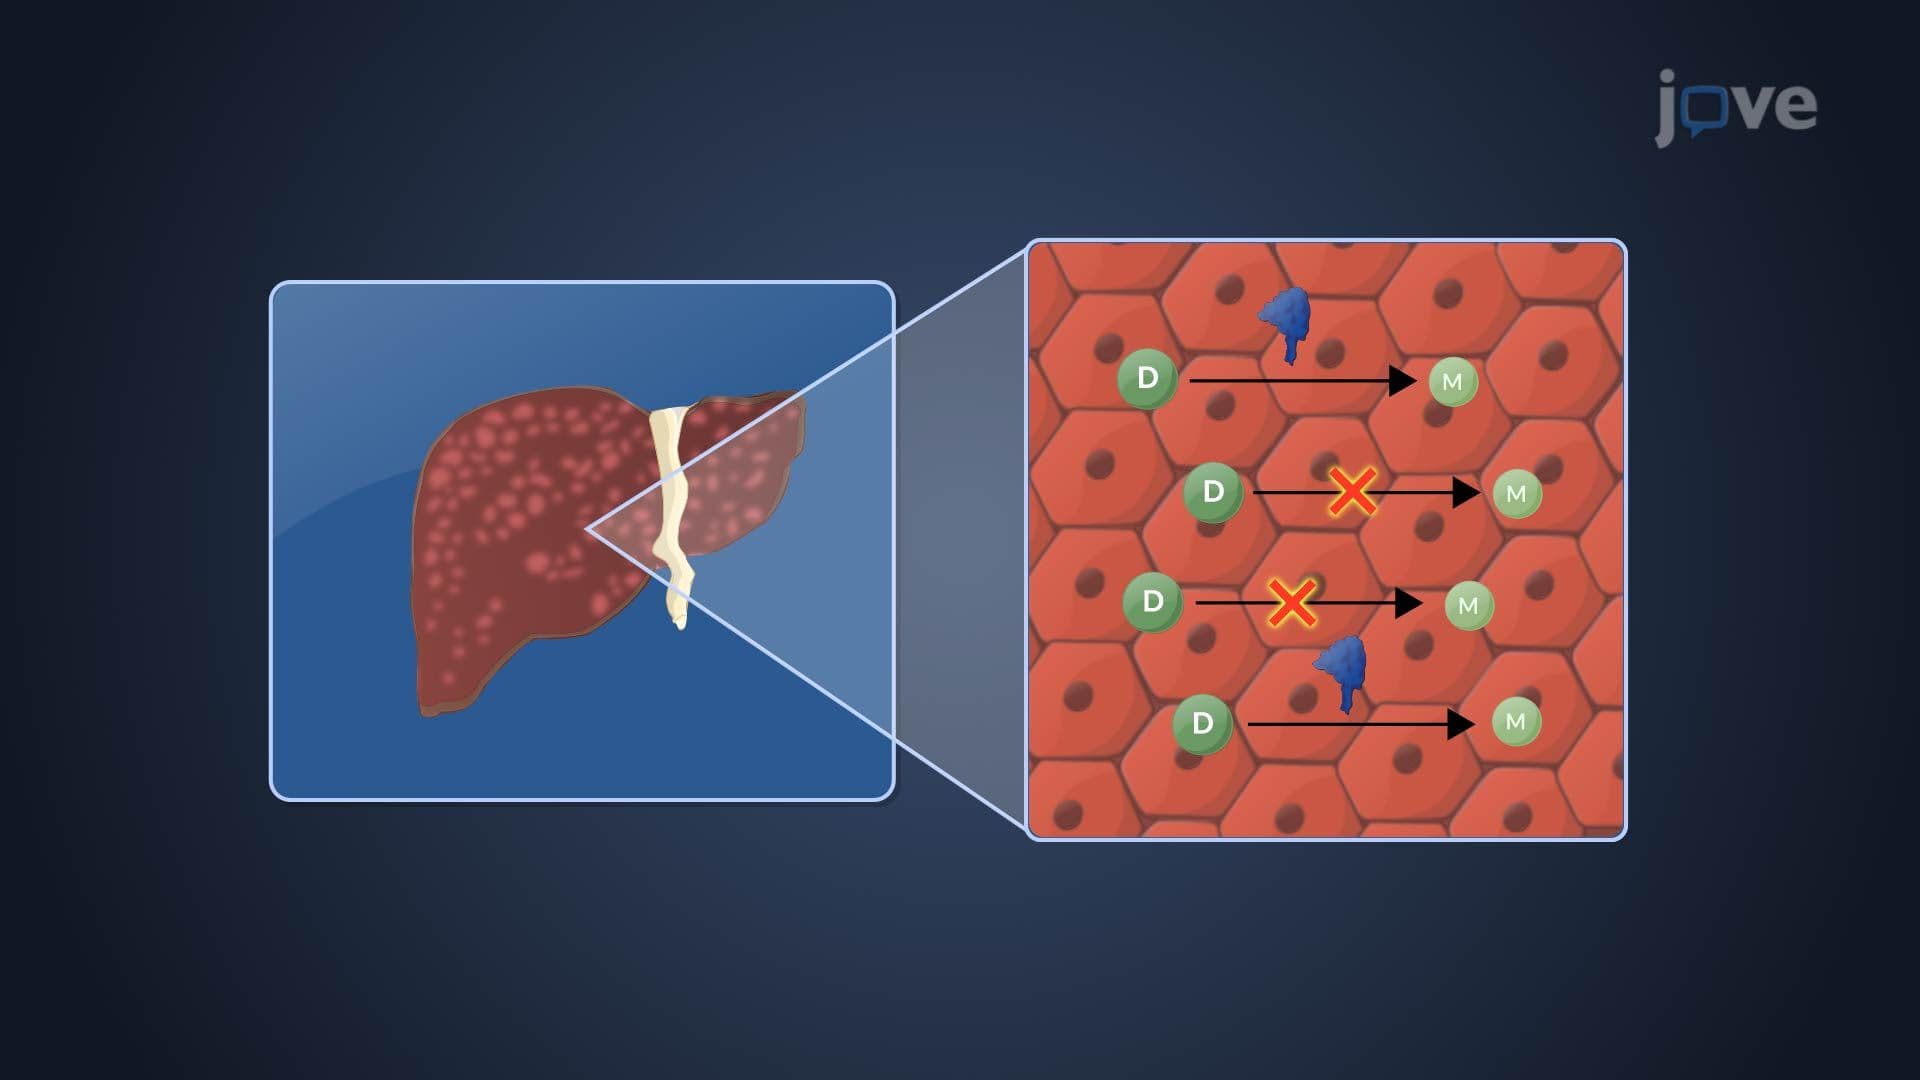
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:14
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug