Related Experiment Videos
Pharmacokinetics and pharmacodynamics of imipenem during continuous renal replacement therapy in critically ill
Douglas N Fish1, Isaac Teitelbaum, Edward Abraham
1University of Colorado Health Sciences Center, Department of Clinical Pharmacy, School of Pharmacy, Campus Box C-238, 4200 East Ninth Avenue, Denver, CO 80262, USA. doug.fish@uchsc.edu

The pharmacokinetics of imipenem were studied in adult intensive care unit (ICU) patients during continuous venovenous hemofiltration (CVVH; n=6 patients) or hemodiafiltration (CVVHDF; n=6 patients). Patients (mean+/-standard deviation age, 50.9+/-15.9 years; weight, 98.5+/-15.9 kg) received imipenem at 0.5 g every 8 to 12 h (total daily doses of 1 to 1.5 g/day) by intravenous infusion over 30 min. Pre- and postmembrane blood (plasma) and corresponding ultrafiltrate or dialysate samples were collected 1, 2, 4, and 8 or 12 h (depending on dosing interval) after completion of the drug infusion. Drug concentrations were measured using validated high-performance liquid chromatography methods. Mean systemic clearance (CL(S)) and elimination half-life (t1/2) of imipenem were 145+/-18 ml/min and 2.7+/-1.3 h during CVVH versus 178+/-18 ml/min and 2.6+/-1.6 h during CVVHDF, respectively. Imipenem clearance was substantially increased during both CVVH and CVVHDF, with membrane clearance representing 25% and 32% of CL(S), respectively. The results of this study indicate that CVVH and CVVHDF contribute to imipenem clearance to a greater degree than previously reported. Imipenem doses of 1.0 g/day appear to achieve concentrations adequate to treat most common gram-negative pathogens (MIC up to 2 microg/ml) during CVVH or CVVHDF, but doses of 2.0 g/day or more may be required to adequately treat and prevent resistance in pathogens with higher MICs (MIC=4 to 8 microg/ml). Higher doses should only be used after consideration of potential central nervous system toxicities or other risks of therapy in these severely ill patients.
The pharmacokinetics of imipenem were studied in adult intensive care unit (ICU) patients during continuous venovenous hemofiltration (CVVH; n=6 patients) or hemodiafiltration (CVVHDF; n=6 patients). Patients (mean+/-standard deviation age, 50.9+/-15.9 years; weight, 98.5+/-15.9 kg) received imipenem at 0.5 g every 8 to 12 h (total daily doses of 1 to 1.5 g/day) by intravenous infusion over 30 min. Pre- and postmembrane blood (plasma) and corresponding ultrafiltrate or dialysate samples were collected 1, 2, 4, and 8 or 12 h (depending on dosing interval) after completion of the drug infusion. Drug concentrations were measured using validated high-performance liquid chromatography methods. Mean systemic clearance (CL(S)) and elimination half-life (t1/2) of imipenem were 145+/-18 ml/min and 2.7+/-1.3 h during CVVH versus 178+/-18 ml/min and 2.6+/-1.6 h during CVVHDF, respectively. Imipenem clearance was substantially increased during both CVVH and CVVHDF, with membrane clearance representing 25% and 32% of CL(S), respectively. The results of this study indicate that CVVH and CVVHDF contribute to imipenem clearance to a greater degree than previously reported. Imipenem doses of 1.0 g/day appear to achieve concentrations adequate to treat most common gram-negative pathogens (MIC up to 2 microg/ml) during CVVH or CVVHDF, but doses of 2.0 g/day or more may be required to adequately treat and prevent resistance in pathogens with higher MICs (MIC=4 to 8 microg/ml). Higher doses should only be used after consideration of potential central nervous system toxicities or other risks of therapy in these severely ill patients.
Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:24
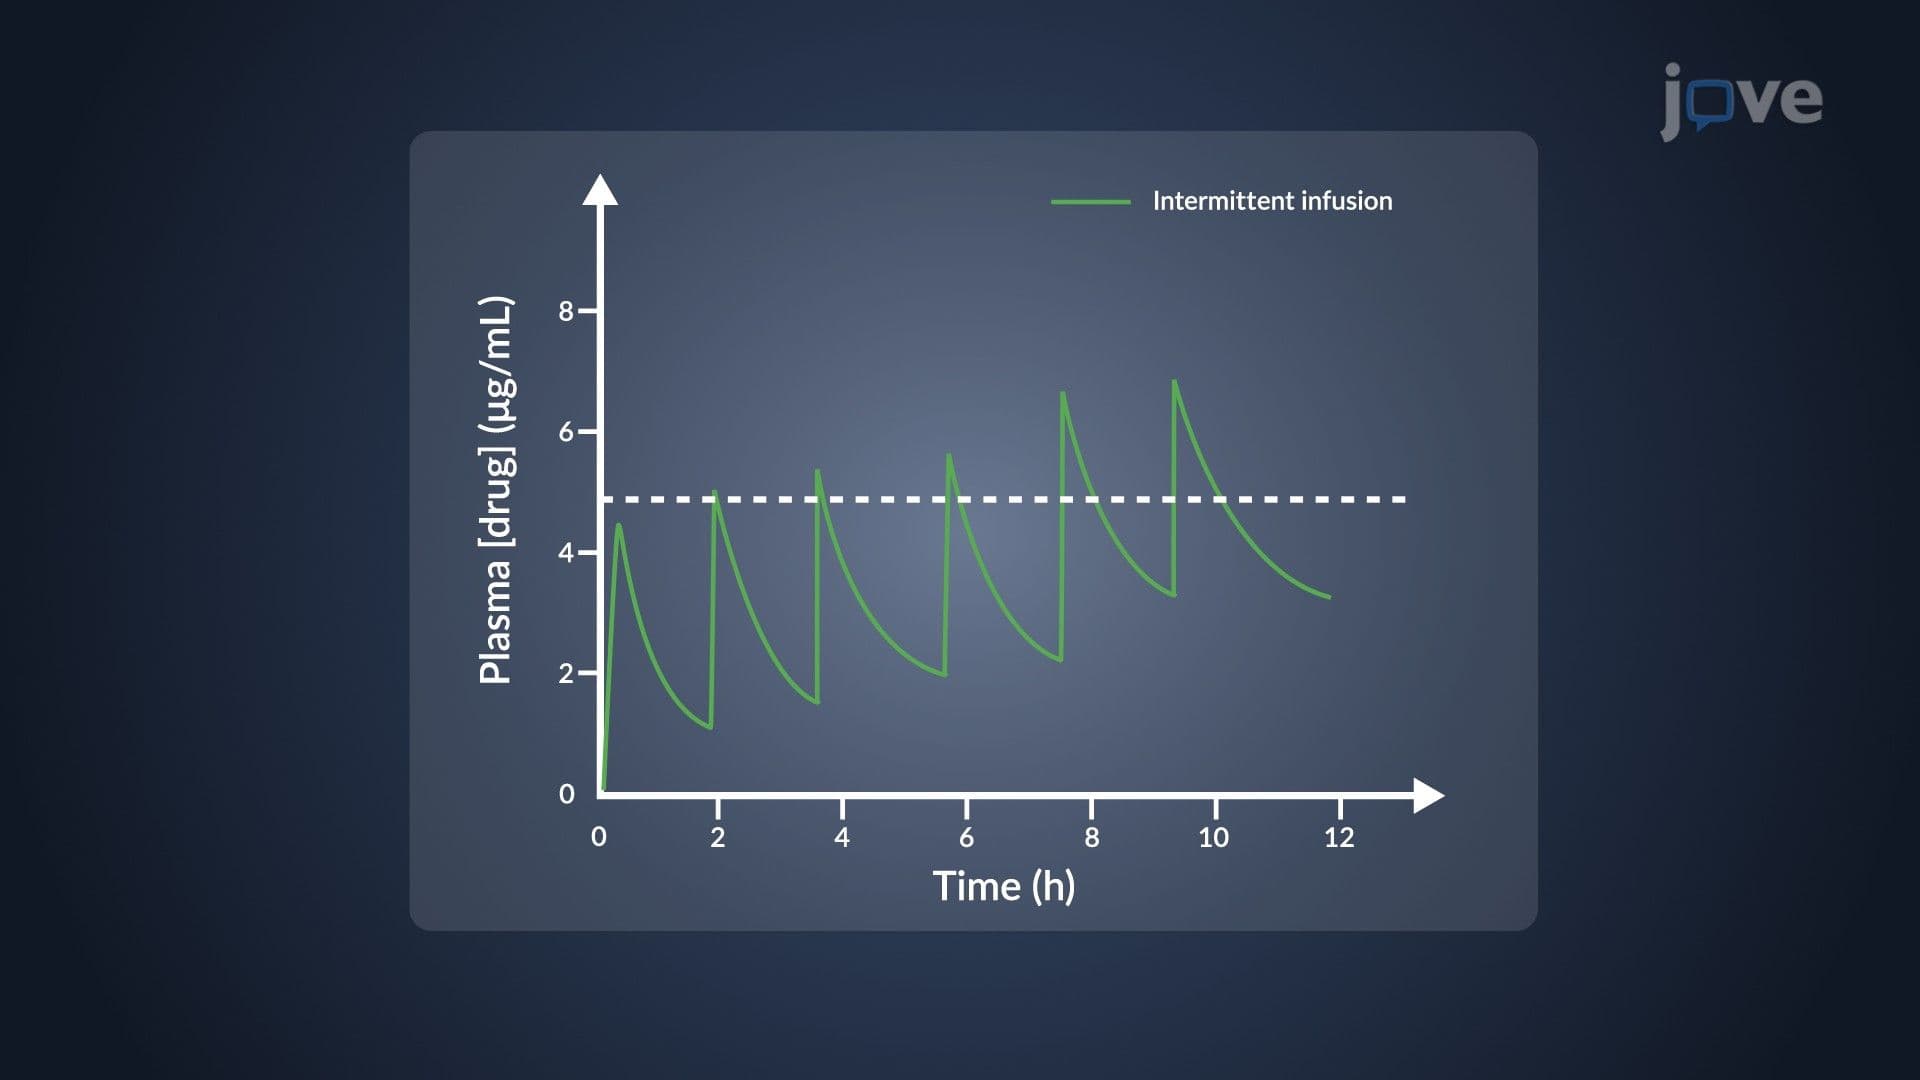
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:15
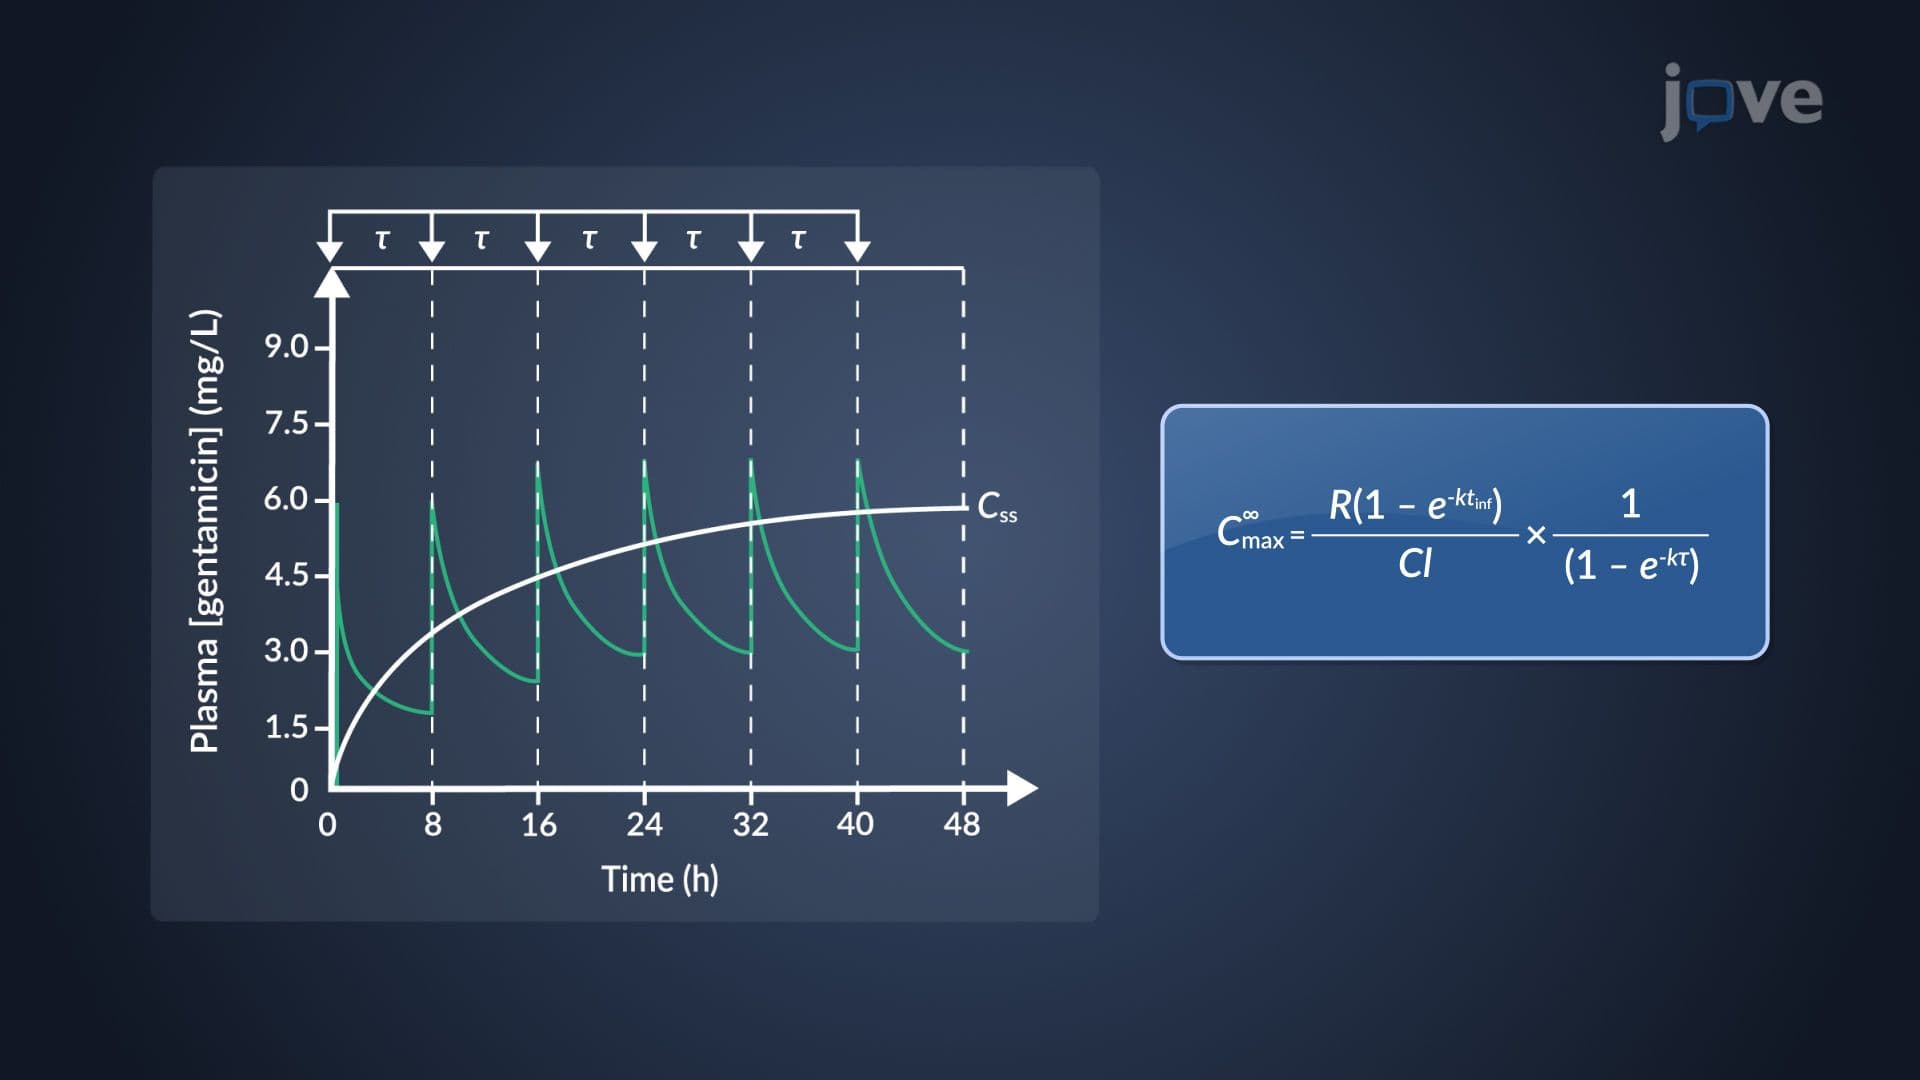
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations