Related Experiment Video
Updated: Aug 17, 2026
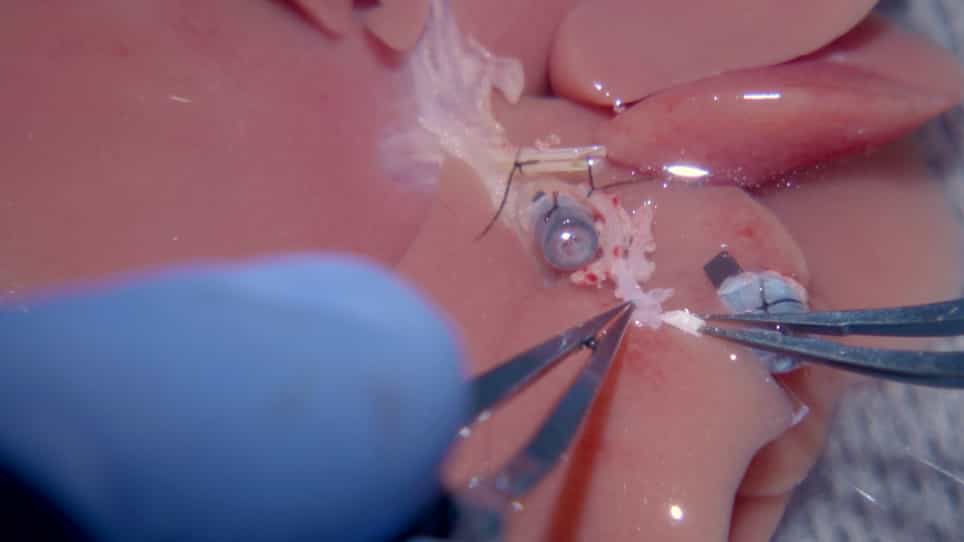

Reduced Complications after Arterial Reconnection in a Rat Model of Orthotopic Liver Transplantation
Published on: November 7, 2020
Repeated steroid pulse therapies in HCV-positive liver recipients: significant risk factor for HCV-related graft loss
M Bahra1, U P Neumann, D Jacob
1Department of Surgery, Charite Campus Virchow-Klinikum, Humboldt-University, Berlin, Germany. marcus.bahra@charite.de

Background:
The optimal immunosuppressive regimen for HCV-positive liver transplant recipients has not been established. Treatment for acute cellular rejection (ACR) with steroids is associated with increased viral replication and graft hepatitis. We retrospectively analyzed 232 patients after orthotopic liver transplantation (OLT) for HCV cirrhosis to determine the influence of methylprednisolone pulse therapy on long-term outcome after OLT.
Methods:
Two hundred thirty-two liver transplants were performed in HCV-positive recipients between 1989 and 2001. Median follow-up was 4.4 years and median age of patients was 53 years (range 15 to 72 years). Immunosuppression consisted of tacrolimus (Tac) or cyclosporine (CyA) in different protocols. All rejection episodes were histologically proven.
Results:
Twenty-eight of 232 (12.06%) graft losses were due to severe hepatitis C reinfection. Of 232 patients, 105 showed a minimum of one episode of ACR (45.25%). Of 232 patients, 71 (30.6%) received methylprednisolone pulse therapy once and 15 of 232 required OKT3 treatment for steroid-resistant rejection (6.4%). Of 232 patients, 19 (8.1%) required repeated steroid pulse therapy due to more than one episode of ACR. In patients with more than one episode of ACR, the risk of HCV-related graft loss was significantly enhanced (6/19, P < .05). The primary immunosuppression had no influence on the outcome in our data.
Conclusion:
Our data show that outcome of HCV-positive patients who require repeated steroid pulse therapy (RSPT) for ACR is significant worse than that in patients with a single pulse therapy. Therefore RSPT should be avoided in HCV-positive transplant recipients. New strategies to manage acute rejection are required for these patients.
Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
 01:28
Kidney Transplant I: Introduction
 01:16
Hepatic Drug Excretion: Influencing Factors