Related Experiment Video
Updated: Aug 17, 2026


Randomized Controlled Trial to Study the Acute Effects of Strength Exercise on Insulin Sensitivity in Obese Adults
Published on: December 1, 2023
Dose-response relationship of oral insulin spray in healthy subjects
Simona Cernea1, Miriam Kidron, Jay Wohlgelernter
1Diabetes Unit, Dept of Medicine, Hadassah Hospital, POB 12000, Jerusalem, Israel 91120.

Objective:
To evaluate the pharmacodynamic and pharmacokinetic properties and the dose-ranging effects of an oral insulin spray in comparison with subcutaneous regular insulin.
Research Design And Methods:
In this randomized, five-way, cross-over study, seven healthy volunteers were assessed under euglycemic clamp and received four different doses of oral spray and one dose of subcutaneous regular insulin.
Results:
The time to maximum insulin concentration was shorter for oral insulin than for subcutaneous insulin (25.9 +/- 9 vs. 145.7 +/- 49.5 min, P < 0.05). Maximum serum insulin levels (C(max)) were comparable between the subcutaneous and 20 puffs of oral insulin (39.1 +/- 19.6 vs. 34.0 +/- 7.4 microU/ml, NS). The Ins-AUC(0-120) (area under the curve from 0 to 120 min for serum insulin) (339.8 +/- 218, 681.3 +/- 407, and 1,586.7 +/- 8 microU/ml, P < 0.05) and C(max) (7.6 +/- 2.8, 16.4 +/- 9.3, and 39.1 +/- 19.6 microU/ml, P < 0.005) proved a dose-response relationship for the three doses of oral insulin (5, 10, and 20 puffs, respectively). Oral insulin had an earlier onset of action (31.7 +/- 12 vs. 77.8 +/- 3 min, P < 0.05), earlier peak (44.2 +/- 10 vs. 159.2 +/- 68 min, P < 0.05), and a shorter duration of action (85.1 +/- 25 vs. 319.2 +/- 45 min, P < 0.05) compared with subcutaneous insulin. The maximum metabolic effect (1.7 +/- 1.0, 3.09 +/- 1.7, and 4.6 +/- 1.5 mg . kg(-1) . min(-1), P < 0.05) and the GIR-AUC(0-120) (amount of glucose infused from 0 to 120 min) (106.7 +/- 74.3, 162.9 +/- 116.1, and 254 +/- 123 mg/kg) increased in a dose-dependent relationship for the three doses.
Conclusions:
Oral insulin was absorbed in direct relation to the amount given and had a faster onset and a shorter duration of action compared with subcutaneous regular insulin. A dose-response relationship in the absorption and metabolic effect of the oral insulin was noted.

Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:21
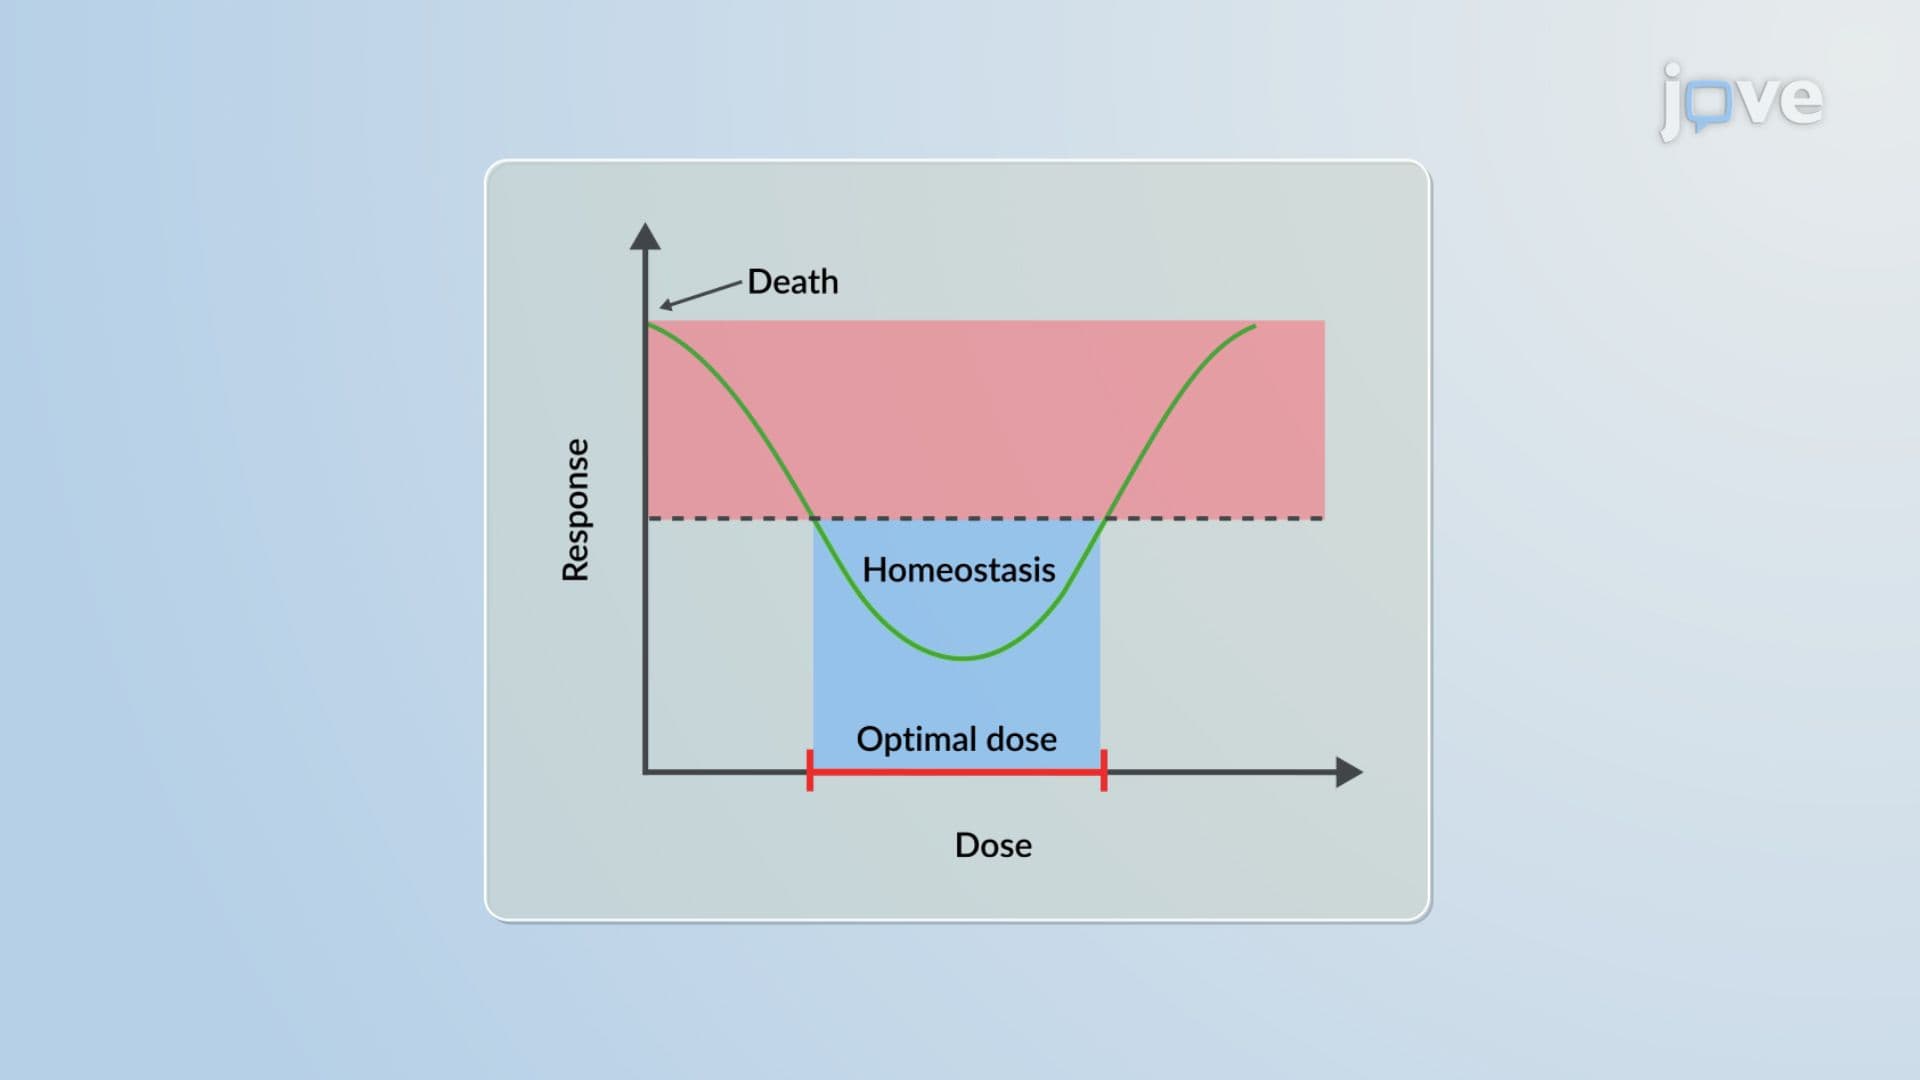
Dose Response Curve: Conventional Versus Nonmonotonic
 01:03
Dose-Response Relationship: Overview
 01:22
Dose-Response Relationship: Potency and Efficacy
 01:27
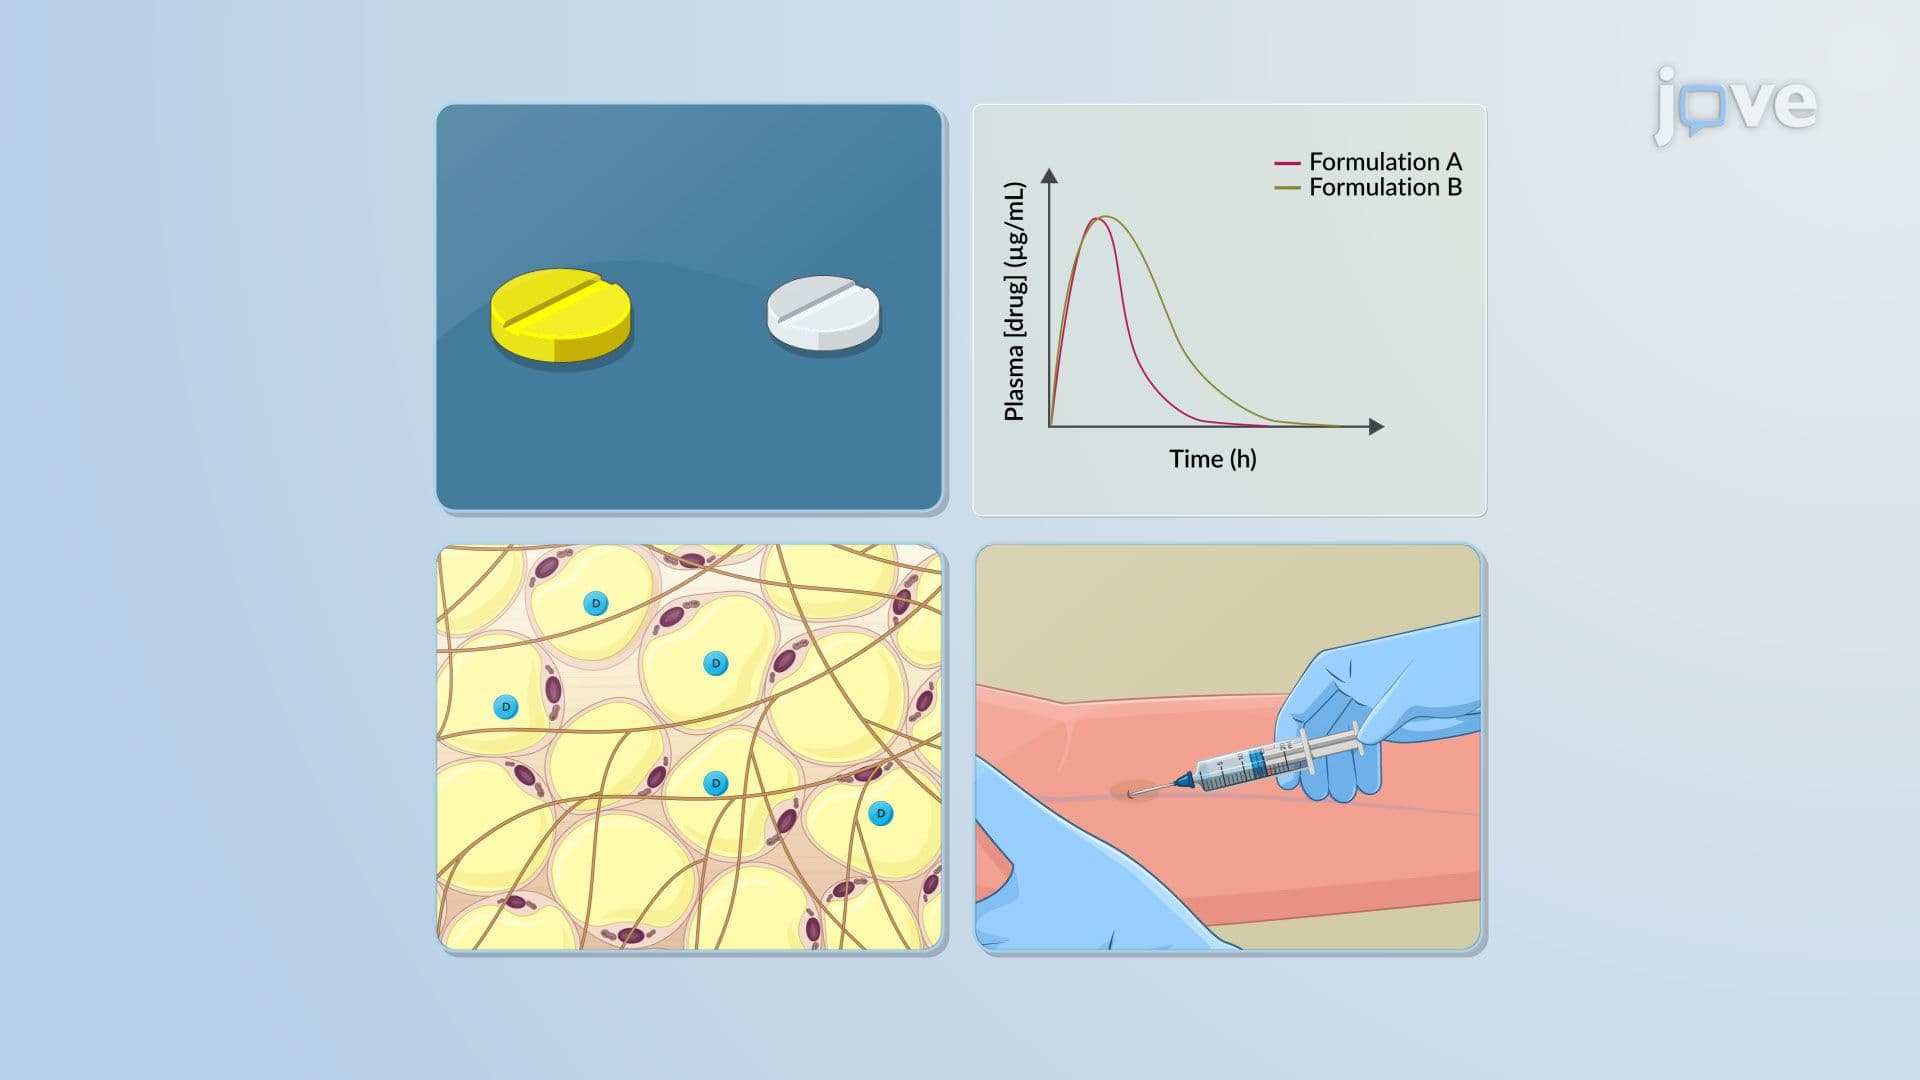
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship