Related Experiment Video
Updated: Aug 17, 2026


An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
Hormone replacement therapy (HRT) and endometrial morphology under consideration of the different molecular pathways
Lars-Christian Horn1, Manfred Dietel, Jens Einenkel
1Institute of Pathology, Division of Gynecologic Pathology, University of Leipzig, Liebigstrasse 26, Leipzig D-04103, Germany. hornl@medizin.uni-leipzig.de

Abstract:
The majority of modern hormone replacement therapy (HRT) regimens contain estrogen and progestogens, given either in a cyclical or continuous manner. About 15% of the endometrial biopsies taken from women on sequential HRT show proliferative activity including atypical endometrial hyperplasia in up to 1% of the cases. The majority of biopsies from women under continuous combined HRT show an endometrial atrophy. About 2-3% of these women will present proliferative activity, usually without atypical hyperplasia. Contrary to breast cancer, an increased risk of endometrial cancer has not been reported in the WHI- and HERS-studies. However, endogenous factors, such as obesity, diabetes mellitus, the distribution of estrogen receptors alpha and beta and genetic polymorphisms for receptors and enzymes might alter the endometrial stimulation under different types of HRT. There should be a liberal indication for endometrial biopsies in Hereditary Non-Polyposis Colorectal Cancer (HNPCC). HNPCC-patients under HRT as well as for ultrasonographic evaluation of the endometrium. The risk of atypical hyperplasias or carcinoma under unopposed estrogen-therapy varies from 2 to 10%. So, this kind of HRT should not be used in non-hysterectomised women. As far as the risk of endometrial cancer under any kind of HRT is concerned, the different molecular pathways of endometrial carcinogenesis (type 1 and 2 cancers) should be taken into account. The use of tibolone leaves the endometrium unaffected.

Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:22
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:30
Hormonal Control of the Ovarian Cycle
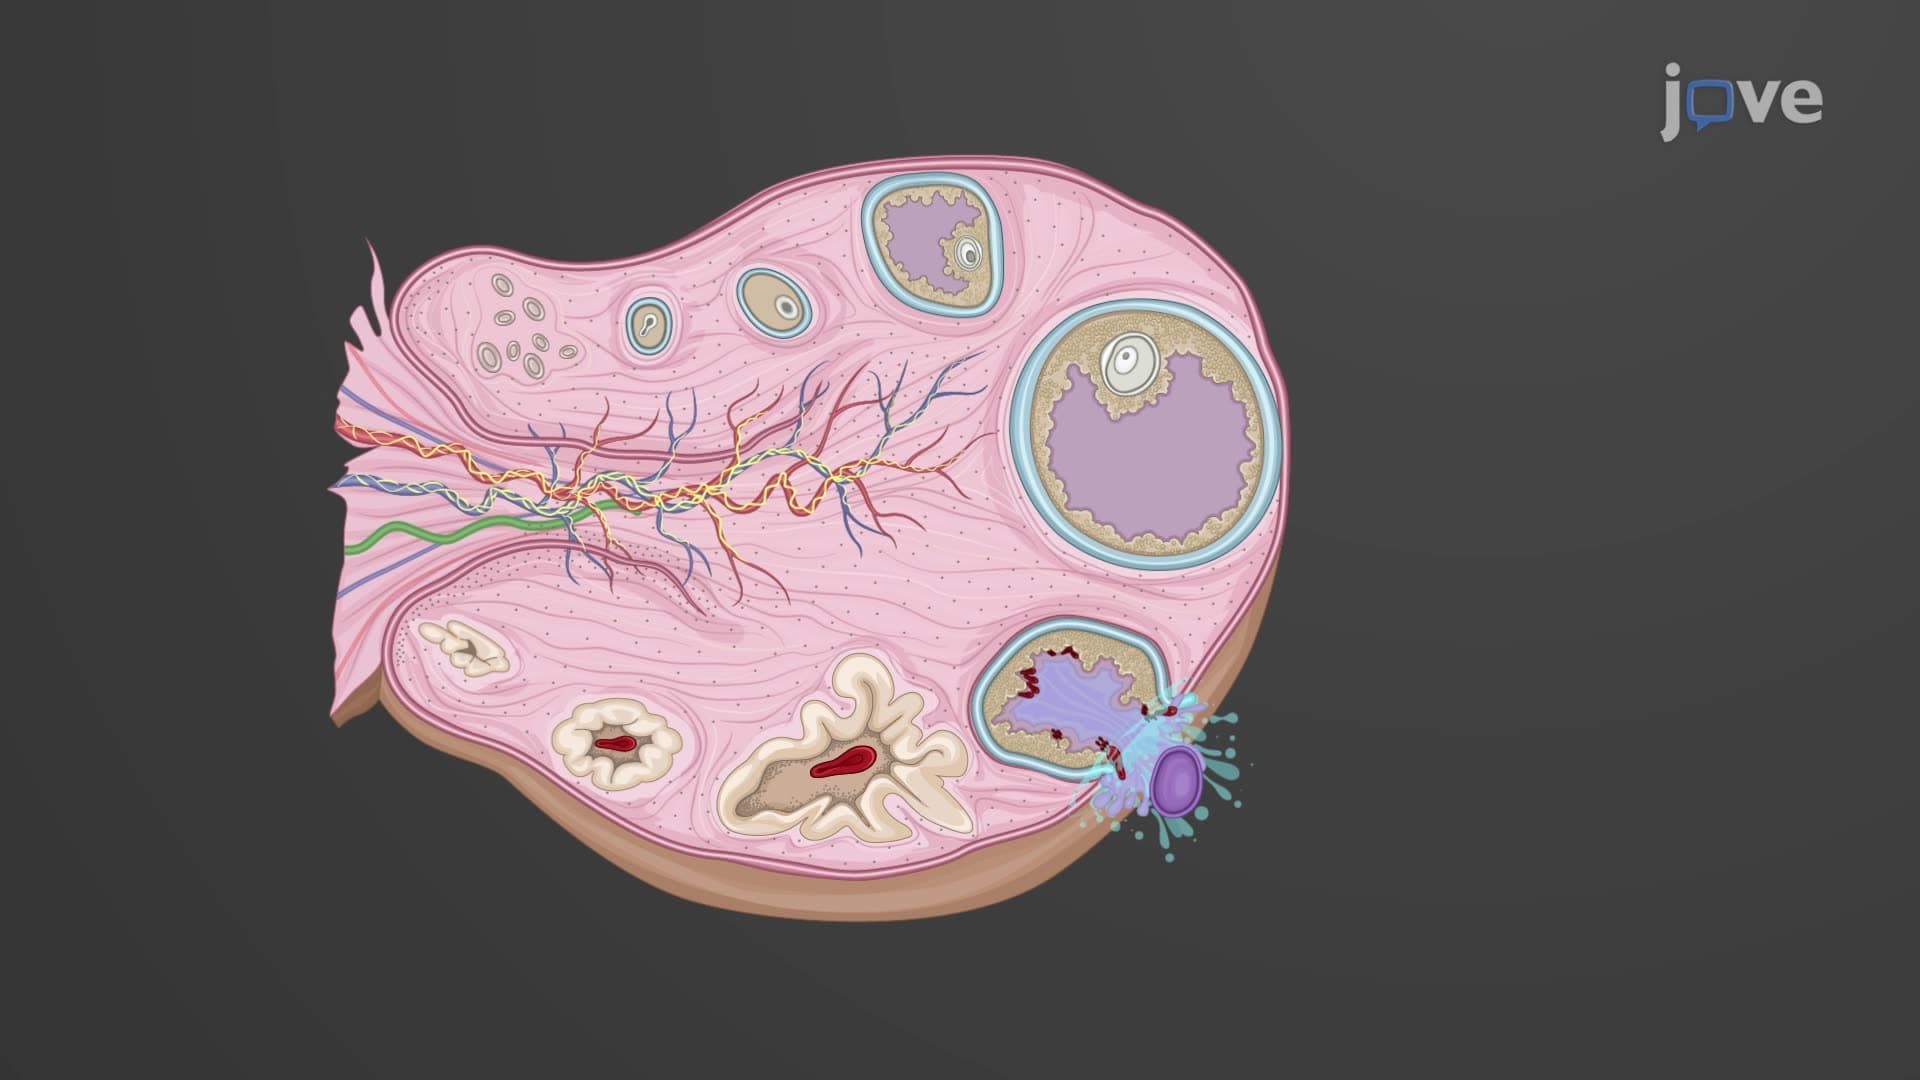
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a uterine...
 01:27
Ovarian Cycle