Related Experiment Video
Updated: Aug 17, 2026

Cooling or Warming the Esophagus to Reduce Esophageal Injury During Left Atrial Ablation in the Treatment of Atrial Fibrillation
Published on: March 15, 2020
Graded esophageal mucosal ablation with cryotherapy, and the protective effects of submucosal saline
1Center for Endoscopic Research, Training and Innovation (CERTAIN), Division of Gastroenterology and Hepatology, Department of Internal Medicine and Pathology, University of Texas Medical Branch, Galveston, Texas 77555-0762, USA. gsraju@utmb.edu

Background And Study Aims:
Knowledge about the extent of damage with endoscopic cryotherapy is of critical importance before its potential as an ablative therapy is explored. The aims of this study were to evaluate the extent of transmural esophageal necrosis at 48 hours after cryospraying for varying durations, using a novel device based on the Joule-Thomson effect and with carbon dioxide as the refrigerant gas, and to examine the role of submucosal injection of saline in preventing deeper injury.
Methods:
Cryospray was applied to several different segments of the esophagus for various lengths of time (15, 30, 45, 60, and 120 seconds) in a pig model. In another set of experiments performed subsequently, 2 ml of saline was injected into the submucosa and cryospray was applied for 60 seconds.
Results:
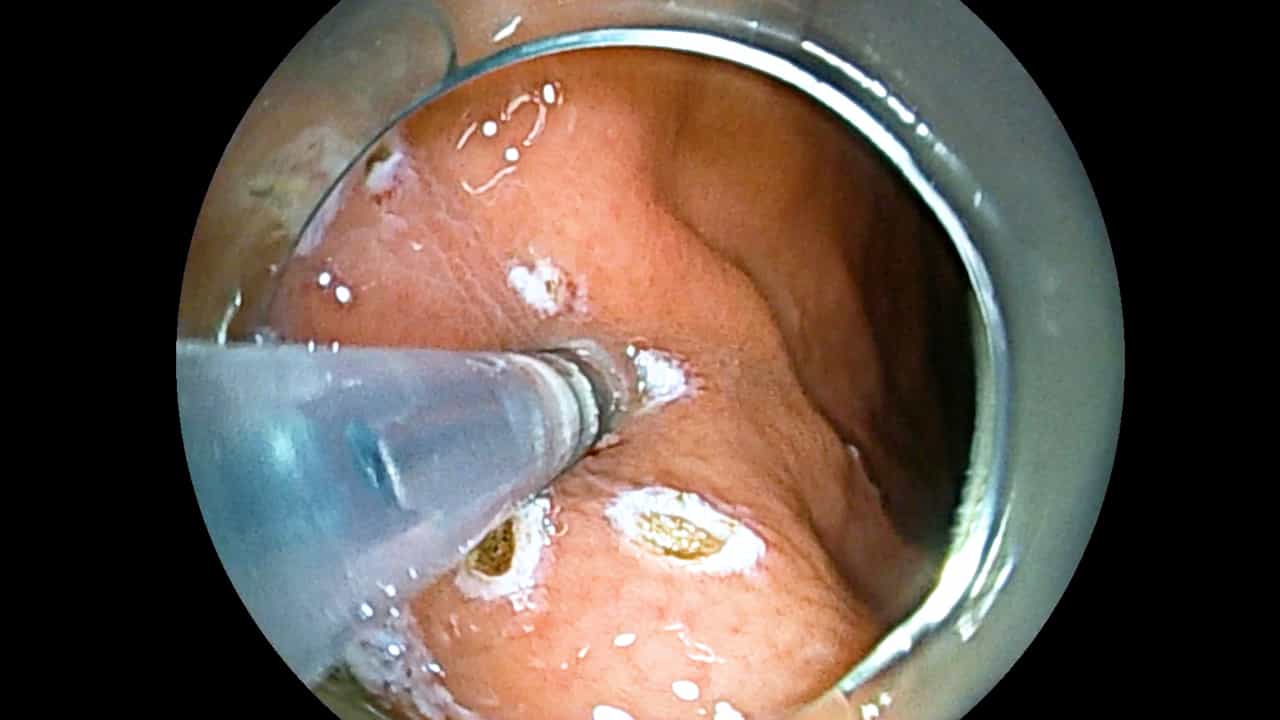
Esophageal cryotherapy resulted in a dose-dependent injury to the esophagus: esophageal necrosis was minimal or limited to the mucosa after 15 seconds of cryospraying, extended to involve the submucosa after 30 seconds of cryospraying, and involved the muscularis propria also after 45 seconds, with frank transmural necrosis found after 120 seconds of cryotherapy. Prior submucosal saline injection protected against muscular necrosis from prolonged cryotherapy.
Conclusions:
We have shown a dose-dependent effect of cryotherapy on esophageal mucosal ablation. When more extensive lesions are encountered, it may be advisable to consider using submucosal saline injections as an additional safeguard against deeper injury.
Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...