Related Experiment Video
Updated: Aug 17, 2026


A Modified Two Kidney One Clip Mouse Model of Renin Regulation in Renal Artery Stenosis
Published on: October 26, 2020
Everolimus treatment downregulates renocortical cyclooxygenase-2 expression in the rat kidney
Klaus Höcherl1, Corina Hensel, Bettina Ulbricht
1Institut für Pharmazie, Lehrstuhl für Pharmakologie und Toxikologie, Universität Regensburg, Universitätsstrasse 31, D-93040 Regensburg, Germany. klaus.hoecherl@chemie.uni-regensburg.de

Abstract:
Based on recent evidence that renal cyclooxygenase-2 (COX-2) gene expression is suppressed by immunosuppressive agents such as cyclosporin A (CsA), tacrolimus and dexamethasone, this study aimed to characterize the effect of the new immunosuppressant everolimus on COX-2 expression in the rat kidney. Oral application of everolimus (3 mg kg(-1) day(-1)) to male Sprague-Dawley rats (175-200 g; n=8) for 7 days lowered COX-2 expression in the rat renal cortex and outer medulla, while COX-2 expression in the inner medulla as well as COX-1 expression remained unaltered. Furthermore, everolimus decreased renocortical prostaglandin (PG) E(2) concentration. Everolimus also attenuated the stimulation of renocortical COX-2 expression by furosemide (12 mg day(-1) for 7 days; s.c. via osmotic minipumps), by low salt intake (0.02% NaCl, wt wt(-1)) or by a combination of low salt intake with the AT(1)-receptor antagonist valsartan (30 mg kg(-1) day(-1); oral). In line with these findings, everolimus decreased renocortical PGE(2) concentration during these treatment maneuvers. Everolimus moderately increased natriuresis and diuresis, while the urinary excretion of PGE(2), 6-keto PGF(1alpha) and thromboxane B(2) was decreased. These findings suggest that everolimus inhibits basal and also stimulated expression of renocortical COX-2 and of tissue prostanoid formation. Since inhibition of renal prostanoid formation by everolimus was associated by an increased rather than decreased natriuresis and diuresis, it appears as if everolimus also inhibits tubular salt and water resorption.
Insights
The immunosuppressant everolimus reduces cyclooxygenase-2 (COX-2) expression in rat kidneys, lowering prostaglandin E2 levels and affecting salt and water balance. This suggests everolimus impacts renal prostanoid formation and tubular resorption.
Area of Science:
- Nephrology
- Pharmacology
- Molecular Biology
Background:
- Renal cyclooxygenase-2 (COX-2) gene expression is known to be suppressed by immunosuppressive agents like cyclosporin A (CsA), tacrolimus, and dexamethasone.
- Understanding the effects of new immunosuppressants on renal pathways is crucial for managing patients.
Purpose of the Study:
- To investigate the impact of the novel immunosuppressant everolimus on cyclooxygenase-2 (COX-2) expression within the rat kidney.
- To characterize how everolimus influences prostaglandin E2 (PGE2) production and renal function.
Main Methods:
- Male Sprague-Dawley rats were administered oral everolimus (3 mg/kg/day) for 7 days.
- COX-2 and COX-1 expression levels were analyzed in different kidney regions (cortex, outer medulla, inner medulla).
- Renocortical PGE2 concentrations and effects of everolimus on stimulated COX-2 expression (furosemide, low salt, valsartan) were assessed.
Main Results:
- Everolimus significantly lowered COX-2 expression in the renal cortex and outer medulla, without affecting the inner medulla or COX-1 expression.
- Renocortical PGE2 concentration was decreased by everolimus.
- Everolimus attenuated stimulated COX-2 expression and PGE2 production under various conditions (furosemide, low salt intake).
- Moderate increases in natriuresis and diuresis were observed, alongside decreased urinary prostanoid excretion.
Conclusions:
- Everolimus inhibits both basal and stimulated expression of renal COX-2 and subsequent prostanoid formation.
- The observed increase in natriuresis and diuresis suggests everolimus may also inhibit tubular salt and water reabsorption.
- These findings highlight a novel mechanism of action for everolimus in the kidney.
Related Concept Videos
 01:28
Renal Drug Excretion: Tubular Secretion
 01:15
Renal Drug Excretion: Overview
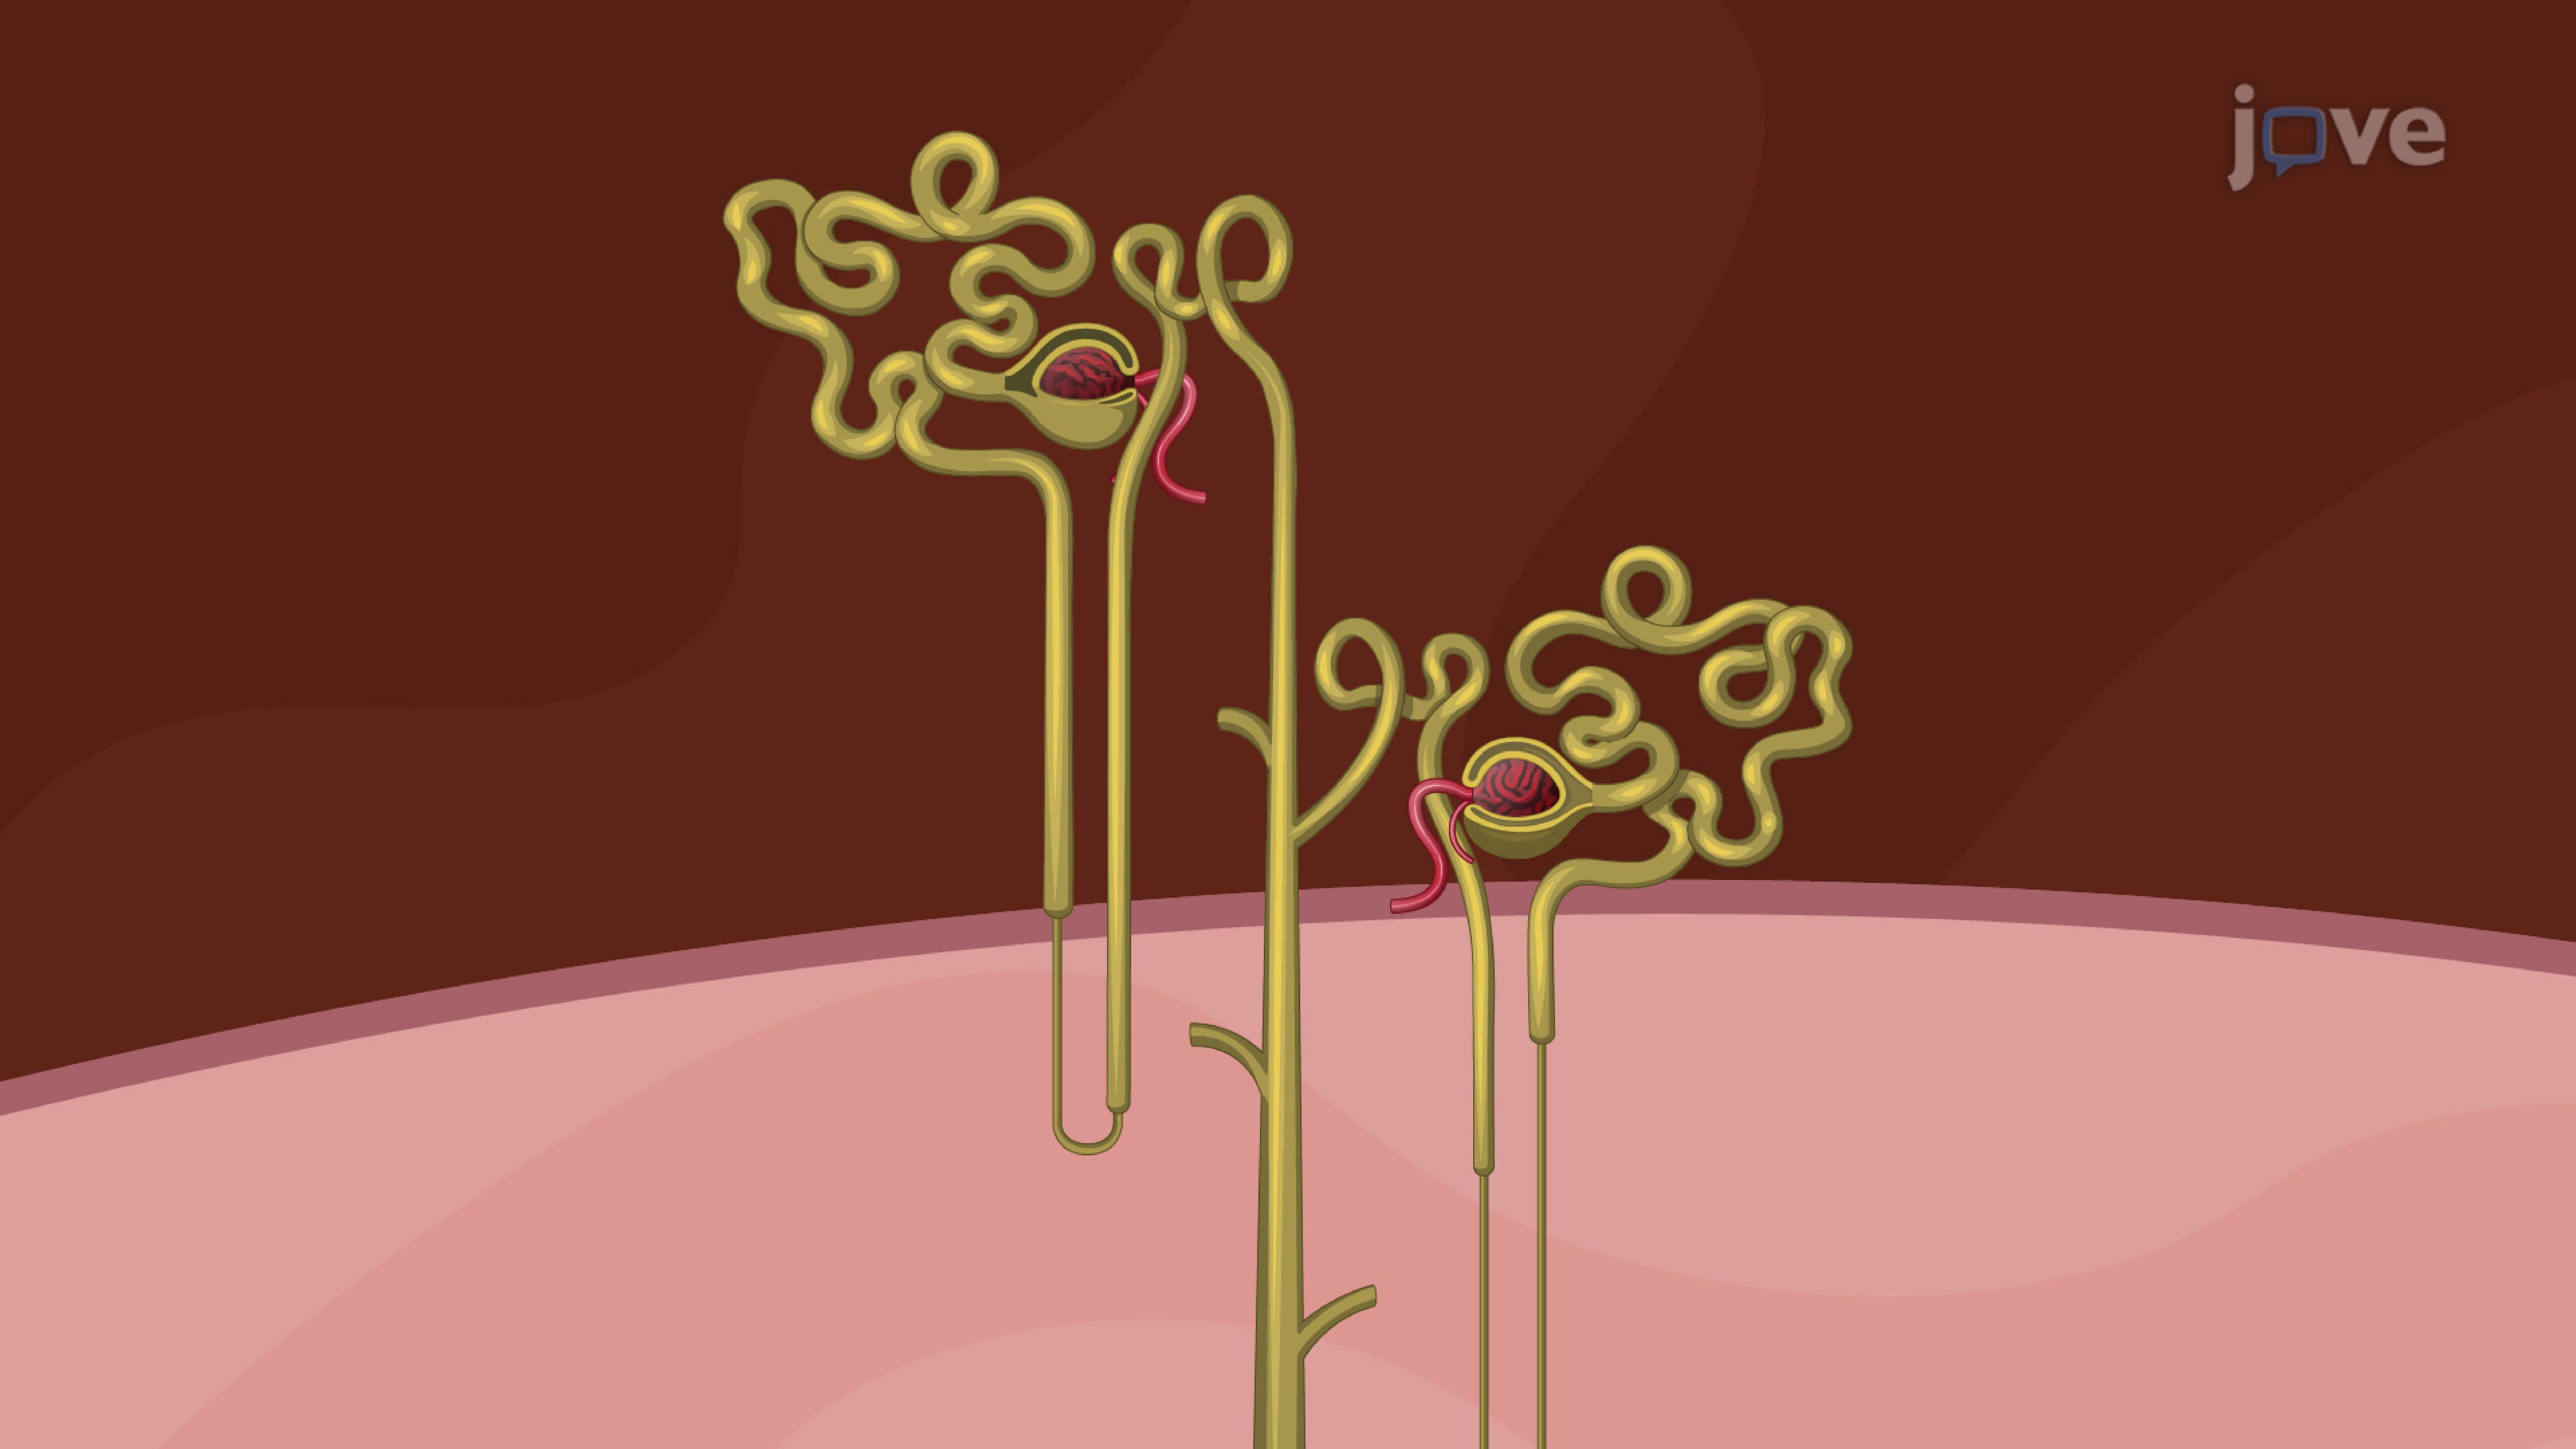
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System