Related Experiment Video
Updated: Aug 17, 2026


Trans-Tympanic Drug Delivery for the Treatment of Ototoxicity
Published on: March 16, 2018
Asphyxia and depolarization increase adenosine levels in perilymph
Richard P Bobbin1, Sanford C Bledsoe
1Kresge Hearing Research Laboratory, Department of Otolaryngology, Louisiana State University Health Sciences Center, New Orleans, LA 70112-2234, USA. rbobbi@lsuhsc.edu

Abstract:
Extracellular adenosine has been suggested as a modulator of cochlear function. To date the release of adenosine into the extracellular spaces of the cochlea has not been demonstrated. Therefore, experiments were designed to examine whether adenosine release into perilymph could be detected in response to depolarization by high potassium concentrations or in response to asphyxia. For this purpose, the perilymph compartment of guinea pigs was perfused with an artificial perilymph and the effluent assayed for ATP, ADP, AMP and adenosine. Results indicate that potassium induced a slight, significant increase and asphyxia induced a very large, significant increase in adenosine levels in perilymph effluent. No changes in the levels of the other compounds were measured. It is concluded that depolarization and asphyxia can induce the release of adenosine into perilymph.
More Related Videos
 11:29
HPLC-based Assay to Monitor Extracellular Nucleotide/Nucleoside Metabolism in Human Chronic Lymphocytic Leukemia Cells
Published on: July 20, 2016
 10:41
Laser-Induced Action Potential-Like Measurements of Cardiomyocytes on Microelectrode Arrays for Increased Predictivity of Safety Pharmacology
Published on: September 13, 2022
Related Concept Videos
 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:21
Cytotoxic Edema: Pathophysiology
 01:28
Action Potential: Phases of Stimulation
Resting Phase:
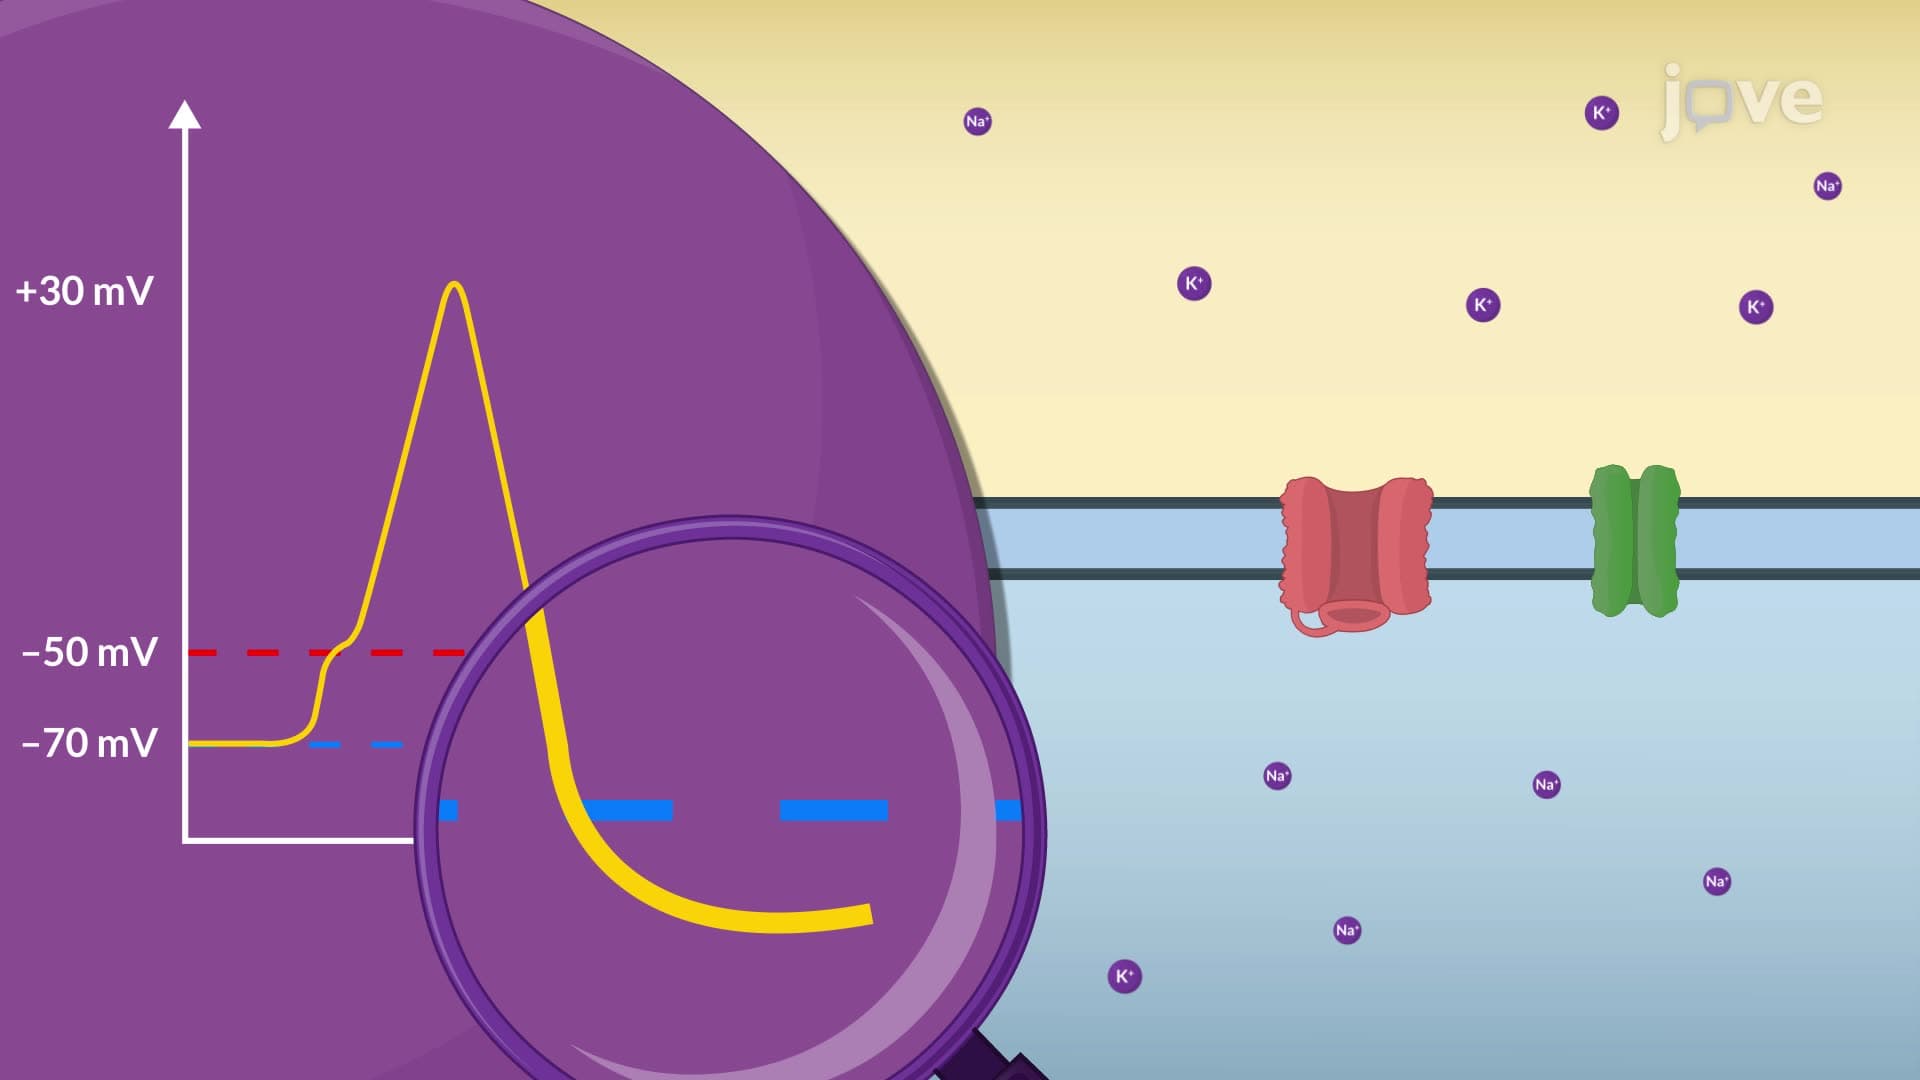
In this phase, the cell's membrane is at its resting potential, typically around -70 millivolts (mV) for neurons. Inside the cell, there is a higher concentration of potassium ions (K+) and a lower concentration of sodium ions (Na+). Voltage-gated sodium channels are closed, and...
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers