Related Experiment Video
Updated: Aug 17, 2026
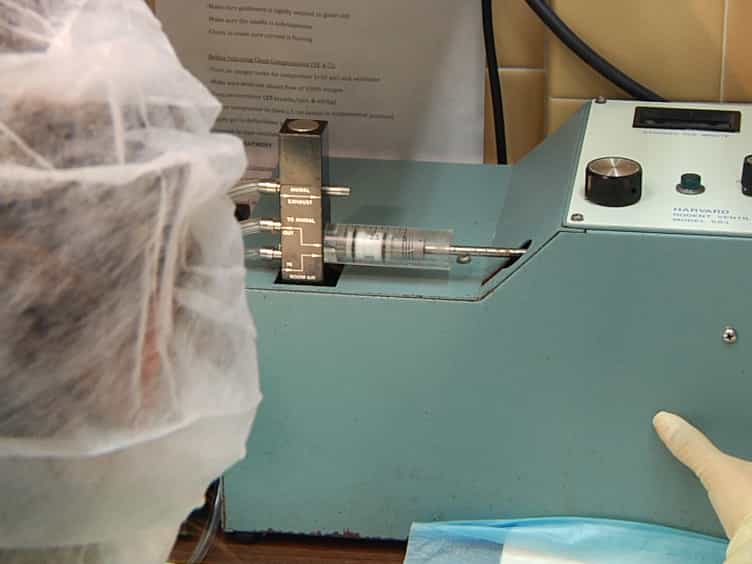
A Rat Model of Ventricular Fibrillation and Resuscitation by Conventional Closed-chest Technique
Published on: April 26, 2015
Carvedilol mitigates adverse effects of epinephrine during cardiopulmonary resuscitation
Lei Huang1, Max Harry Weil, Shijie Sun
1The Institute of Critical Care Medicine, Palm Springs, CA, USA.

Introduction:
Earlier studies have implicated the adverse effects of beta- and alpha(1)-adrenergic receptors during cardiopulmonary resuscitation (CPR). Because carvedilol is both a nonselective beta- and alpha1-selective adrenergic receptor-blocking agent, we hypothesized that pretreatment with carvedilol would convert the actions of epinephrine to that of a selective alpha2-agonist.
Methods:
Ventricular fibrillation (VF) was induced in Sprague-Dawley rats weighing approximately 500 g. Animals were randomized to 4 groups of 5 animals each: (1) placebo pretreatment and epinephrine treatment, (2) carvedilol pretreatment and placebo treatment, (3) carvedilol pretreatment and epinephrine treatment, and (4) placebo pretreatment and placebo treatment. Carvedilol (50 microg/kg) was injected as a bolus into the right atrium 15 minutes before VF was induced. VF was untreated for 8 minutes, after which CPR (chest compression and mechanical ventilation) was begun. Epinephrine (30 microg/kg) was injected into the right atrium 2 minutes after the start of CPR. Electrical defibrillation was attempted after 14 minutes of VF.
Results:
All but 2 animals were successfully resuscitated. Approximately equivalent increases in coronary perfusion pressure from 23 +/- 1 mm Hg to 30 +/- 3 mm Hg were observed after the injection of epinephrine independently of carvedilol pretreatment. Carvedilol pretreatment followed by epinephrine treatment reduced early postresuscitation ventricular ectopy (116 +/- 147 vs 834 +/- 380, P < .01) and minimized increases in arterial blood lactate at 5 minutes after resuscitation (10.9 +/- 2.1 mmol/L vs 17.4 +/- 3.5 mmol/L, P < .01). The postresuscitation cardiac index measured 4 hours later was increased (307 +/- 43 mL x min(-1) x kg(-1) vs 210 +/- 6 mL x min(-1) x kg(-1), P < .05). Left ventricular diastolic pressures were decreased (6 +/- 1 vs 14 +/- 1 mm Hg, P < .05). Animals pretreated with carvedilol survived longer (71 +/- 1 vs 45 +/- 22 hours, P < .05) and with less postresuscitation neurologic deficit.
Conclusion:
After beta- and alpha1-adrenergic blockade with carvedilol before inducing cardiac arrest, epinephrine administered during CPR yielded better postresuscitation myocardial and neurologic functions and significantly increased postresuscitation survival.
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:22
Heart Failure Drugs: β-Blockers
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...