Related Experiment Video
Updated: Aug 17, 2026

An Immunofluorescent Method for Characterization of Barrett’s Esophagus Cells
Published on: July 20, 2014
Barrett esophagus: risk factors for progression to dysplasia and adenocarcinoma
Stefan Oberg1, Jörgen Wenner, Jan Johansson
1Department of Surgery, Lund University Hospital, Lund, Sweden. stefan.oberg@kir.lu.se

Objective:
To evaluate risk factors for dysplasia and adenocarcinoma development in nondysplastic Barrett mucosa.
Summary Background Data:
The risk for patients with Barrett esophagus to develop esophageal adenocarcinoma is low, and most patients undergoing surveillance will not develop malignancy. Identification of risk factors may allow for more rational surveillance programs in which patients are stratified according to their individual risk of progressing to dysplasia and invasive adenocarcinoma.
Methods:
The development of dysplasia and esophageal adenocarcinoma was studied during long-term endoscopic and histologic surveillance in 140 patients with Barrett esophagus free from dysplasia. Risk factors for progression to dysplasia and adenocarcinoma were evaluated.
Results:
Median follow-up was 5.8 years. Forty-four patients (31.4%) developed low-grade dysplasia and 7 patients (5%) developed high-grade dysplasia or esophageal adenocarcinoma. Dysplasia development was significantly less common after antireflux surgery compared with conventional medical therapy. Low-grade dysplasia (relative risk = 5.5; 95% confidence interval, 1.1-28.6) and long duration of reflux symptoms (relative risk = 1.3; 95% confidence interval, 1.2-1.7) were independently associated with an increased risk of developing high-grade dysplasia or esophageal adenocarcinoma.
Conclusions:
Successful antireflux surgery protects the Barrett mucosa from developing high-grade dysplasia and esophageal adenocarcinoma, possibly by better control of reflux of gastric contents. Low-grade dysplasia is the only clinically useful risk factor that permits stratification of the surveillance intervals according to the risk of the individual patient.


Related Concept Videos
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:24
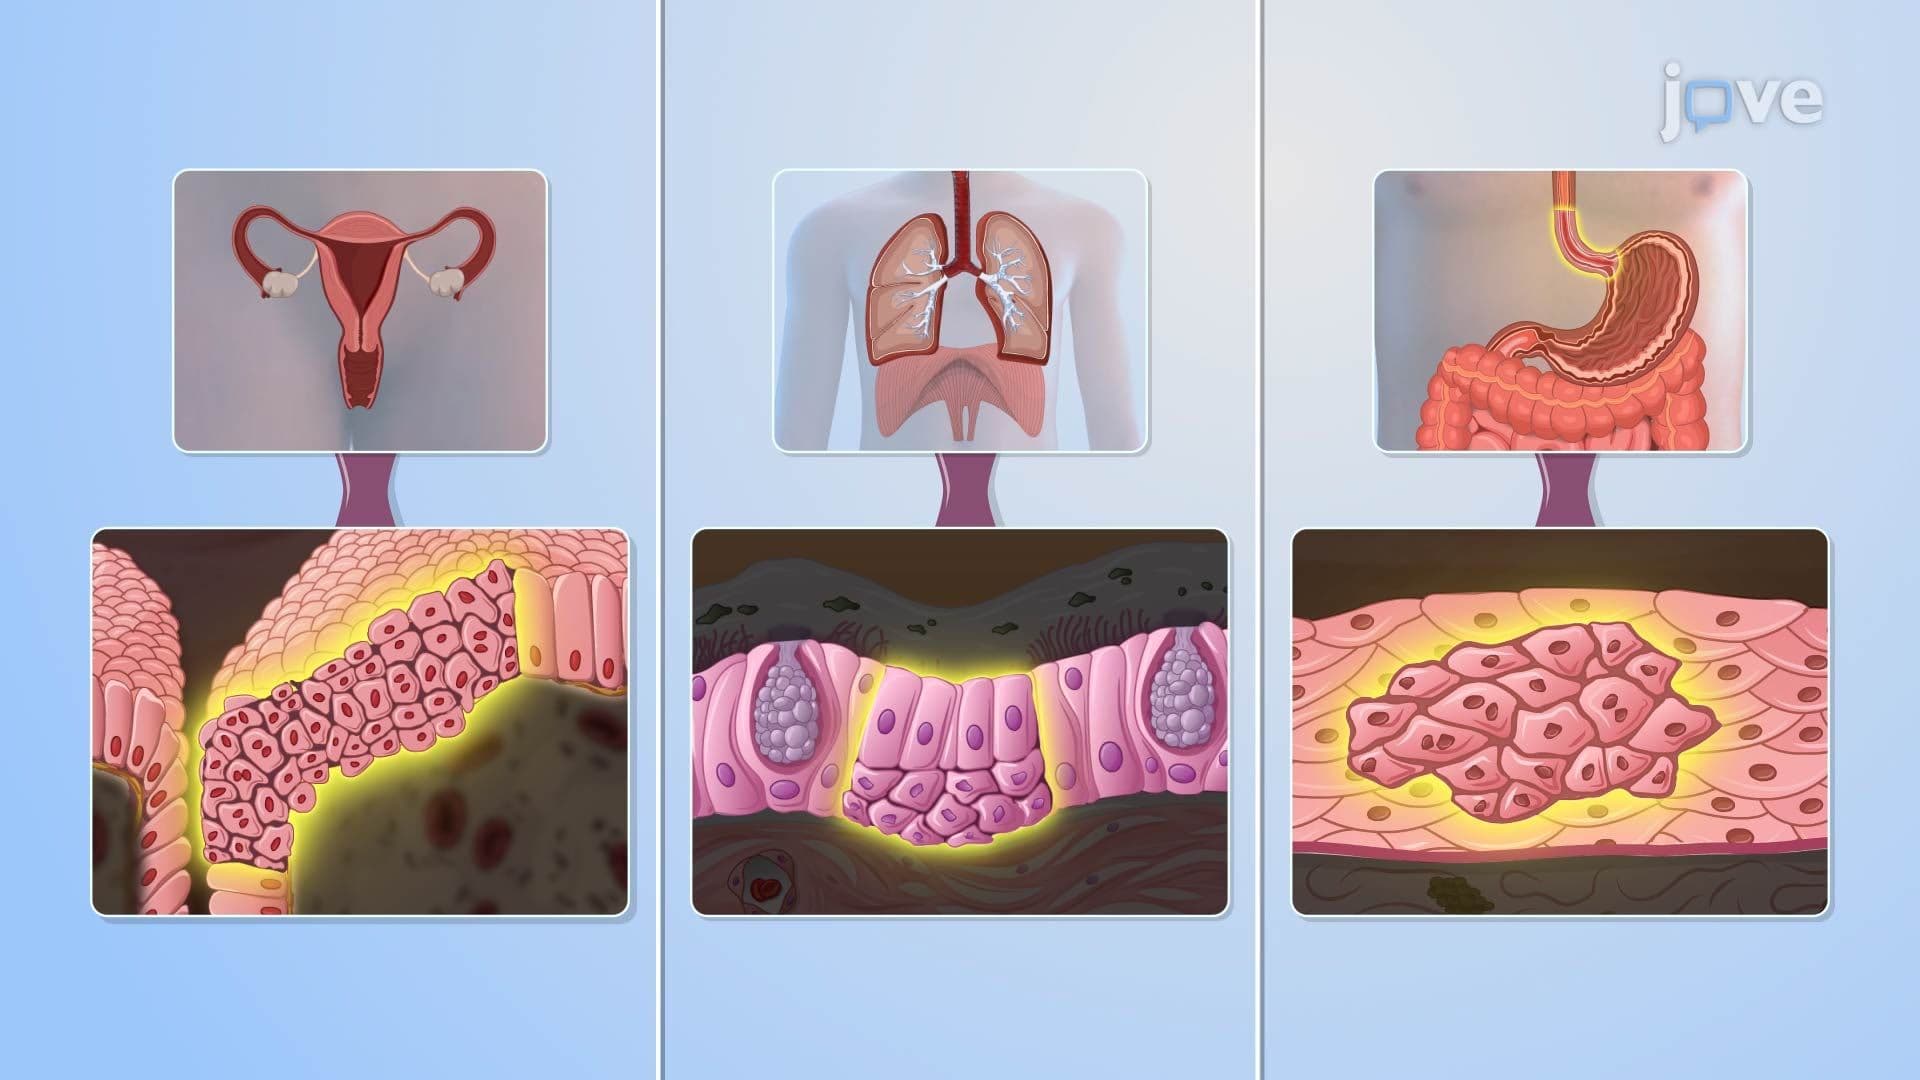
Cellular Adaptation IV: Dysplasia and Metaplasia
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:25
Gastroesophageal Reflux Disease
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...