

Clinical predictors of cardiac events in patients with isolated syncope and negative electrophysiologic study
Antoine Da Costa1, Jean-Luc Gulian, Cécile Romeyer-Bouchard
1Division of Cardiology, University Jean Monnet of Saint-Etienne, 42000 Saint-Etienne, France. dakosta@aol.com

Insights
For patients with unexplained syncope, an abnormal electrocardiogram (ECG) is the sole predictor of significant cardiac events. This finding aids in risk stratification for cardiac arrhythmias after initial negative diagnostic tests.
Area of Science:
- Cardiology
- Electrophysiology
- Diagnostic Medicine
Background:
- Syncope and near syncope of unknown origin pose diagnostic challenges.
- Initial evaluations and electrophysiologic testing (EPS) often yield inconclusive results for risk stratification.
- Implantable Holter monitoring is typically reserved for recurrent episodes.
Purpose of the Study:
- Identify predictors of significant cardiac rhythmic events in patients with syncope after negative diagnostics and EPS.
- Define significant cardiac events, including symptomatic atrioventricular (AV) block, conduction abnormalities, ventricular arrhythmias, and sudden death.
Main Methods:
- Retrospective analysis of 329 patients undergoing EPS for syncope or presyncope (1997-2001).
- Data included patient demographics, medical history, and electrocardiogram (ECG) findings.
- Follow-up averaged 31 months to assess cardiac rhythmic events.
Main Results:
- Among 305 patients with follow-up, 5% experienced significant cardiac rhythmic events.
- Univariate analysis linked structural heart disease, ECG abnormalities, and left ventricular ejection fraction (LVEF) to events.
- Multivariate analysis identified ECG abnormality as the only independent predictor of events (10.6% risk in this subset).
Conclusions:
- An electrocardiogram (ECG) abnormality is the sole independent predictor of significant arrhythmic events in patients with a single episode of syncope and negative EPS.
- This finding is crucial for risk assessment in unexplained syncope cases.
Background:
Patients with syncope or near syncope of unknown etiology represent a great challenge to cardiologists. An initial symptomatic episode triggers a series of diagnostic analysis which remain unsatisfactory when negative. More invasive tools such as electrophysiologic testing yield only partial answers to risk stratification while the complementary implantable holter diagnostics are not usually considered until a recurrent episode is documented.
Objective:
This study targets predictors of significant cardiac rhythmic events in patients with a reported episode of syncope or near syncope presenting with negative diagnostics and electrophysiologic study results (EPS). A significant cardiac rhythmic event was defined as a combined end-point of (1) symptomatic AV block; (2) symptomatic conduction abnormalities requiring pacemaker therapy; (3) symptomatic sustained ventricular arrhythmia; and (4) sudden death.
Methods:
All patients undergoing EPS after a first episode of syncope or presyncope between January 1997 and December 2001 were included for analysis. The study population consisted of 329 pts (42.6% women), 21 to 96 years old (mean 70+/-15 years) referred for an EP study for syncope or near syncope.
Results:
Of the 329 patients who underwent EPS, 305 (92.7%) had follow-up data. The population, mean age 70 (+/- 15 years) and composed of 42% women, presented with hypertension (51.5%), diabetes mellitus (14.4%), hypercholesterolemia (30%), tobacco use (35%), a familial history of coronary heart disease (22%), history of stroke (4%), history of MI (12%), history of atrial fibrillation (10%), structural heart disease (17.4%), left ventricular ejection fraction 61 (+/- 11%) and ECG abnormalities (37%). These anomalies included right (RBBB) or left (LBBB) bundle branch blocks, left anterior fascicular block (LAFB), left posterior fascicular block (LPFB), bifascicular block (RBBB+LAFB) and traces of myocardial infarction. The mean follow-up was 31+/-20 months with 5% of patients recording significant cardiac rhythmic events (15/305): AV block requiring pacemaker therapy in 7 patients, sinus dysfunction in 4, sudden death in 3 and ventricular tachycardia in 1. Univariate analysis reveals structural heart disease, ECG abnormalities and LVEF associated with the risk of significant cardiac rhythmic events defined by the combined end-point. Multivariate analysis using a Cox model found that the only independent predictor of events was an ECG abnormality. The long-term risk of significant event in the subset with ECG abnormalities is of 10.6% (12/113). If unexplained syncope recurrence was included in the combined end-point, ECG abnormality and LVEF were both determinants with a 13.3% (15/113) risk of a arrhythmic events analysis in the subset of patients presenting with ECG abnormalities and Cox model found ECG abnormality as the only independent predictor of event.
Conclusions:
This study demonstrated that an ECG abnormality is the only predictive variable associated with a significant arrhythmic event in patients with a lone episode of syncope or near syncope and a negative EPS.
Related Concept Videos
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:26
Exercise Stress Test
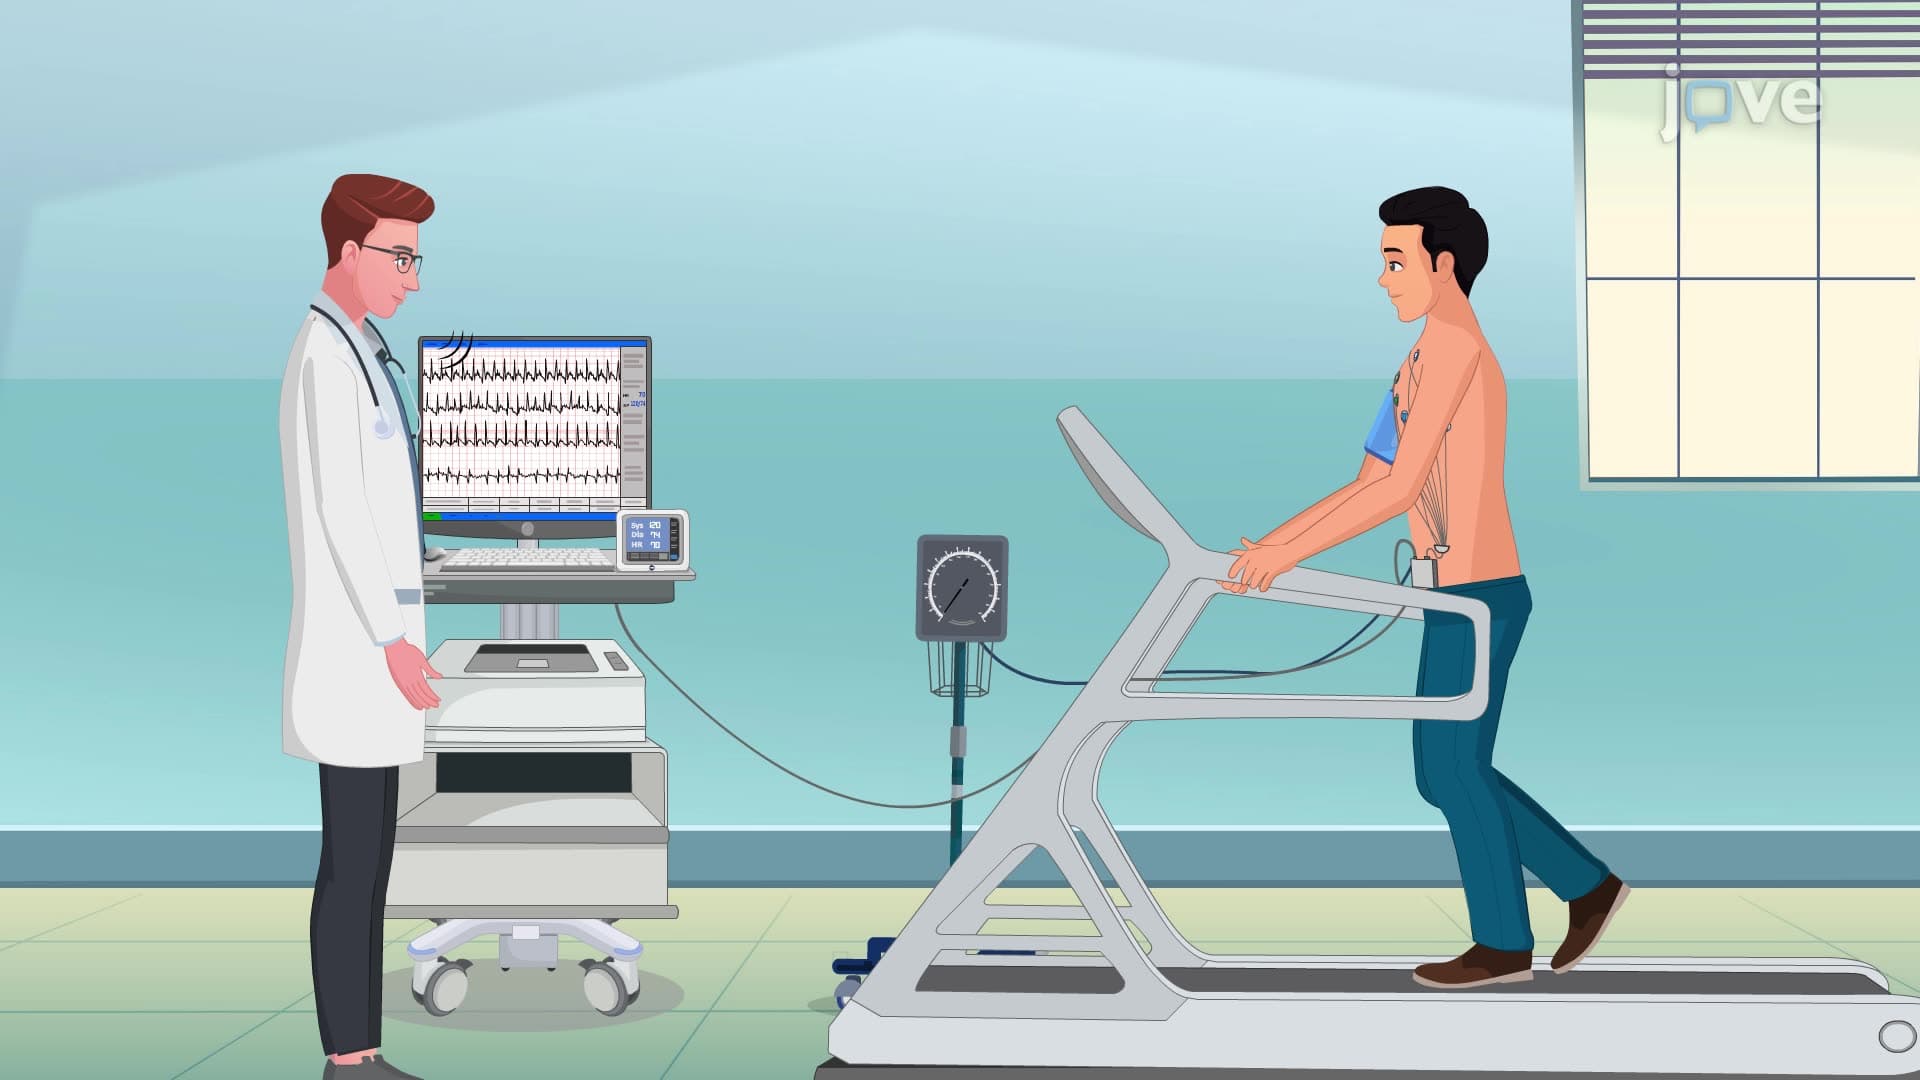
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:19
Electrophysiology of Normal Cardiac Rhythm