Related Experiment Video
Updated: Aug 17, 2026
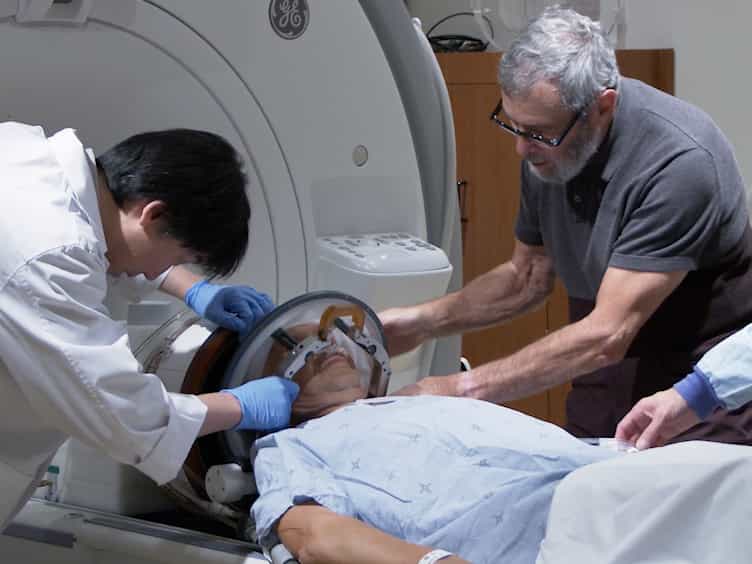

MRI-guided Focused Ultrasound Thalamotomy for Patients with Medically-refractory Essential Tremor
Published on: December 13, 2017
The impact of ventrolateral thalamotomy on high-frequency components of tremor
Christian Duval1, Antonio P Strafella, Abbas F Sadikot
1Faculty of Applied Health Science, Brock University, 500 Glenridge Avenue, St Catharines, Ont., Canada H2S 3A1. cduval@brocku.ca

Objective:
The present study assessed the impact of ventrolateral (VL) thalamotomy on the high-frequency components of tremor in patients with Parkinson's disease (PD).
Methods:
Tremor was recorded prior to, and 7 days post-surgery using a laser displacement sensor. In addition, tremor was recorded in 10 age-matched patients with PD showing low amplitude tremor (named PD controls) and in 10 age-matched control subjects. Tremor recordings in patients were performed after a 12h withdrawal from anti-Parkinsonian drugs. Tremor characteristics such as amplitude, median power frequency (MPF) and power dispersion (a measure of concentration of power in the frequency domain) were assessed for all groups (i.e. controls, PD controls, pre-surgery and post-surgery).
Results:
All tremor characteristics were similar between controls and PD controls. Tremor amplitude was significantly reduced post-surgery, to become statistically similar to that of controls and PD controls. However, MPF and power dispersion remained lower post-surgery, indicating that although there was normalization of tremor amplitude, tremor showed systematically slower oscillations after the surgical procedure. In order to eliminate amplitude as a possible confounding factor, epochs of post-surgical tremor (5s in duration) were paired for equal amplitude with 5s tremor epochs from matched controls. Results show once again that MPF and power dispersion were lower post-surgery compared to controls. In addition, when amplitude of power was compared within specific frequency bands (0-3.5, 3.5-7.5, 7.5-12.5, 12.5-16.5, 16.5-30 and 30-45), power regained normal values at frequencies below 7.5 Hz. Power within higher frequency bands was systematically lower, indicating that the surgical procedure had an impact on high-frequency components of tremor.
Conclusions:
Results from the present study showed that VL thalamotomy reduced tremor amplitude by selectively targeting centrally driven components of PD tremor. The high-frequency component of physiological tremor failed to emerge after amplitude normalization.
Significance:
The thalamus should then be considered as an important component of the generation and/or propagation of high-frequency components of physiological tremor.