Related Experiment Video
Updated: Aug 17, 2026


An Open-Source Normothermic Perfusion System Designed for Research Scientists
Published on: July 18, 2025
Derivation of meropenem dosage in patients receiving continuous veno-venous hemofiltration based on pharmacodynamic
Joseph L Kuti1, David P Nicolau
1Center for Anti-Infective Research and Development, Hartford Hospital, Hartford, CT 06102-5037, USA.

Background:
Dosage recommendations for antibiotics in patients receiving continuous veno-venous hemofiltration (CVVH) should be based on pharmacodynamic requirements. For meropenem, this would be achieving appropriate time above the minimum inhibitory concentration (T > MIC). We employed Monte Carlo simulation to calculate the bactericidal target attainment for various dosing regimens of meropenem against Pseudomonas aeruginosa and Acinetobacter species.
Methods:
Target attainment at 40% T > MIC was calculated for 5,000 simulated subjects receiving meropenem 1,000 mg every 12 and 8 h, and 500 mg every 12, 8 and 6 h. Pharmacokinetics were extrapolated from primary literature sources utilizing similar methods of CVVH. MIC data for P. aeruginosa and Acinetobacter species were derived from the US 2003 MYSTIC study. Target attainment at the breakpoint of 4 microg/ml was also calculated.
Results:
Only regimens of 1,000 mg every 8 h and 500 mg every 6 h essentially achieve 100% target attainment at the breakpoint. However, due to higher peak concentrations, 1,000 mg every 8 h is able to attain improved target attainment against more resistant populations of P. aeruginosa and Acinetobacter species, thus providing the greatest probability of bactericidal exposure.
Conclusion:
Meropenem 1,000 mg every 8 h optimizes the pharmacodynamic profile in patients undergoing CVVH. Lower doses or increased dosing intervals should not be advocated for inpatients receiving this renal replacement technique. .
Insights
Meropenem 1,000 mg every 8 hours optimizes antibiotic exposure for patients on continuous veno-venous hemofiltration (CVVH). This dosing ensures bactericidal activity against challenging bacteria like Pseudomonas aeruginosa and Acinetobacter species.
Area of Science:
- Pharmacology
- Infectious Diseases
- Nephrology
Background:
- Antibiotic dosing in continuous veno-venous hemofiltration (CVVH) requires careful consideration of pharmacodynamic targets.
- Achieving adequate meropenem exposure (time above minimum inhibitory concentration) is crucial for effective treatment.
- Monte Carlo simulations were used to evaluate meropenem dosing regimens.
Purpose of the Study:
- To determine optimal meropenem dosing for patients undergoing CVVH.
- To assess target attainment of meropenem against Pseudomonas aeruginosa and Acinetobacter species.
Main Methods:
- Simulated 5,000 subjects with meropenem regimens (500 mg every 6, 8, 12 h; 1000 mg every 8, 12 h).
- Extrapolated pharmacokinetic data from CVVH literature.
- Utilized 2003 US MYSTIC study MIC data for target attainment calculations.
Main Results:
- Regimens of 1000 mg every 8 h and 500 mg every 6 h achieved 100% target attainment at the breakpoint.
- 1000 mg every 8 h demonstrated superior target attainment against resistant P. aeruginosa and Acinetobacter.
- Higher peak concentrations with 1000 mg every 8 h provided the greatest probability of bactericidal exposure.
Conclusions:
- Meropenem 1000 mg every 8 h is the optimal regimen for patients on CVVH.
- Lower doses or extended intervals are not recommended for this patient population.
- This regimen optimizes the pharmacodynamic profile for effective antimicrobial therapy.
Related Concept Videos
 01:15
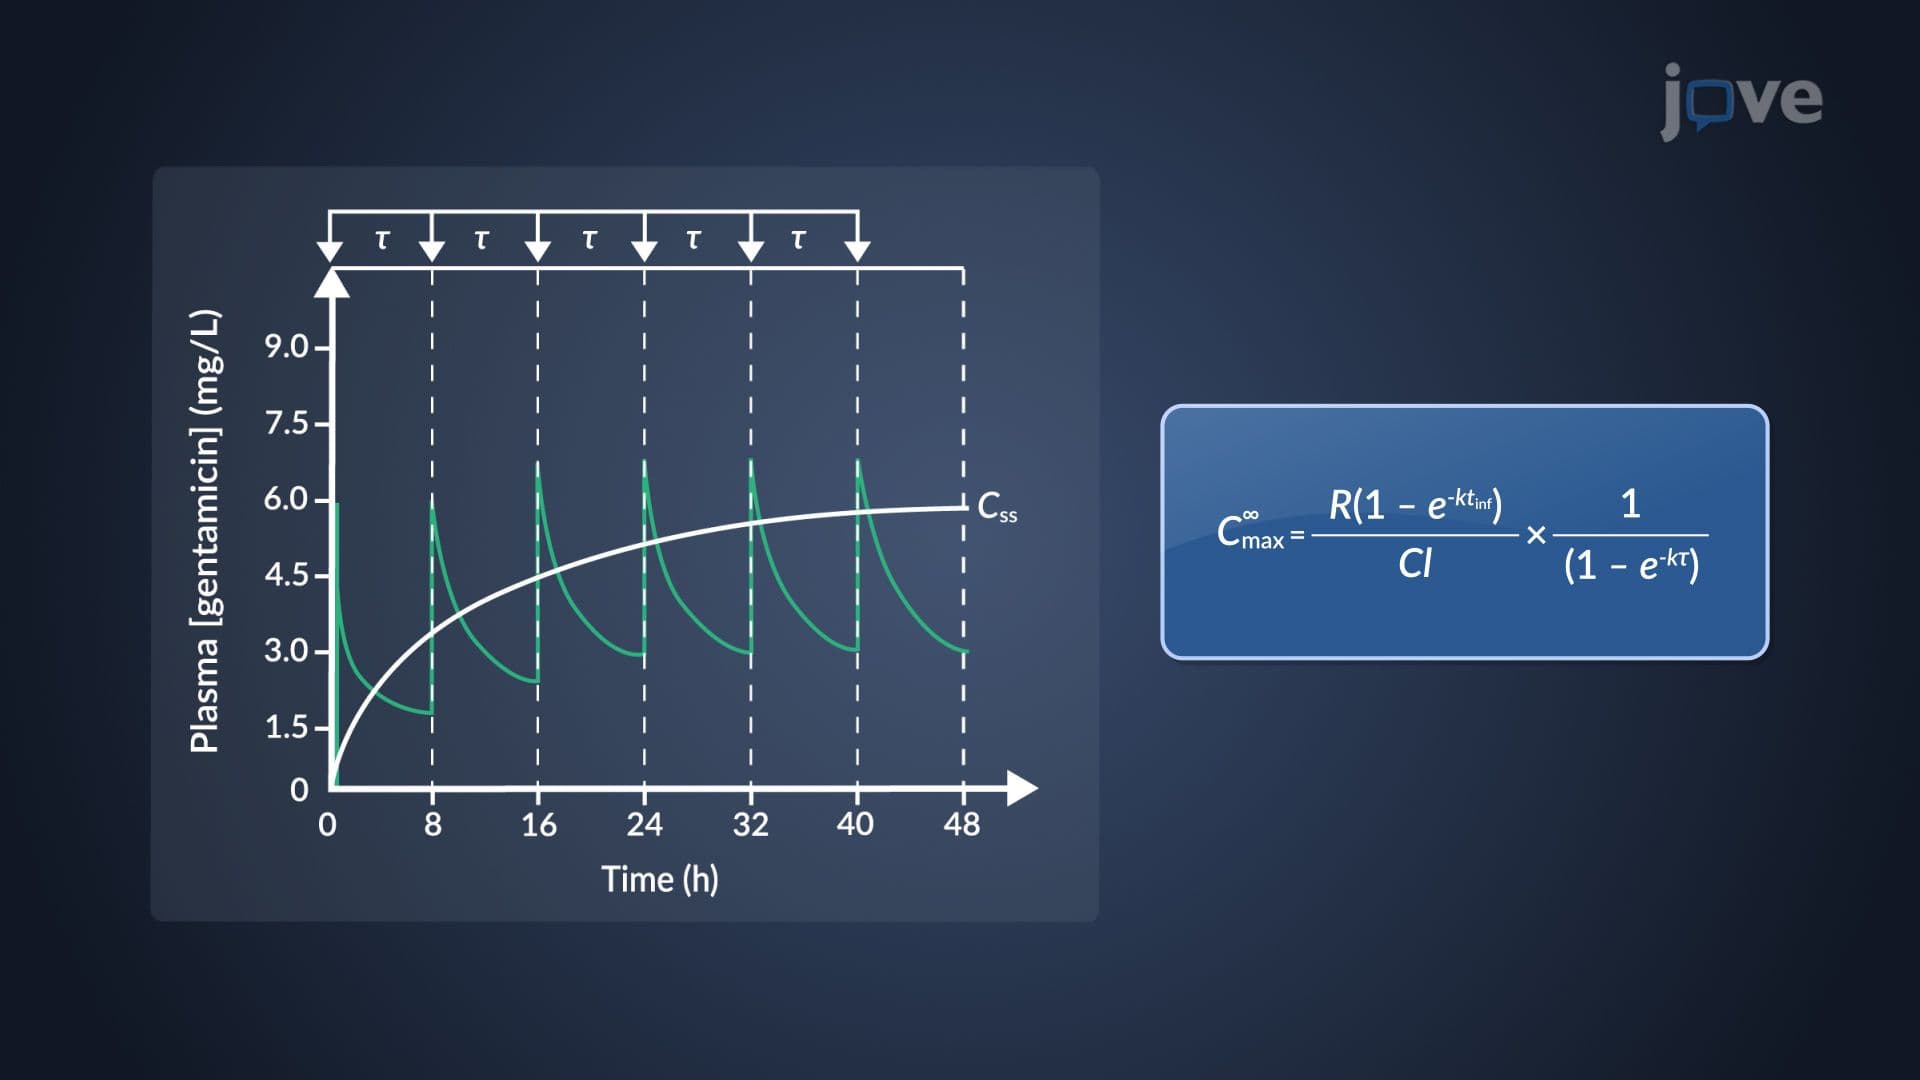
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:20
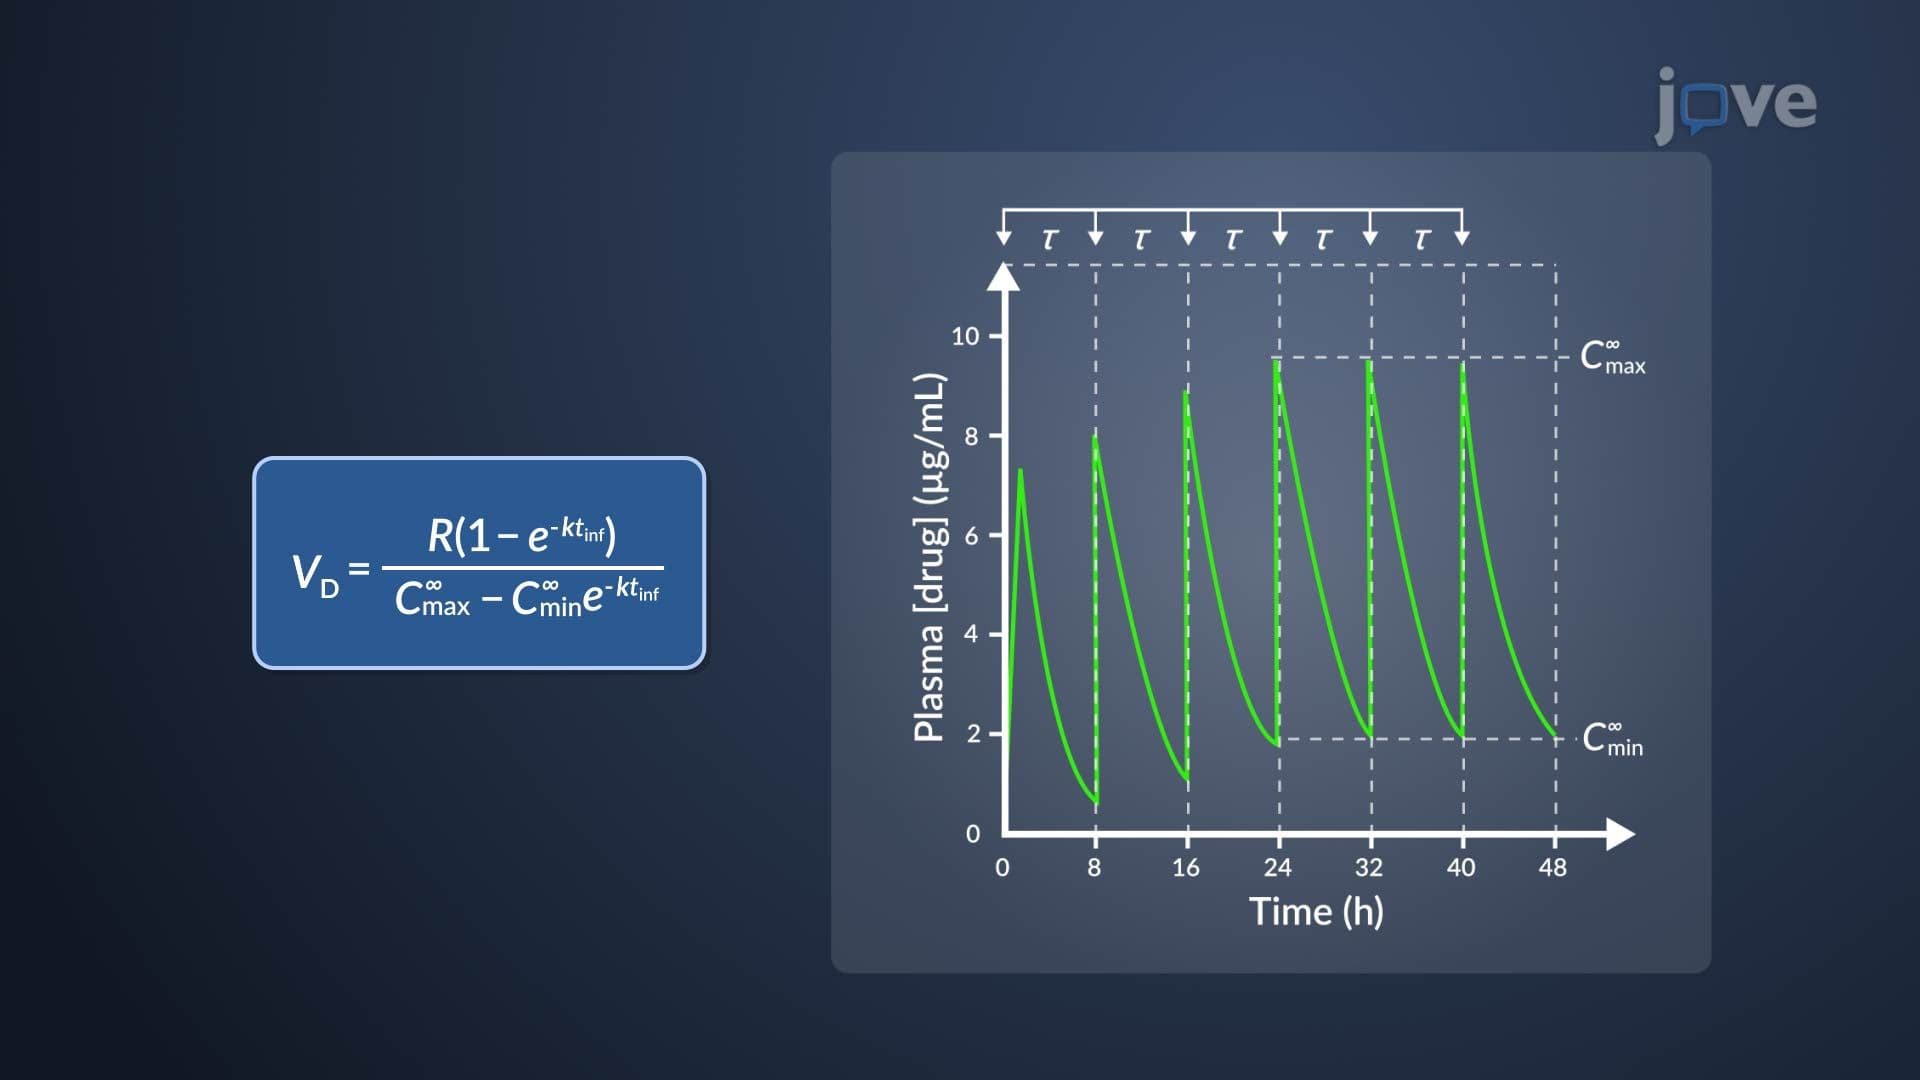
Estimation of k and VD of Aminoglycosides
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady state,...