Related Experiment Video
Updated: Aug 17, 2026


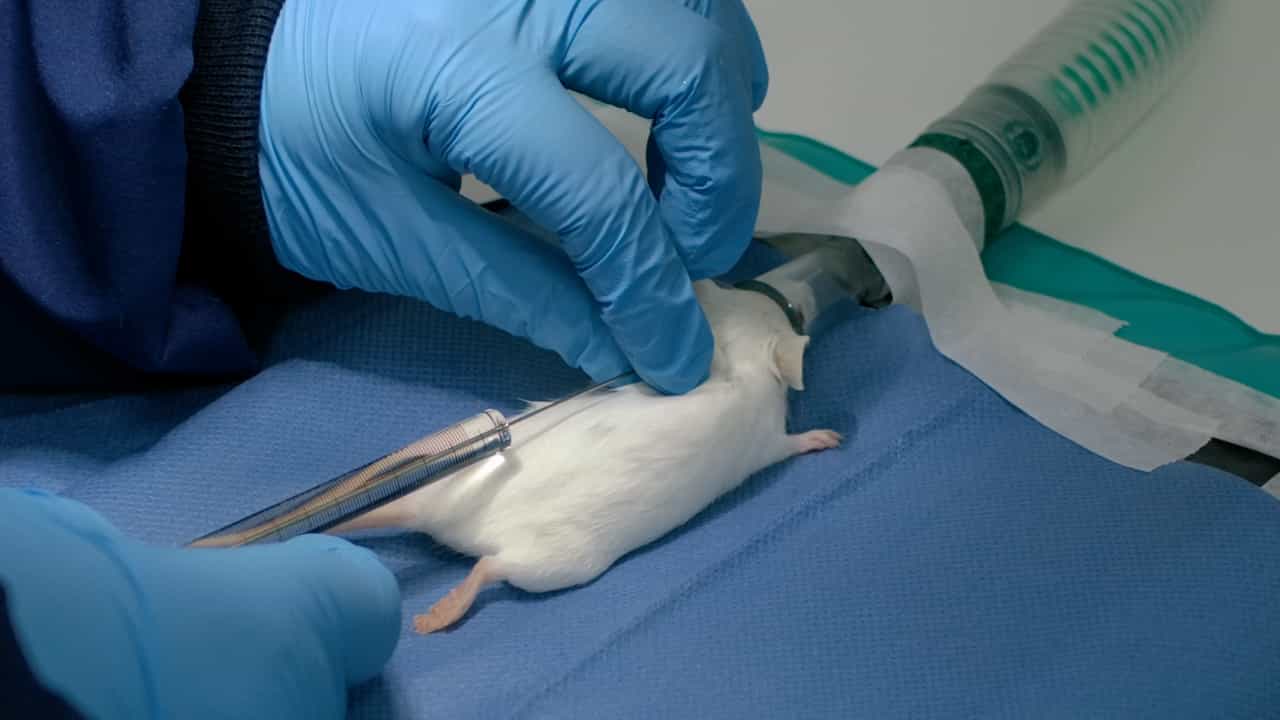
Stimulated Single Fiber Electromyography (SFEMG) for Assessing Neuromuscular Junction Transmission in Rodent Models
Published on: March 8, 2024
Recovery of neuromuscular function after a combination of mivacurium and rocuronium
Robert G Stout1, Timothy S J Shine, David G Silverman
1Department of Anesthesiology, Yale University School of Medicine, Yale-New Haven Hospital, New Haven, Connecticut, USA.

Purpose:
The present study was undertaken to evaluate onset, and early and late recovery of neuromuscular block after a combination of mivacurium (M) and rocuronium (R).
Methods:
In this controlled, randomized study, 45 consenting ASA I-II patients were assigned to one of three treatment groups: 2.ED95 R alone (2R); 2.ED95 R plus 1.ED95 M (2R1M). or 2.ED95 R plus 2.ED95 M (2R2M). Neuromuscular monitoring of the ulnar nerve consisted of surface electrode stimulation and force transduction of the adductor pollicis muscle. Stable baseline stimulation (1 Hz, square-wave, supramaximal current) was established prior to relaxant administration and continued until 95 percent twitch height depression (onset). Thereafter, train-of-four stimulation every 10 seconds was used to record recovery data until 95 percent recovery (T(95%)). Data were analyzed using grouped t-tests, ANOVA, and Newman-Keuls multiple comparison tests. Significance was defined at the p < 0.05 level.
Results:
The addition of mivacurium to rocuronium did not accelerate onset of block. The combination prolonged the clinical duration (time to 5 percent recovery, T(5%)), but did not affect subsequent recovery parameters: T(5%) in the 2R1M and 2R2M groups were 100 percent and 118 percent longer than in the 2R group, respectively (p < 0.05) the T(5-25%) (early recovery) and T(25-75%) (linear recovery) indexes were similar in all three groups.
Conclusions:
The present study did not note an acceleration of block onset when mivacurium was added to rocuronium. The findings suggest that the addition of mivacurium (1-2.ED95) to rocuronium (2.ED95) prolongs the clinical duration of the longer-acting agent, rocuronium, but has no effect on the early or linear recovery indexes of rocuronium. Thus, although clinical duration is prolonged, recovery from the combination regimens proceeds as if no mivacurium had been added to rocuronium.
Insights
Adding mivacurium to rocuronium does not speed up neuromuscular block onset. While it prolongs the duration of action, recovery times remain unaffected, suggesting no significant impact on early or linear recovery phases.
Area of Science:
- Anesthesiology
- Pharmacology
Background:
- Neuromuscular blocking agents are crucial in anesthesia for facilitating tracheal intubation and surgical procedures.
- Understanding the combined effects of different neuromuscular blockers is essential for optimizing anesthetic management and patient recovery.
Purpose of the Study:
- To evaluate the onset and recovery characteristics of neuromuscular block when mivacurium is combined with rocuronium.
- To determine if combining these agents alters the speed of neuromuscular blockade or its subsequent reversal.
Main Methods:
- A controlled, randomized study involving 45 ASA I-II patients.
- Patients received either rocuronium alone or a combination of rocuronium and mivacurium.
- Neuromuscular monitoring used ulnar nerve stimulation and force transduction, measuring onset and recovery (T(95%)).
Main Results:
- Combining mivacurium with rocuronium did not accelerate the onset of neuromuscular block.
- The clinical duration (T(5%)) was significantly prolonged in the combination groups compared to rocuronium alone.
- Early (T(5-25%)) and linear (T(25-75%)) recovery indexes were similar across all groups.
Conclusions:
- Adding mivacurium to rocuronium does not hasten block onset.
- The combination prolongs the clinical duration of rocuronium without affecting early or linear recovery.
- Recovery from combined regimens appears similar to rocuronium alone, despite a longer duration of effect.

Related Concept Videos
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:17
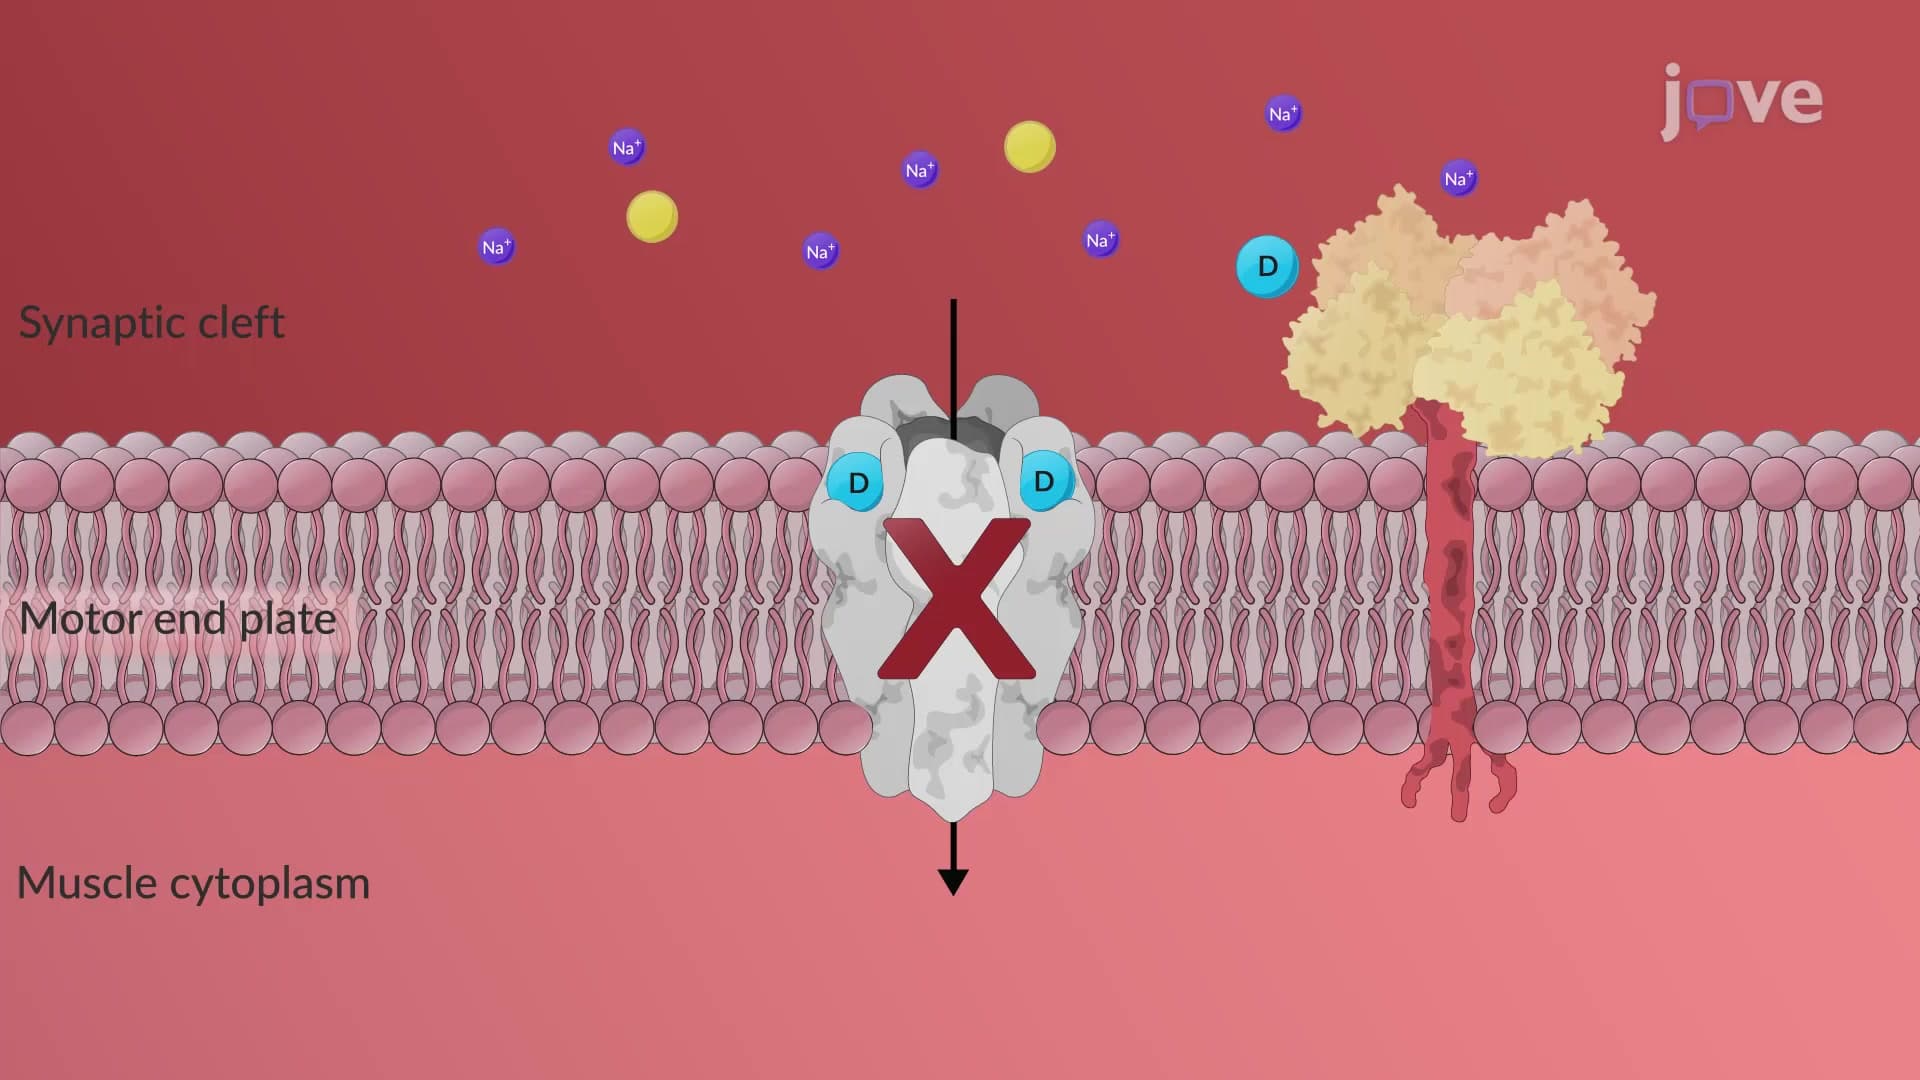
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...