Related Experiment Video
Updated: Jul 29, 2026


Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
VEGF levels in the alveolar compartment do not distinguish between ARDS and hydrostatic pulmonary oedema
L B Ware1, R J Kaner, R G Crystal
1Division of Allergy, Pulmonary and Critical Care Medicine, Dept of Medicine, Vanderbilt University School of Medicine, Nashville, TN 37232-2650, USA. lorraine.ware@vanderbilt.edu

Abstract:
Although overexpression of vascular endothelial growth factor (VEGF) 165 in the lung causes pulmonary oedema, its role in human acute lung injury (ALI) is unclear. VEGF levels are reported to be lower in bronchoalveolar lavage from ALI patients compared with normals, but these studies did not include a comparably ill control group with noninflammatory pulmonary oedema. The current authors hypothesised that VEGF levels in pulmonary oedema fluid would be lower in ALI patients compared with control patients with severe hydrostatic pulmonary oedema. VEGF was measured in pulmonary oedema fluid and plasma from 56 patients with ALI and 46 controls with severe hydrostatic pulmonary oedema. Pulmonary oedema fluid levels of VEGF did not differ between patients with hydrostatic oedema (median 799 pg x mL(-1), interquartile range (IQR) 226-2,281) and ALI (median 507, IQR 0.8-1,031). Plasma levels were also the same (median 20.5 pg x mL(-1), IQR 0-152 versus 4.8, IQR 0-99.8). There was no association between plasma or oedema fluid VEGF levels and outcomes including mortality. Vascular endothelial growth factor levels in pulmonary oedema fluid were depressed both in acute lung injury and hydrostatic pulmonary oedema. The decrease in air space concentrations of vascular endothelial growth factor in acute lung injury may not be a function of the degree of lung injury, but rather may result from alveolar flooding.
More Related Videos
 09:36
Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
 06:22
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome (ARDS)
Published on: April 7, 2021
Related Concept Videos
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:26
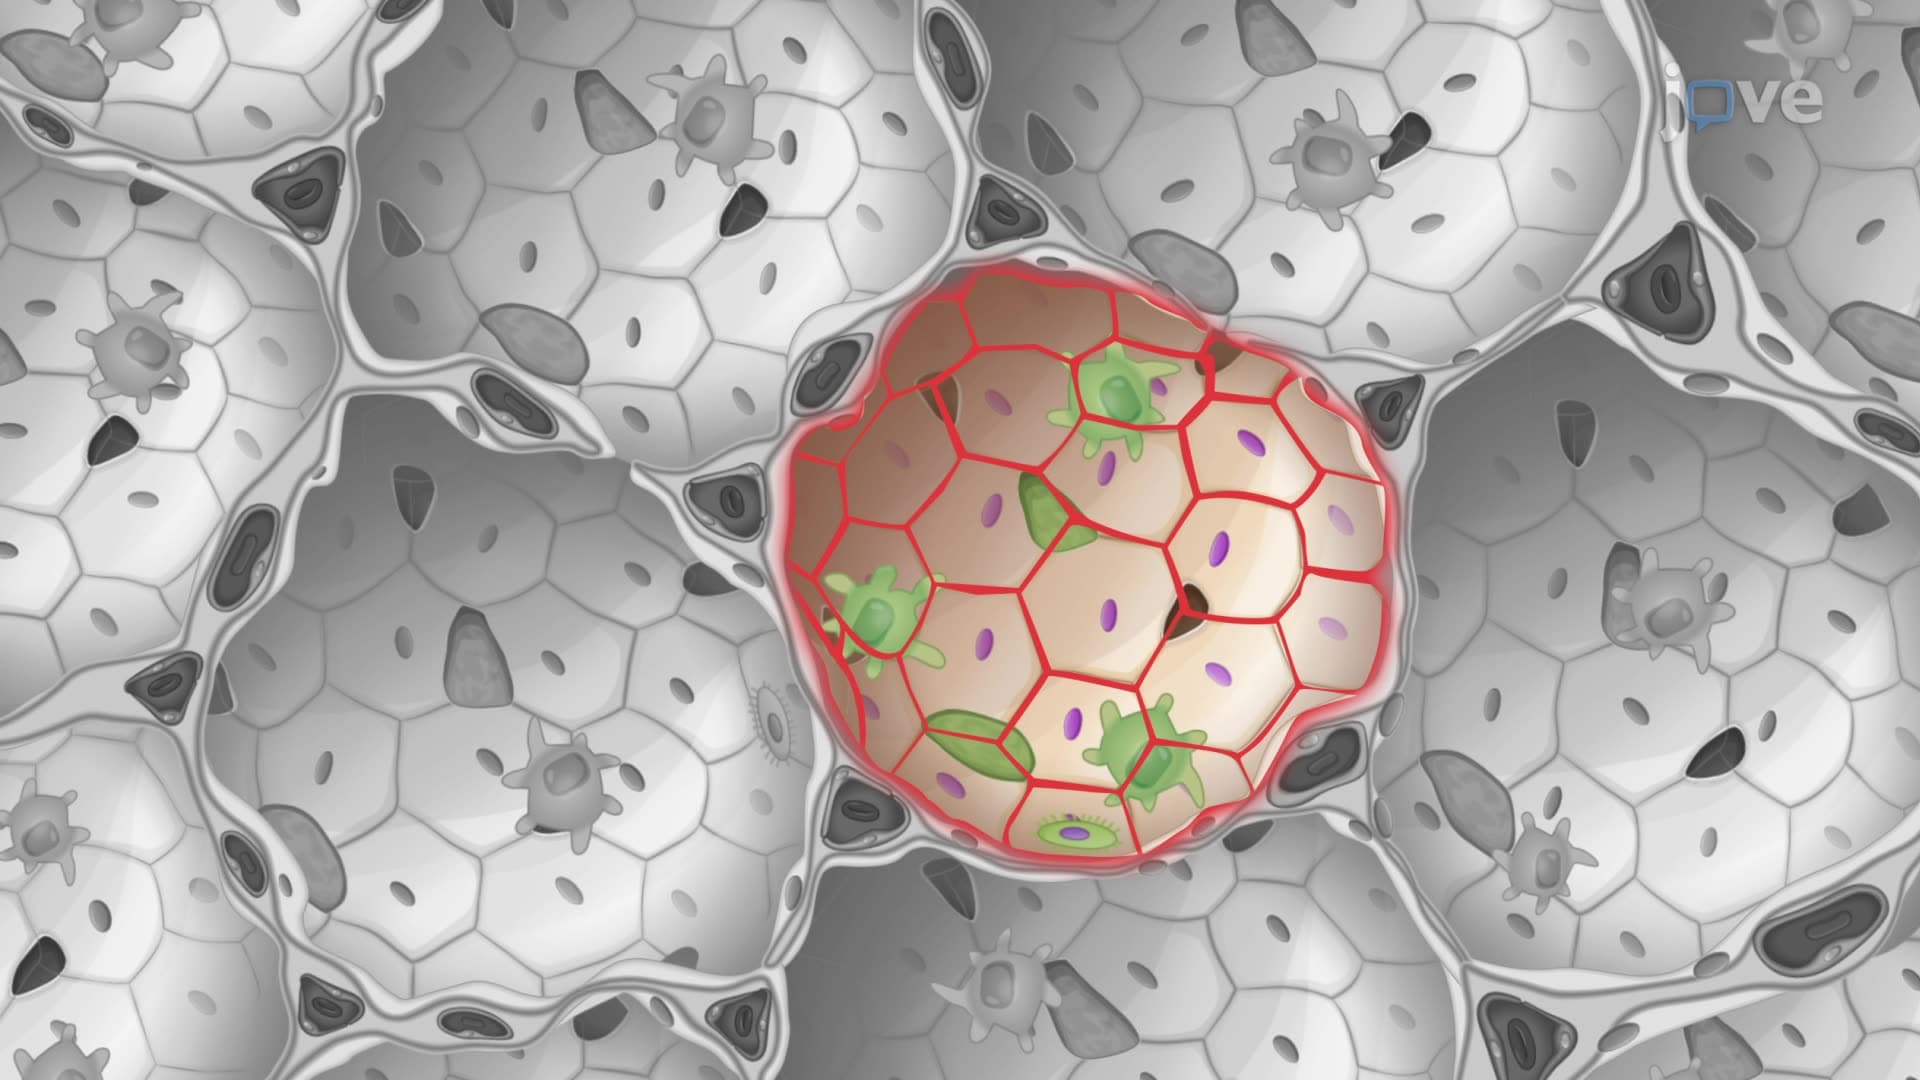
Alveoli and Alveolar Ducts
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:08
Pneumothorax II: Pathophysiology
 01:10
Atelectasis II: Pathophysiology
 01:18
Pulmonary Edema II: Pathophysiology