Related Experiment Video
Updated: Aug 17, 2026


The WATCHMAN Left Atrial Appendage Closure Device for Atrial Fibrillation
Published on: February 28, 2012
Fuzzy logic and continuous cellular automata in warfarin dosing of stroke patients
Cathy M Helgason1, Thomas H Jobe
1Department of Neurology, University of Illinois College of Medicine, 912 South Wood Street, Room 855N, Chicago, IL 60611, USA. helgason@uic.edu

"Evidence-based" recommendations for warfarin prescription in patients with history of ischemic stroke limit its use to prevention of stroke due to atrial fibrillation. Warfarin is also prescribed by the authors to prevent thrombosis in stroke patients with thrombophilia and potential cardiac or arterial source for thromboembolism. These potential conditions, in the face of thrombophilia, include, but may not be limited to, dilated cardiomyopathy, decreased left ventricular function, atrial septal aneurysm with or without patent foramen ovale (PFO), PFO with evidence of pelvic or lower extremity deep venous thrombosis or with clear thrombophilia, spontaneous echocardiographic contrast, intracardiac or intra-arterial thrombus, intra-aortic arch thrombus, high degree of stenosis of large- and medium-sized cerebrovascular arteries, and arterial dissection. Commonly diagnosed thrombophilic states in our population currently include protein S or C deficiency, antiphospholipid antibodies, and less commonly ATIII deficiency, factor V Leiden mutation, G20210A PT mutation, and plasminogen activator inhibitor-1 mutation. Thrombophilic states often occur in combination. The occurrence of combined arterial, cardiac, and thrombophilic sources of thromboembolism poignantly describes the complexity of causation of ischemic stroke in any one patient. Our practice of treating the complex interaction of thromboembolic sources is based on scientific evidence, which is not arbitrarily limited to probability-based statistics. Warfarin is well known in the clinical setting to interact with many different contextual factors of the individual patient, making its dosing and response unique to that patient. We have shown why the indications for warfarin use and its dosing cannot be directly extrapolated to the individual patient from the results of large, double-blind, randomized trials. In practice, the unique patient and his or her context must be considered by the expert physician who makes the therapeutic decision. The context includes, but is not limited to, known pathologies that contribute to thrombus formation according to the accepted pathophysiologic model of thrombosis based on Virchow's triad of altered flow, endothelium, and blood components.
"Evidence-based" recommendations for warfarin prescription in patients with history of ischemic stroke limit its use to prevention of stroke due to atrial fibrillation. Warfarin is also prescribed by the authors to prevent thrombosis in stroke patients with thrombophilia and potential cardiac or arterial source for thromboembolism. These potential conditions, in the face of thrombophilia, include, but may not be limited to, dilated cardiomyopathy, decreased left ventricular function, atrial septal aneurysm with or without patent foramen ovale (PFO), PFO with evidence of pelvic or lower extremity deep venous thrombosis or with clear thrombophilia, spontaneous echocardiographic contrast, intracardiac or intra-arterial thrombus, intra-aortic arch thrombus, high degree of stenosis of large- and medium-sized cerebrovascular arteries, and arterial dissection. Commonly diagnosed thrombophilic states in our population currently include protein S or C deficiency, antiphospholipid antibodies, and less commonly ATIII deficiency, factor V Leiden mutation, G20210A PT mutation, and plasminogen activator inhibitor-1 mutation. Thrombophilic states often occur in combination. The occurrence of combined arterial, cardiac, and thrombophilic sources of thromboembolism poignantly describes the complexity of causation of ischemic stroke in any one patient. Our practice of treating the complex interaction of thromboembolic sources is based on scientific evidence, which is not arbitrarily limited to probability-based statistics. Warfarin is well known in the clinical setting to interact with many different contextual factors of the individual patient, making its dosing and response unique to that patient. We have shown why the indications for warfarin use and its dosing cannot be directly extrapolated to the individual patient from the results of large, double-blind, randomized trials. In practice, the unique patient and his or her context must be considered by the expert physician who makes the therapeutic decision. The context includes, but is not limited to, known pathologies that contribute to thrombus formation according to the accepted pathophysiologic model of thrombosis based on Virchow's triad of altered flow, endothelium, and blood components.
Related Concept Videos
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
 01:25
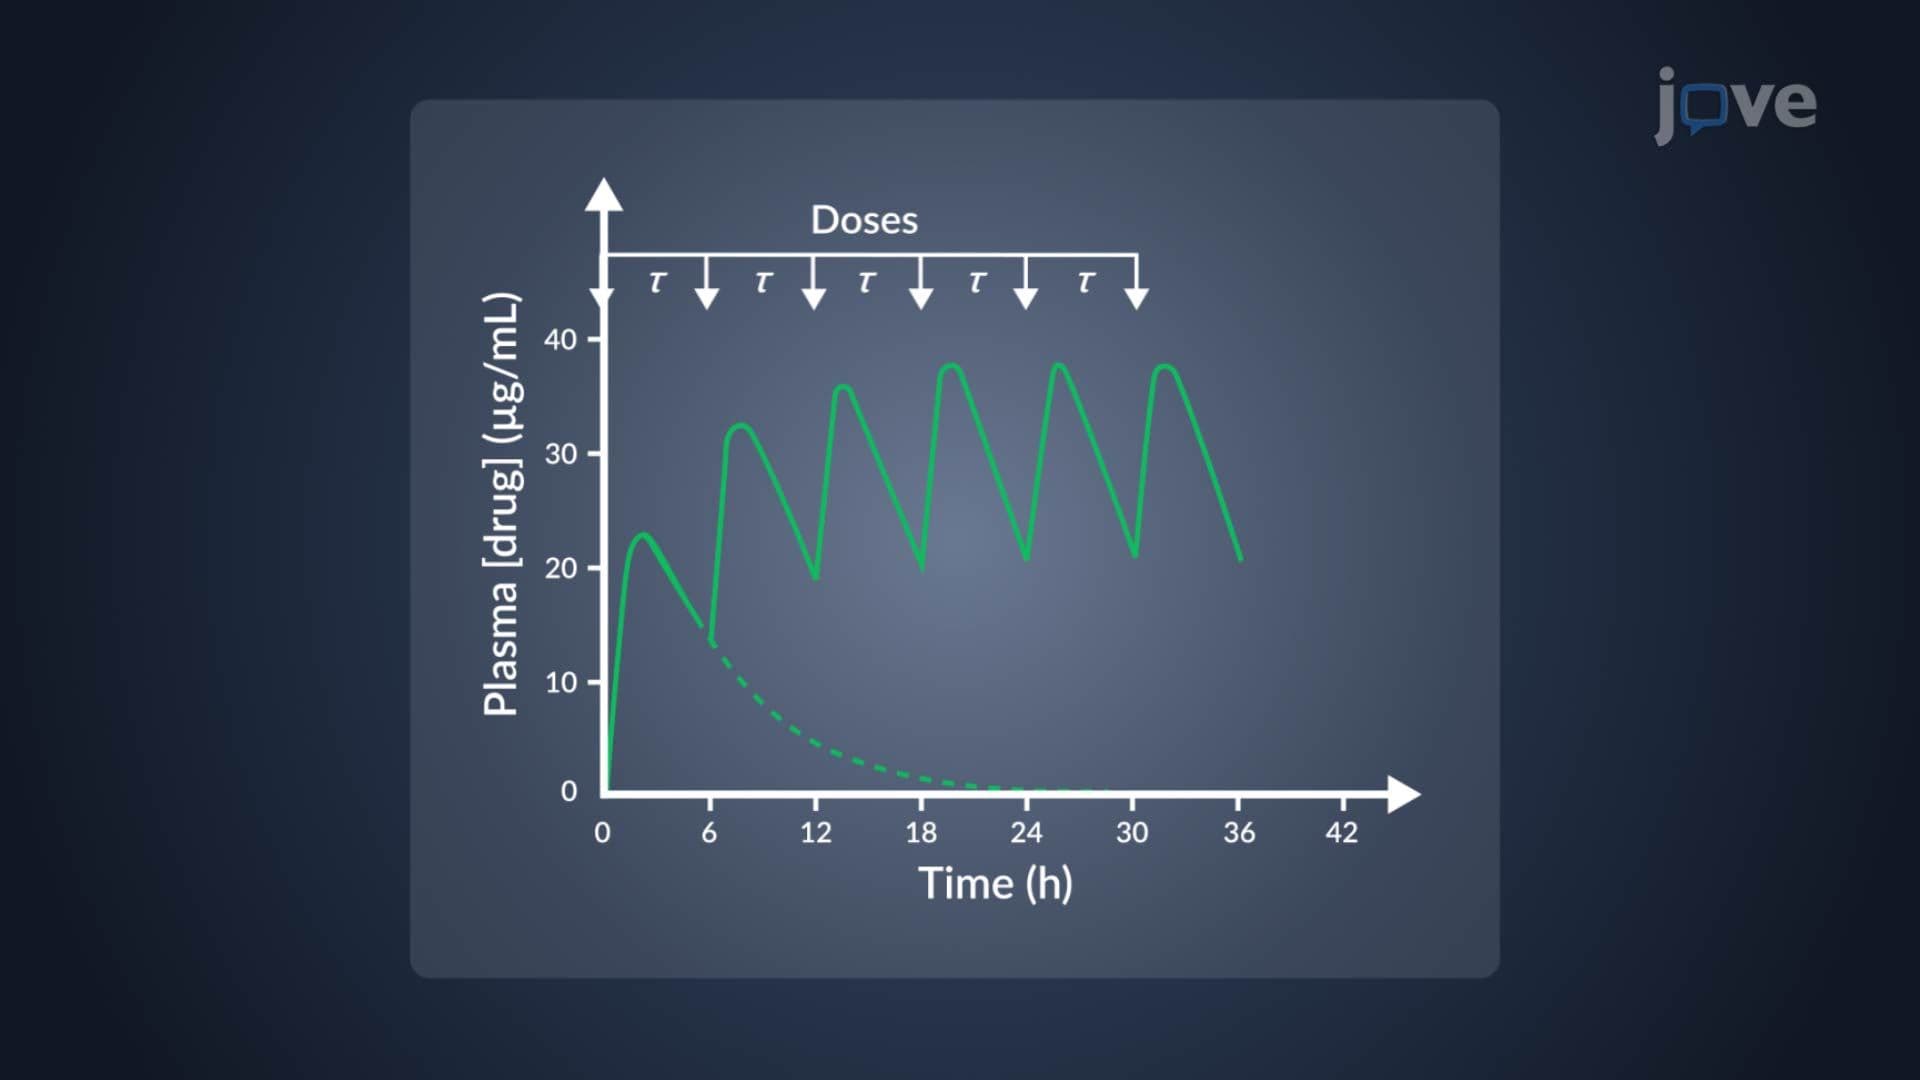
Dosage Regimen: Multiple Oral Dosage
 01:31
Classification of Systems-II
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant