Chest CT assessment following thrombolysis or surgical embolectomy for acute pulmonary embolism
Related Experiment Video
Updated: Aug 17, 2026
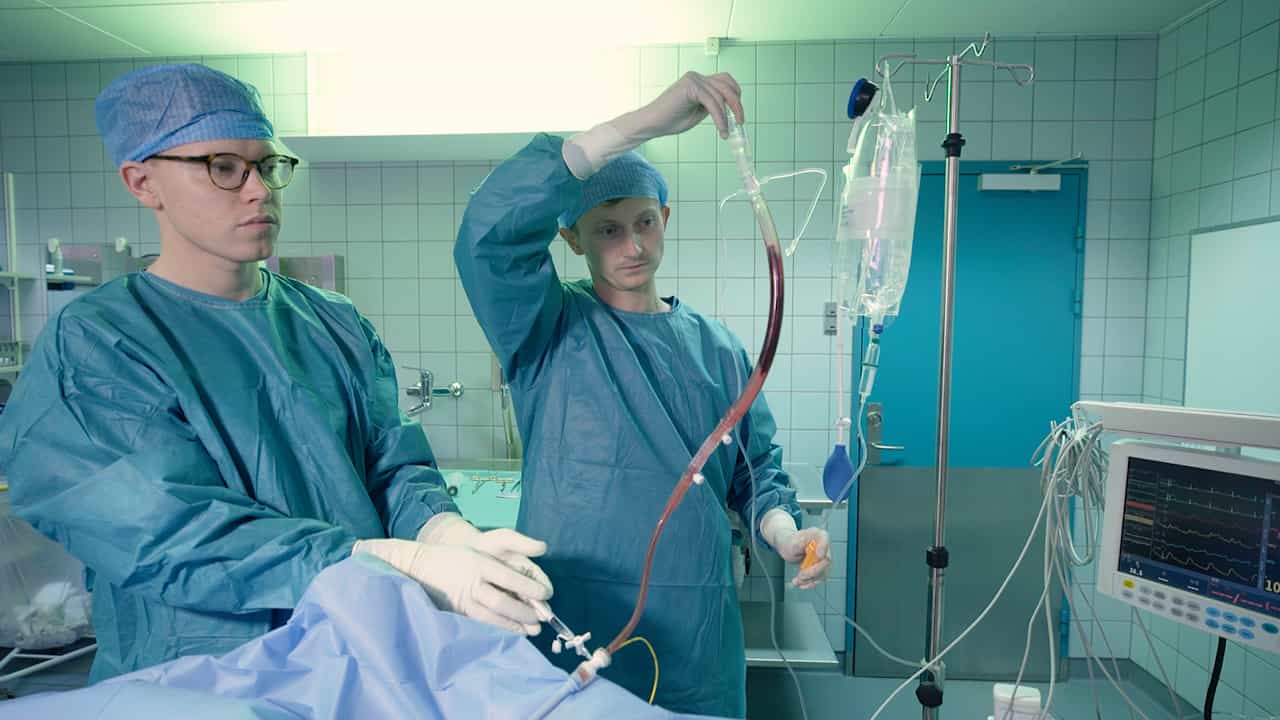
A Porcine Model of Acute Autologous Pulmonary Embolism
Published on: September 6, 2024
Florian Kipfmueller1, Rene Quiroz, Samuel Z Goldhaber
1Cardiovascular Division, Department of Medicine, Brigham and Women's Hospital, Harvard Medical School, Boston, MA 02115, USA.

Abstract:
Right ventricular (RV) enlargement, assessed by two-dimensional reconstructed 4-chamber views on contrast-enhanced multirow detector computed tomography (MDCT), is emerging as an important marker for predicting adverse clinical events in patients with acute pulmonary embolism (PE). It is unclear whether dynamic changes occur on chest computed tomography (CT) in response to thrombolysis or embolectomy to treat acute PE. We retrospectively investigated 23 consecutive patients who met the criteria of (1) a positive MDCT PE protocol; (2) RV dysfunction on echocardiography; (3) reperfusion therapy by systemic thrombolysis (n=17) or surgical embolectomy (n=6); and (4) follow-up MDCT study after completion of therapy. Two blinded observers reconstructed 4-chamber views on a Leonardo (Siemens, Munich, Germany) workstation using multiplanar reformats of axial CT data and then measured right and left ventricular dimensions (RV(D), LV(D)). RV enlargement was defined as RV(D)/LV(D) > 0.9. Mean age was 52 years, and there were 10 (43%) women. The median time to MDCT follow-up was 21 (range 2-231) days. Seventeen (74%) patients had their chest MDCT follow-up within 30 days. All 23 patients had RV enlargement (mean RV(D)/LV(D) 1.28, range 0.94 to 1.74) prior to initiation of reperfusion therapy. Although right ventricular enlargement was found in 43% of patients at follow-up, the mean RV(D)/LV(D) decreased from 1.28 +/- 0.21 cm to 0.94 +/- 0.16 cm (p < 0.001). The mean change in RV(D)/LV(D) was 0.31 +/- 0.42 in thrombolysis patients and 0.42 +/- 0.09 in embolectomy patients (p = 0.33). Reconstructed 4-chamber views on chest CT provide noninvasive imaging of right ventricular enlargement and permit dynamic assessment of the right ventricular response to thrombolysis and embolectomy in patients with acute PE.
Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:29
Pulmonary Embolism I: Introduction
 01:19
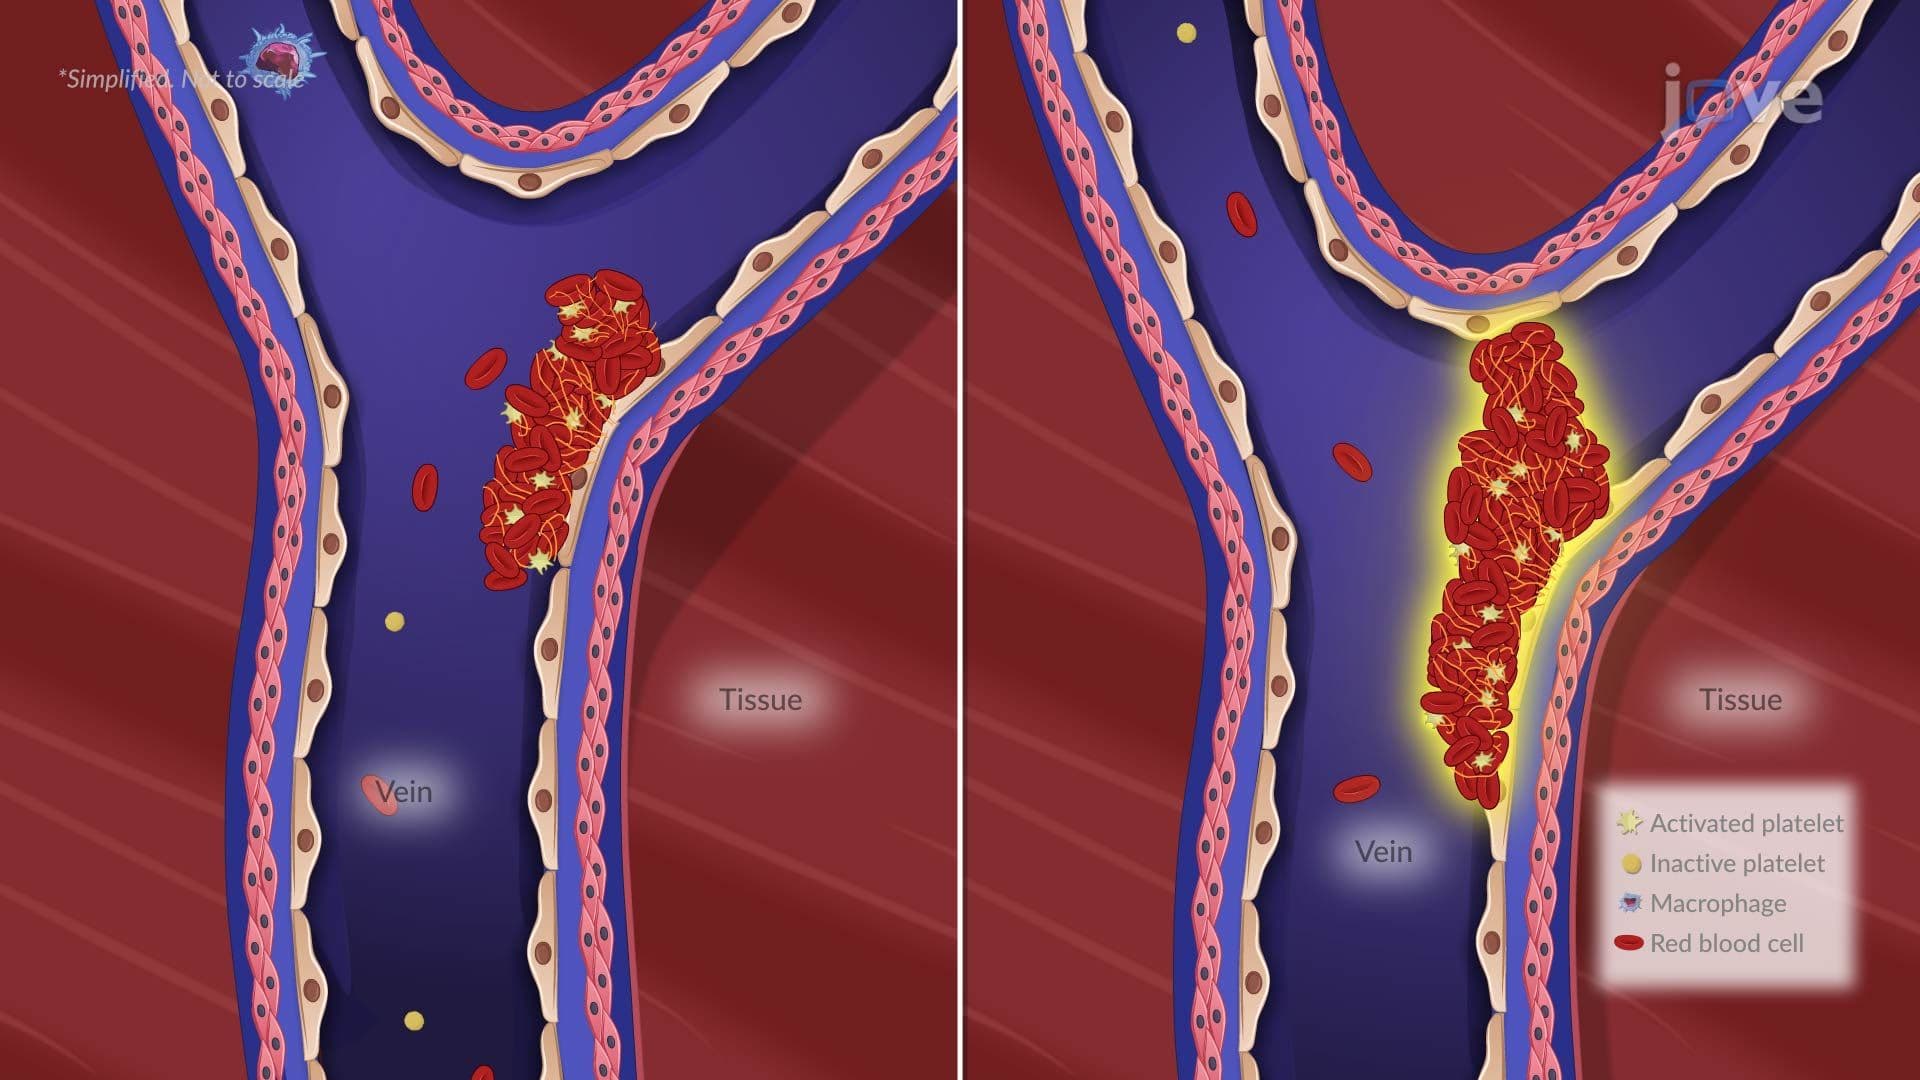
Pulmonary Embolism I: Introduction
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Pneumothorax-II
Clinical Manifestations: