Related Experiment Videos
Cholelithiasis and cholecystitis
Bruce D Schirmer1, Kathryne L Winters, Richard F Edlich
1Department of Surgery, University of Virginia Health System Charlottesville VA 22908, USA. bs@virginia.edu

Abstract:
Gallstone disease remains one of the most common medical problems leading to surgical intervention. Every year, approximately 500,000 cholecystectomies are performed in the US. Cholelithiasis affects approximately 10% of the adult population in the United States. It has been well demonstrated that the presence of gallstones increases with age. An estimated 20% of adults over 40 years of age and 30% of those over age 70 have biliary calculi. During the reproductive years, the female-to-male ratio is about 4:1, with the sex discrepancy narrowing in the older population to near equality. The risk factors predisposing to gallstone formation include obesity, diabetes mellitus, estrogen and pregnancy, hemolytic diseases, and cirrhosis. A study of the natural history of cholelithiasis demonstrates that approximately 35% of patients initially diagnosed with having, but not treated for, gallstones later developed complications or recurrent symptoms leading to cholecystectomy. During the last two decades, the general principles of gallstone management have not notably changed. However, methods of treatment have been dramatically altered. Today, laparoscopic cholecystectomy, laparoscopic common bile duct exploration, and endoscopic retrograde management of common bile duct (CBD) stones play important roles in the treatment of gallstones. These technological advances in the management of biliary tract disease are not infrequently accomplished by a multidisciplinary team of physicians, including surgeons trained in laparoscopic techniques, interventional gastroenterologists, and interventional radiologists. With the evolution of laparoscopic cholecystectomy, there has been a global reeducation and retraining program of surgeons. However, the treatment of choice for gallstones remains cholecystectomy. In recognition of the revolutionary advances in the treatment of cholelithiasis, it is the purpose of this collective review to describe recent information on the following topics: types of gallstones, asymptomatic gallstones, symptomatic gallstones, chronic cholecystitis, acute cholecystitis, and other complications of gallstones. Gross and compositional analysis of gallstones allows them to be classified as cholesterol, mixed, and pigment gallstones. When asymptomatic gallstones are detected during the evaluation of a patient, a prophylactic cholecystectomy is normally not indicated because of several factors. Only about 30% of patients with asymptomatic cholelithiasis will warrant surgery during their lifetime, suggesting that cholelithiasis can be a relatively benign condition in some people. However, there are certain factors that predict a more serious course in patients with asymptomatic gallstones and warrant a prophylactic cholecystectomy when they are present. These factors include patients with large (>2.5 cm) gallstones, patients with congenital hemolytic anemia or nonfunctioning gallbladders, or during bariatric surgery or colectomy. Epigastric and right upper quadrant pain occurring 30-60 minutes after meals is frequently associated with gallstone disease. The diagnosis of chronic cholecystitis is made by the presence of biliary colic with evidence of gallstones on an imaging study. Ultrasonography is the diagnostic test of choice, being 90-95% sensitive. The surgical literature suggests that 3-10% of patients undergoing cholecystectomy will have CBD stones. Intraoperative laparoscopic ultrasonography has recently replaced cholangiography as the method of choice for detecting CBD stones. Ultrasonography and radionuclide cholescintigraphy (HIDA scan) are useful in establishing a diagnosis of acute cholecystitis. Laparoscopic cholecystectomy should also be used in the treatment of acute cholecystitis. Laparoscopic cholecystectomy is more likely to be successful when performed within 3 days of the onset of symptoms. It is important to remember that gallstones can lead to a variety of other complications including choledocholithiasis, gallstone ileus, and acute gallstone pancreatitis.
Related Concept Videos
 01:20
Cholecystitis
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not related to...
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:24
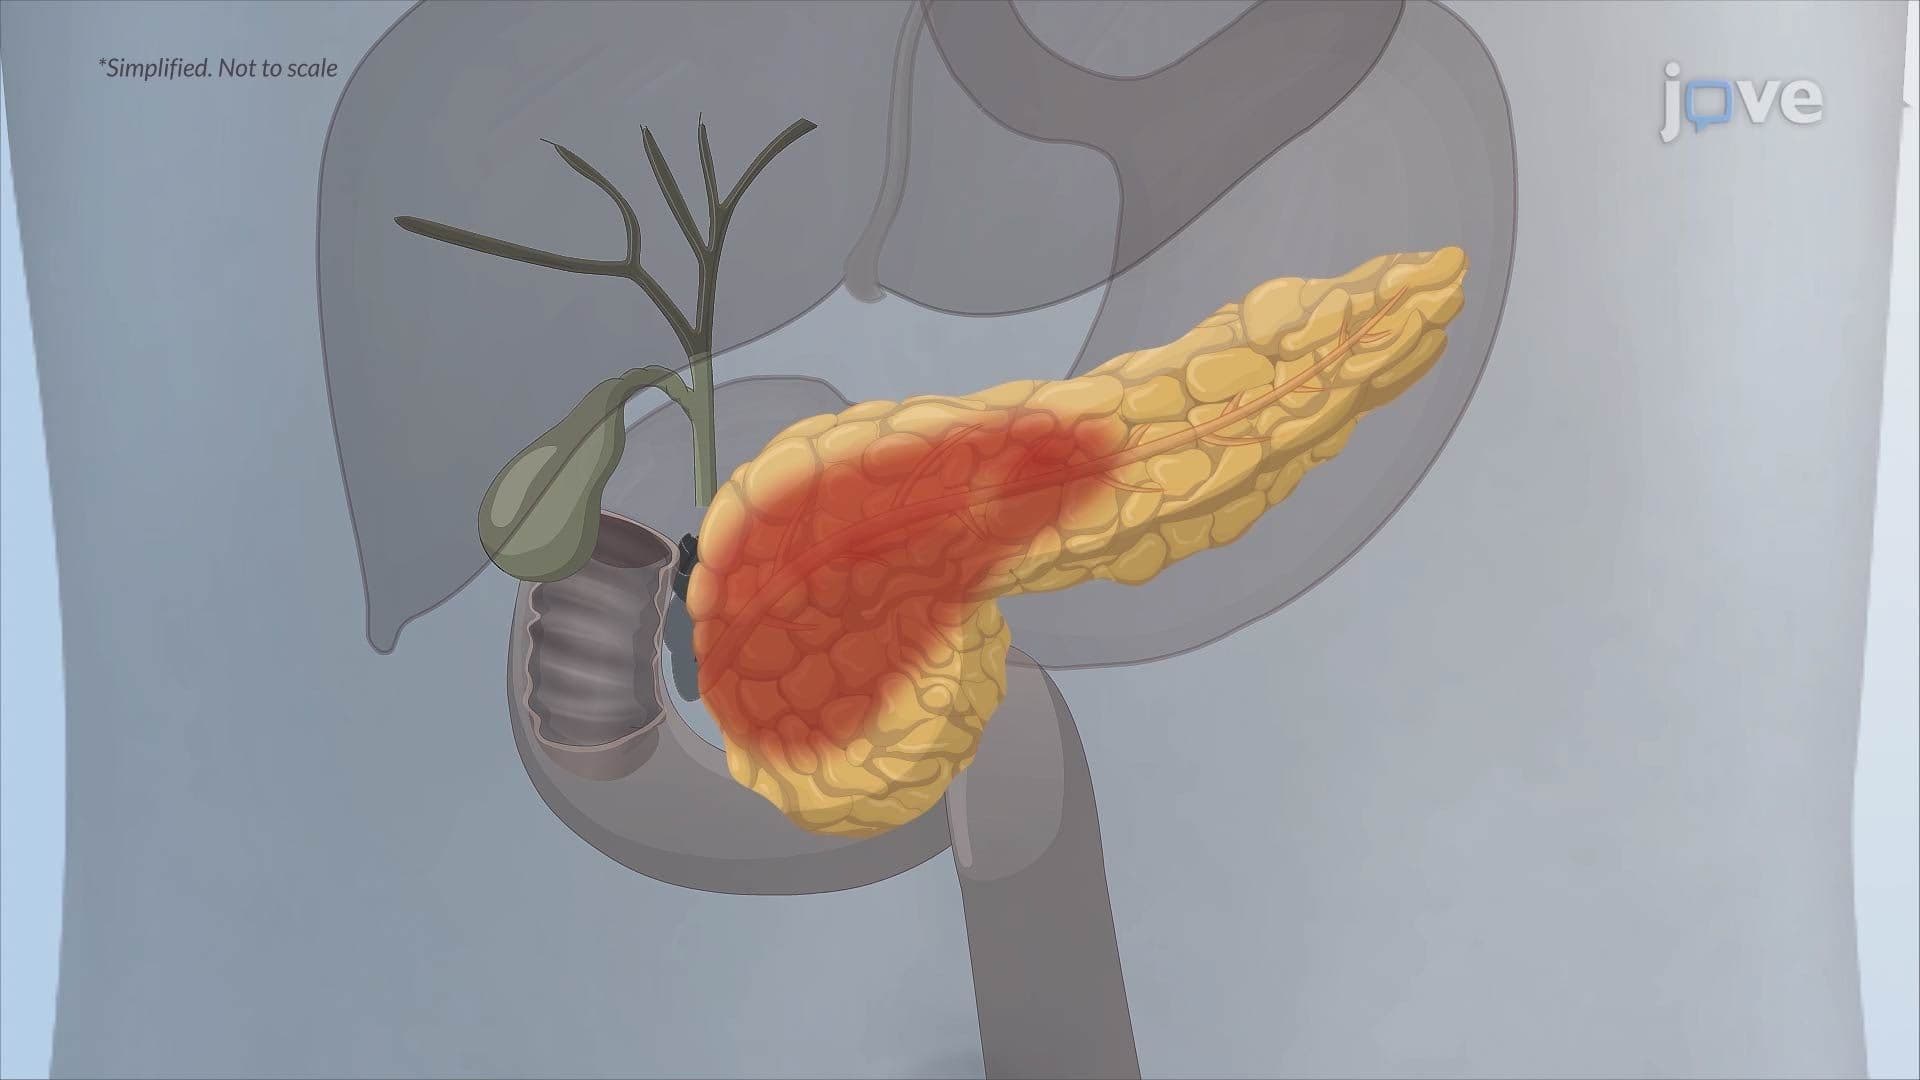
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Chronic Pancreatitis I: Introduction