Related Experiment Video
Updated: Aug 16, 2026
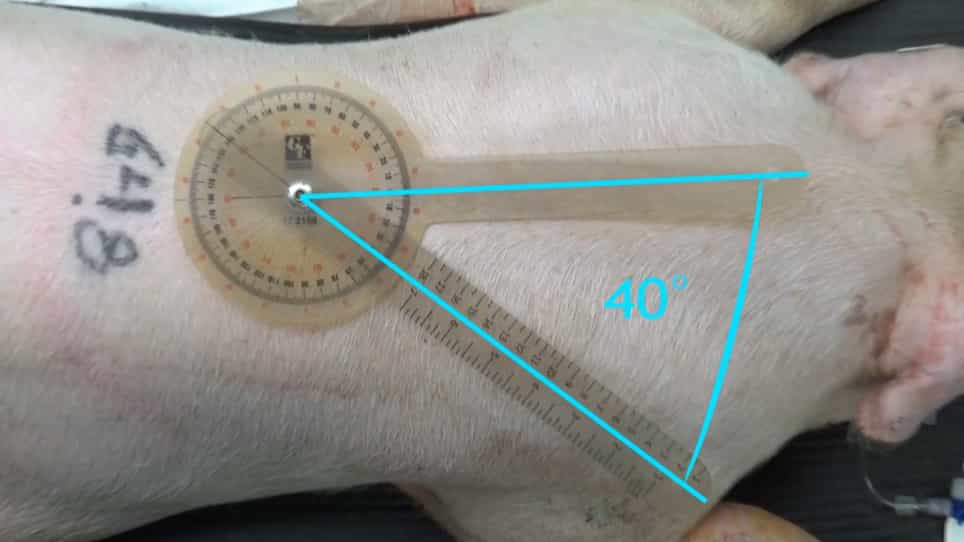
Brachial Artery Catheterization in Swine
Published on: March 30, 2019
Catheterization of the radial or brachial artery in neonates and infants
Ehrenfried Schindler1, Bernd Kowald, Heino Suess
1Department of Anaesthesiology and Intensive Care Medicine, Asklepios Klinik Sankt Augustin, German Paediatric Heart Center, Sankt Augustin, Germany. es@anesthesiology.de

Background:
In neonates and small children, percutaneous insertion of arterial catheters may be very difficult because of the small diameter of the arteries. Multiple attempts at cannulation are common and may be a predictor of serious adverse events following arterial cannulation. As an end artery, the brachial artery is usually not recommended for cannulation. However, limited data exist about brachial artery catheterization in neonates and young children. In this retrospective study, we report our experience with arterial indwelling catheters placed in neonates and small children prior to surgery for congenital heart defects.
Methods:
We reviewed 1473 patient medical files containing information about 1574 arterial lines for perioperative and intensive care monitoring. Patient data (age and weight), cannulation characteristics (site, type, percutaneous or cut down insertion), duration of catheterization and complications were documented using the anesthesia and/or intensive care unit files. Patients were divided into three groups according to body weight. Group I: patients with a bodyweight up to 5 kg (n = 561), group II: bodyweight 5-10 kg (n = 615), and group III: bodyweight 10-20 kg (n = 297).
Results:
The vast majority of our patients had radial or brachial artery catheterization. In group 1, we placed 200 brachial artery lines. Radial artery insertion was more successful with increasing body weight. Two 'cut downs' were necessary to place the arterial cannula (0.3%). The mean duration of the arterial cannula in place was 5.8 + 4.3 days in group I, which was significantly longer than in group III (2.9 + 2.2 days). Multiple attempts at catheter insertion were required for 200 patients in group I (P < 0.05 compared with groups II and III). The number of guide wires used was similar in all study groups. Generally, we preferred 24 and 22 G catheters for cannulation. Serious complications such as permanent ischemic damage were not observed. Temporary occlusion of an artery occurred in five of 1473 patients. The rate of local infection was 0.5% in group I, 0.7% in group II and 2.3% in group III. Local hematoma were observed more frequently, but with no relevant consequences. Most of our patients were cannulated on the right side. In group I, 112 brachial artery catheters were placed. The greater the weight, the more radial catheters were used compared with a brachial approach. The mean functional time of the catheters (5.8 +/- 4.3 days in group I) was significant shorter compared with patients from group III (2.9 +/- 2.2 days). In 33.3% (n = 200) multiple punctures were needed to place a catheter in group I (P < 0.05 compared with the other groups) whereas the use of a guide wire was evenly distributed throughout the study groups. Small catheters (24 and 22 G) were preferred for most patients. In total only eight 20 G sized catheters were used in the children of group III.
Conclusions:
Even considering the nature of a retrospective study design, we conclude that the brachial artery could be considered for cannulation in neonates and small children.
Related Concept Videos
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps:
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:12
Arteries of the Upper Limbs
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:21
Cardiac Catheterization II: Right Heart Catheterization