Related Experiment Video
Updated: Aug 16, 2026


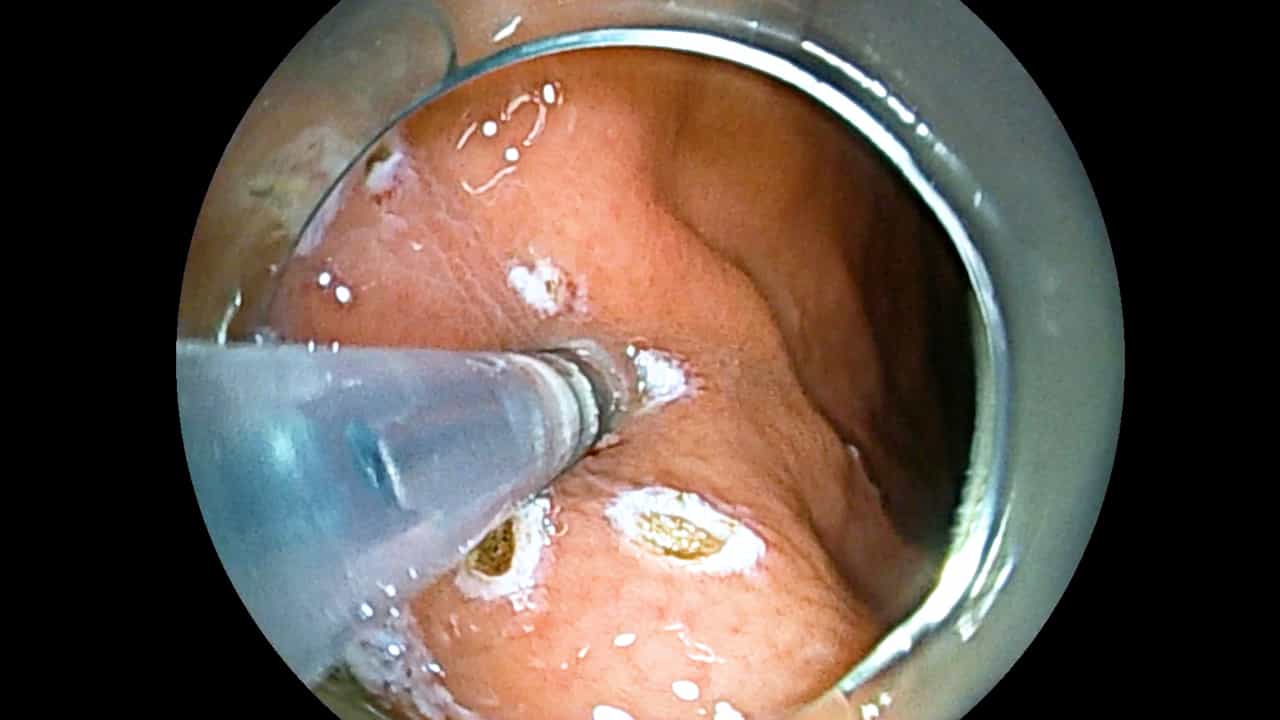
ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
The effectiveness of sucralfate against stricture formation in experimental corrosive esophageal burns
Z Günyüz Temir1, Aytaç Karkiner, Irfan Karaca
1Department of Pediatric Surgery, Dr. Behçet Uz Children's Hospital, 35210 IIzmir, Turkey.

Purpose:
In this study, the effectiveness of sucralfate against stricture formation in experimental corrosive esophageal burn is reported.
Methods:
Sixty-four Swiss albino adult male rats were divided into three groups, group A (control; n, 7), group B (esophageal burn induced but not treated; n, 25), and group C (esophageal burn induced and treated with sucralfate, n, 32). Groups B and C were further subdivided into subgroups for evaluation on days 2, 7, and 28. A standard esophageal burn was performed by the method of Gehanno, using 50% NaOH. Oral sucralfate treatment was given to group C at a dosage of 50 mg/100 g twice daily. The rats were then killed after 2, 7, or 28 days. Levels of tissue hydroxyproline were measured in excised abdominal esophageal segments, and a histopathological evaluation was performed with hematoxylin-eosin and Masson's trichrome staining.
Results:
The tissue hydroxyproline levels were significantly lower in group C than in group B (P = 0.017). There was a significant difference in the stenosis index between groups B and C (P = 0.016). When compared with group B, the collagen deposition in the submucosa and tunica muscularis was significantly lower in group C (P = 0.02).
Conclusion:
Sucralfate has an inhibitory effect on stricture formation in experimental corrosive burns and can be used in the treatment of corrosive esophageal burns to enhance mucosal healing and suppress stricture formation.
More Related Videos

Related Concept Videos
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...