Related Experiment Video
Updated: Aug 14, 2026
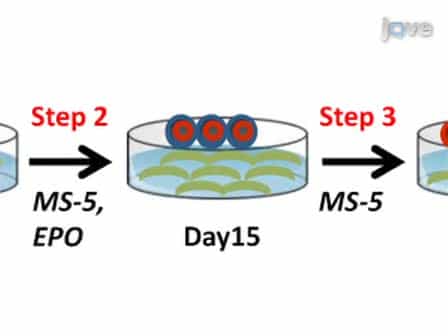
Lentiviral-mediated Knockdown During Ex Vivo Erythropoiesis of Human Hematopoietic Stem Cells
Published on: July 16, 2011
Recombinant human erythropoietin for chronic renal failure anaemia in pre-dialysis patients
1Cochrane Incontinence Review Group, University of Aberdeen, Health Services Research Unit, Polwarth Building, Foresterhill, Aberdeen, UK, AB25 2ZD. j.cody@abdn.ac.uk

Background:
Treatment with recombinant human erythropoietin (rHu EPO) in dialysis patients has been shown to be highly effective in terms of correcting anaemia and improving quality of life. There is debate concerning the benefits of rHu EPO use in pre-dialysis patients which may accelerate the deterioration of renal function. However the opposing view is that if rHu EPO is as effective in pre-dialysis patient's, improving the patients sense of well-being may result in the onset of dialysis being delayed.
Objectives:
To assess the effects of rHu EPO use in pre-dialysis patients with renal anaemia.
Search Strategy:
The initial search included 13 electronic databases (1980 to May 2001) an internet search (August 1997), handsearching of Kidney International (1983 to May 1997), contact with known investigators and biomedical companies, and reference list of relevant articles. For this update we searched the Cochrane Renal Group's specialised register (June 2004) and The Cochrane Library (Issue 3, 2004).
Selection Criteria:
Randomised controlled trials (RCTs) or quasi-RCTs comparing the use of rHu EPO with no treatment or placebo in pre-dialysis patients.
Data Collection And Analysis:
Only published data were used. Quality assessment was performed by two assessors independently. Data were abstracted by a single author onto a standard form, a sample of which was checked by another author. Results were expressed as relative risk (RR) or weighted mean difference (WMD) with 95% confidence intervals (CI).
Main Results:
Fifteen trials (461 participants) were included. There was a marked improvement in haemoglobin (WMD 1.82 g/dL, 95% CI 1.35 to 2.28) and haematocrit (WMD 9.85%, 95% CI 8.35 to 11.34) with treatment and a decrease in the number of patients requiring blood transfusions (RR 0.32, 95% CI 0.12 to 0.83). The data from studies reporting quality of life or exercise capacity demonstrated an improvement in the treatment group. Most of the measures of progression of renal disease showed no statistically significant difference. No significant increase in adverse events was identified.
Authors' Conclusions:
Treatment with rHu EPO in pre-dialysis patients corrects anaemia, avoids the requirement for blood transfusions and also improves quality of life and exercise capacity. We were unable to assess the effects of rHu EPO on progression of renal disease, delay in the onset of dialysis or adverse events. Based on the current evidence, decisions on the putative benefits in terms of quality of life are worth the extra costs of pre-dialysis rHu EPO need careful evaluation.
More Related Videos


Related Concept Videos
 01:14
Erythropoiesis
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy