Mycophenolate mofetil suspension in pediatric renal transplantation: three-year data from the tricontinental trial
Related Experiment Video
Updated: Aug 16, 2026

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Britta Höcker1, Lutz T Weber, Timothy Bunchman
1Division of Pediatric Nephrology, University Children's Hospital Heidelberg, Heidelberg, Germany.

Abstract:
Mycophenolate mofetil (MMF) is widely used to prevent acute rejection in adult solid organ transplant recipients, but data in children and adolescents are scarce. This prospective, multicenter, open-labeled, single-arm study investigated the efficacy and safety of an MMF-based immunosuppressive regimen in 100 pediatric renal transplant recipients over a 3-yr period of time. Three age groups were formed (<6 yr, n = 33; 6 to <12 yr, n = 34; 12-18 yr, n = 33). Basic immunosuppression consisted of MMF (600 mg/m(2) b.i.d), cyclosporin A microemulsion and corticosteroids. Seventy-three percent of patients were given anti-lymphocyte antibody induction therapy, of whom 74% received anti-thymocyte globulin. Patient and graft survival 3 yr after transplantation amounted to 98 and 95%, respectively. Twenty-five percent of all patients suffered a biopsy-proven acute rejection episode in the first 6 month post-transplant. Children undergoing induction therapy exhibited a numerically lower rejection rate (21 vs. 37%, p = 0.11). Three years after transplantation, the acute rejection rate added up to 30% (26% with induction therapy vs. 41% without induction therapy, p = 0.21). The number of patients with acute rejection was lowest in the youngest age group (18%), in comparison with 39% in the 6 to <12 yr and 33% in the 12-18 yr age group, respectively. For the entire patient population, the rate of patients who withdrew prematurely because of adverse events was low (12%). The present study shows that MMF therapy in pediatric renal transplant recipients leads to an excellent patient and graft survival 3 yr post-transplant with an acceptable safety profile.
Insights
Mycophenolate mofetil (MMF) demonstrated excellent patient and graft survival in pediatric renal transplant recipients. This immunosuppressive therapy showed an acceptable safety profile over three years in children and adolescents.
Area of Science:
- Nephrology
- Immunology
- Pediatric Transplantation
Background:
- Limited data exist on mycophenolate mofetil (MMF) efficacy and safety in pediatric renal transplant recipients.
- MMF is a standard immunosuppressant for adult solid organ transplant recipients.
Purpose of the Study:
- To investigate the efficacy and safety of an MMF-based immunosuppressive regimen in pediatric renal transplant recipients.
- To evaluate patient and graft survival rates and acute rejection episodes over a 3-year period.
Main Methods:
- Prospective, multicenter, open-label, single-arm study involving 100 pediatric renal transplant recipients.
- Patients were divided into three age groups: <6 yr, 6 to <12 yr, and 12-18 yr.
- Standard immunosuppression included MMF, cyclosporine A, and corticosteroids, with optional anti-lymphocyte antibody induction therapy.
Main Results:
- Excellent 3-year patient survival (98%) and graft survival (95%) were observed.
- The overall acute rejection rate at 3 years was 30%, with lower rates in patients receiving induction therapy (26%) and the youngest age group (18%).
- Adverse events leading to premature withdrawal occurred in a low percentage of patients (12%).
Conclusions:
- MMF-based immunosuppression achieves excellent patient and graft survival in pediatric renal transplant recipients.
- The regimen is associated with an acceptable safety profile in this pediatric population.
- Further research may explore optimal MMF dosing and induction strategies across different pediatric age groups.
Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:16
Kidney Transplant III: Nursing Management
 01:28
Kidney Transplant I: Introduction
 01:15
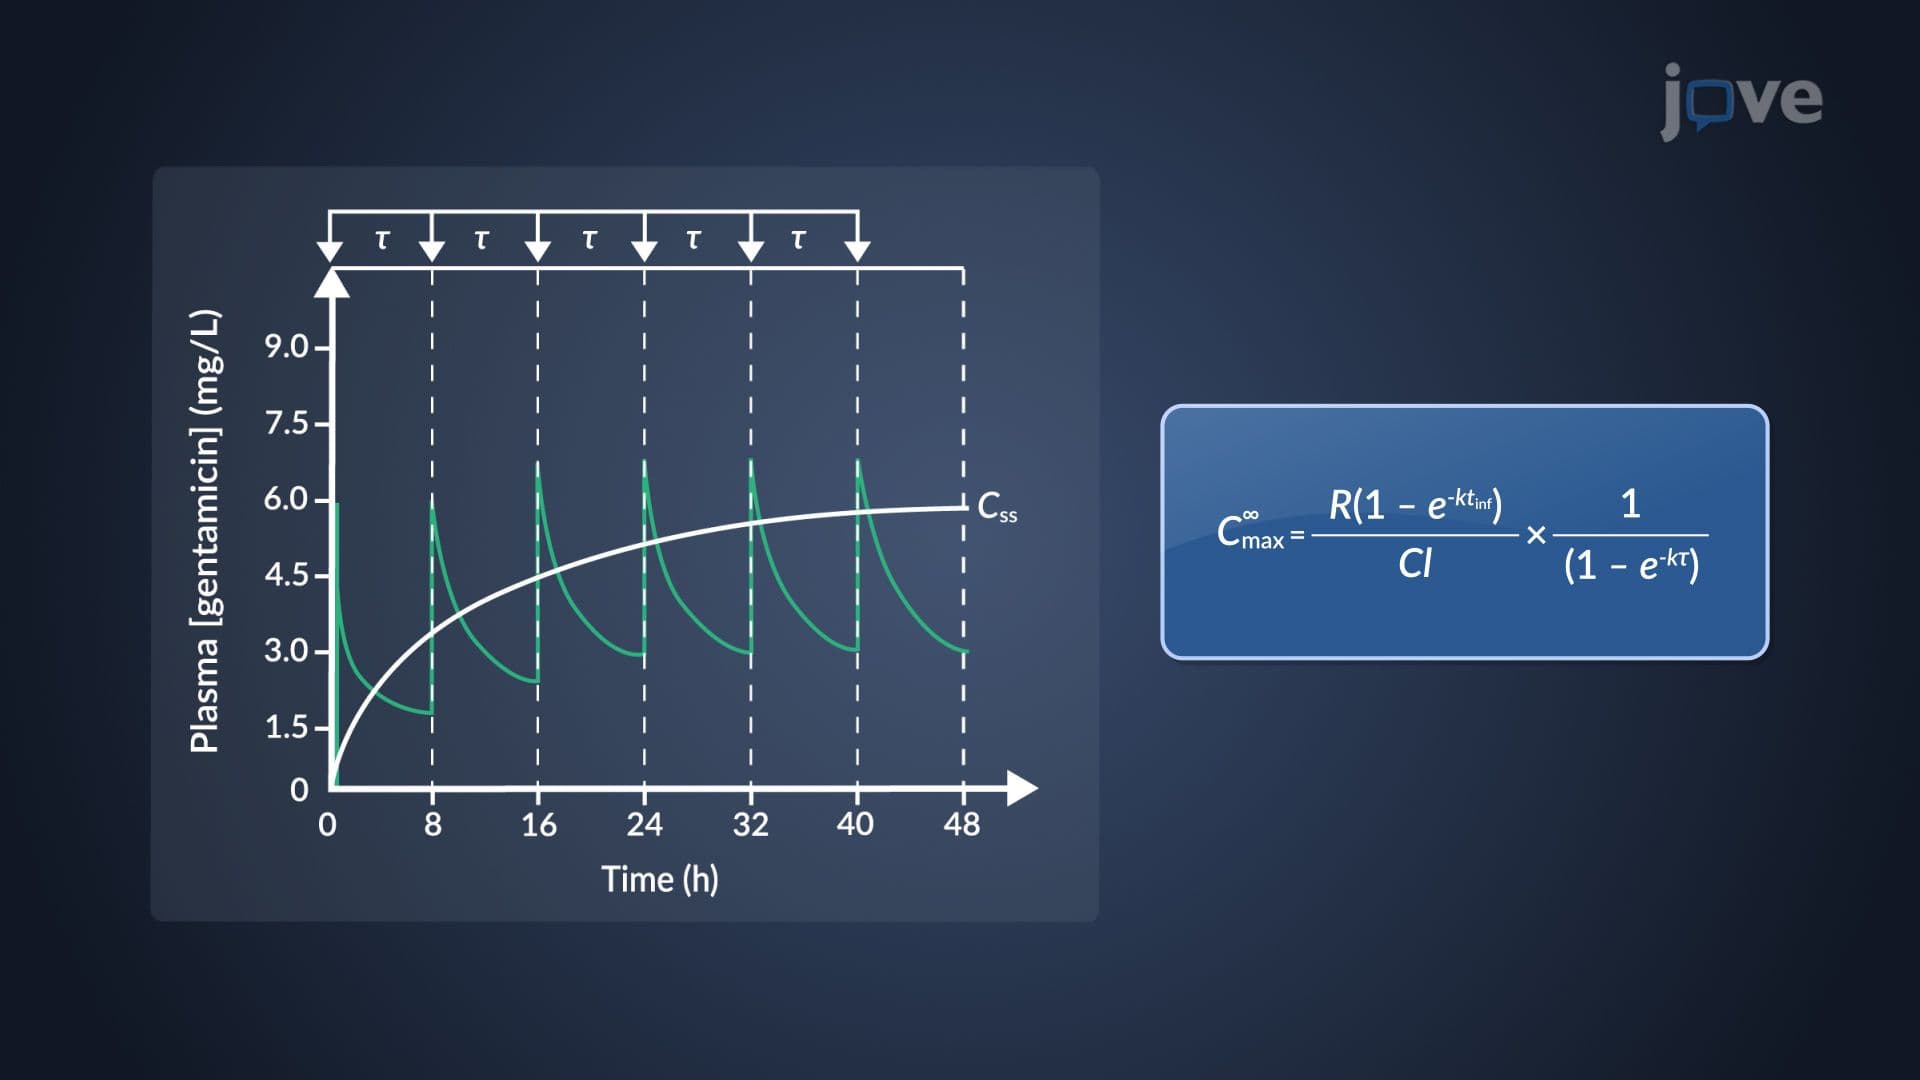
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations