Related Experiment Video
Updated: Aug 16, 2026


A Murine Model of Stent Implantation in the Carotid Artery for the Study of Restenosis
Published on: May 14, 2013
Systemic inflammation after drug-eluting stent placement
Prospero B Gogo1, David J Schneider, Matthew W Watkins
1Division of Cardiology, University of Vermont College of Medicine, 111 Colchester Avenue, Burlington, Vermont 05401, USA.

Insights
Drug-eluting stents (DES) reduce cardiac events compared to bare metal stents (BMS). This study found similar systemic inflammation markers (CRP, IL-6, IL1-Ra) after percutaneous coronary intervention (PCI) with either stent type, suggesting inflammation is not the key factor.
Area of Science:
- Cardiology
- Interventional Cardiology
- Inflammation Biology
Background:
- Systemic inflammation post-coronary intervention is linked to increased cardiac event risk.
- Drug-eluting stents (DES) are associated with fewer cardiac events than bare metal stents (BMS).
- The potential role of reduced systemic inflammation in DES's improved outcomes requires investigation.
Purpose of the Study:
- To investigate if the reduced restenosis observed with DES is due to a blunted systemic inflammatory response compared to BMS.
- To compare the systemic inflammatory markers C-reactive protein (CRP), interleukin-6 (IL-6), and interleukin-1 receptor antagonist (IL1-Ra) after PCI with DES versus BMS.
Main Methods:
- A prospective registry of 75 patients undergoing percutaneous coronary intervention (PCI) was analyzed.
- Peripheral venous blood samples were collected pre-PCI and 24 hours post-stenting.
- Concentrations of CRP, IL-6, and IL1-Ra were measured using ELISA, with 11 patients excluded due to mixed stent use.
Main Results:
- Patients receiving BMS (n=29) showed a higher incidence of marker-positive acute coronary syndromes and vein graft PCI compared to DES (n=34).
- While baseline cytokine levels were lower in the DES group, both DES and BMS groups exhibited comparable, significant increases in CRP, IL-6, and IL1-Ra 24 hours post-PCI.
- A robust 300% relative increase in CRP was observed in both DES and BMS patients after controlling for baseline levels.
Conclusions:
- The systemic inflammatory response following PCI is similar for both DES and BMS.
- The observed reduction in restenosis with DES is unlikely to be mediated by attenuation of systemic inflammatory markers (CRP, IL-1Ra, IL-6).
- Further research may be needed to elucidate the mechanisms behind DES's improved clinical outcomes.
Background:
Systemic inflammation after coronary intervention identifies patients at increased risk of subsequent cardiac events. Cardiac events are less frequent after use of drug eluting stents (DES) compared with bare metal stents (BMS). Thus, we sought to determine whether attenuation of the systemic inflammatory response was contributing to the improved outcomes.
Methods:
A prospective registry was initiated in late 2003. Peripheral venous blood samples from 75 patients undergoing percutaneous coronary intervention (PCI) were obtained before PCI, and both 1 hour and 24 hours after stenting. The concentrations of C-reactive protein (CRP), interleukin-6 (IL-6) and interleukin-1 receptor antagonist (IL1-Ra) were determined by ELISA. Eleven patients were excluded from the analysis because they had both DES and BMS.
Results:
Patients treated with BMS (n=29) compared with DES (n=34) had a higher incidence of marker-positive acute coronary syndromes (40% vs. 17%, p=0.06), vein graft PCI (p=0.02) and a larger final balloon diameter (p=0.04). Consistent with the lower baseline clinical risk, pre-PCI concentrations of cytokines were lower in the DES group (p=0.04 for IL-6 and p=0.08 for CRP). Comparable and significant increases in CRP, IL-6 and IL1-Ra were evident 24 hours after PCI in patients treated with either DES or BMS. After controlling for baseline levels of CRP, there remained a similar and robust (300%) relative increase in CRP for both DES and BMS patients.
Conclusions:
The inflammatory response to PCI appears similar in those treated with DES and BMS. Accordingly, the reduction in restenosis after DES is likely not mediated by attenuation of the systemic markers CRP, IL-1Ra, or IL-6.
Related Concept Videos
 01:25
Acute Inflammation III: Local and Systemic Effects
 01:12
Chronic Inflammation: Introduction
 01:38
Inflammation
 01:25
Endocarditis I: Introduction
 01:18
Endocarditis III: Medical Management
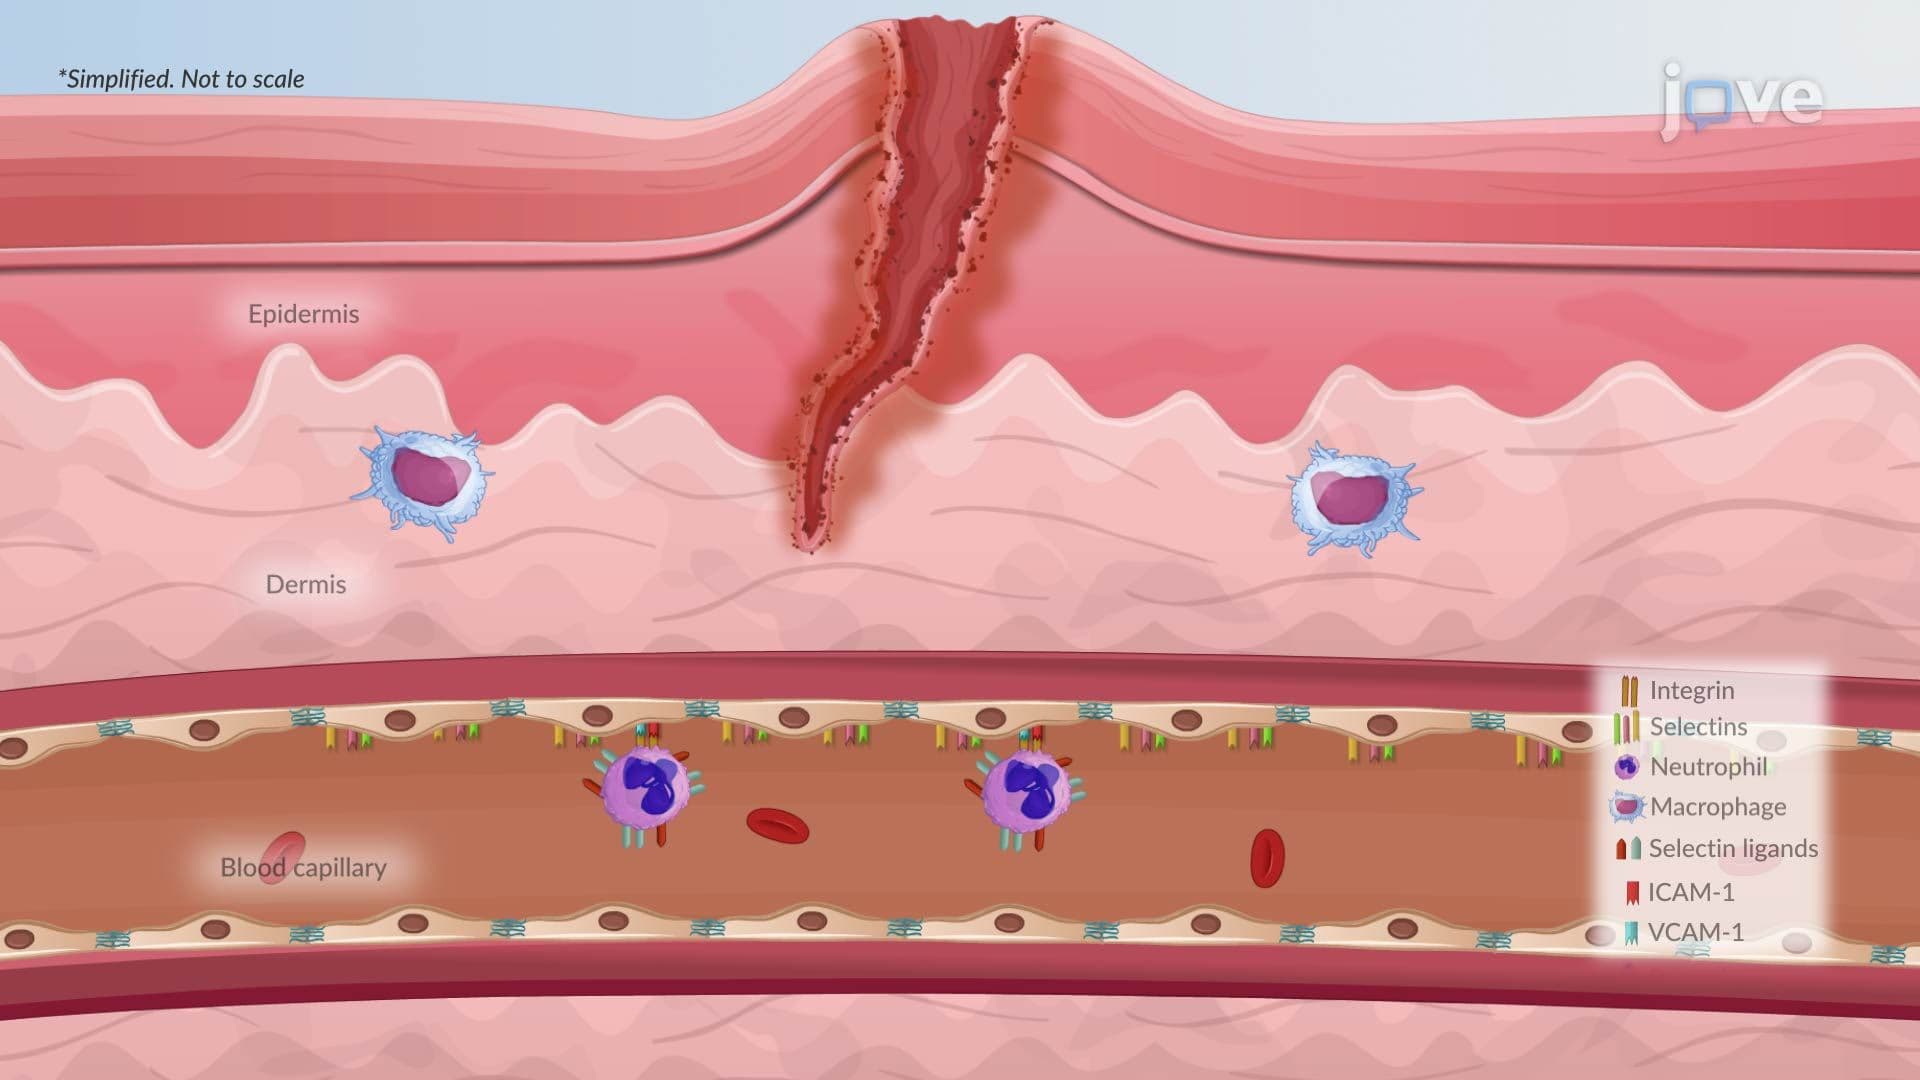 01:26
Acute Inflammation II: Cellular Phase