Predictive clinical factors for the differential diagnosis of childhood extratemporal seizures
Related Experiment Video
Updated: Aug 16, 2026
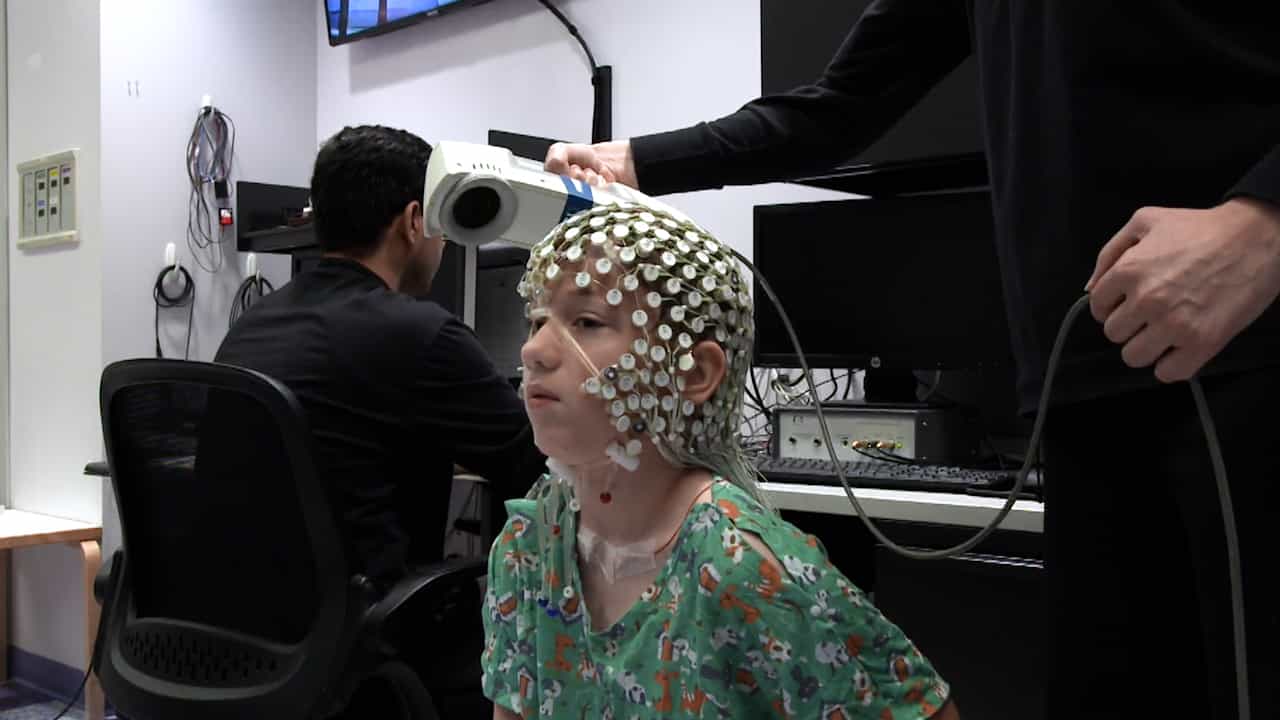
Electromagnetic Source Imaging in Presurgical Evaluation of Children with Drug-Resistant Epilepsy
Published on: September 20, 2024
András Fogarasi1, Ingrid Tuxhorn, Márta Hegyi
1Epilepsie-Zentrum Bethel, Bielefeld, Germany. fogarasi@bethesda.hu

Insights
Differentiating childhood frontal lobe epilepsy (FLE) and posterior cortex epilepsy (PCE) relies on specific clinical factors. Nocturnal seizure occurrence and aura type are key indicators for localizing epilepsy in children.
Area of Science:
- Pediatric Neurology
- Epileptology
- Clinical Neuroscience
Background:
- Childhood epilepsy presents diagnostic challenges, particularly differentiating between frontal lobe epilepsy (FLE) and posterior cortex epilepsy (PCE).
- Accurate localization is crucial for effective presurgical evaluation and treatment planning in pediatric epilepsy cases.
Purpose of the Study:
- To identify predictive clinical factors that distinguish between childhood frontal lobe epilepsy (FLE) and posterior cortex epilepsy (PCE).
- To evaluate the utility of semiologic seizure components and periictal signs in localizing epilepsy in children.
Main Methods:
- Analysis of 177 seizures from 35 children with extratemporal epilepsy who achieved seizure freedom post-surgery.
- Systematic observation of semiologic seizure components and periictal signs.
- Collection of clinical data including age at onset, auras, seizure frequency, nocturnal dominance, and surgical/histopathologic findings.
Main Results:
- Twenty patients were diagnosed with FLE and 15 with PCE.
- Nocturnal seizure dominance was significantly higher in FLE (p < 0.05).
- Exclusive seizure manifestations included visual aura, nystagmus, and versive seizures in PCE; somatosensory aura and hypermotor seizures in FLE. Tonic seizures were more frequent in FLE (p < 0.01).
Conclusions:
- Typical extratemporal epilepsy features seen in adults are often absent in children, especially infants.
- Ictal semiology provides limited differentiation between childhood FLE and PCE.
- Nocturnal seizure presentation and aura characteristics are valuable for localization, underscoring the importance of detailed history taking in pediatric presurgical evaluations.
Purpose:
To describe predictive clinical factors for the differentiation between childhood frontal lobe epilepsy (FLE) and posterior cortex epilepsy (PCE).
Methods:
Two independent, blinded investigators analyzed 177 seizures from 35 children (aged 11 months to 12 years) with extratemporal epilepsy selected by postoperative seizure-free outcome. Semiologic seizure components and different periictal signs were observed. Age at onset, auras, seizure frequency, and nocturnal dominance, as well as surgical and histopathologic data, were collected from medical charts.
Results:
Twenty patients had FLE, and 15 had PCE. Patients from both groups had daily seizures without significant differences in frequency but with higher nocturnal dominance in children with FLE (p < 0.05). Visual aura, nystagmus, and versive seizure were observed exclusively in the PCE group, whereas somatosensory aura and hypermotor seizures appeared only in FLE. Tonic seizures were significantly more frequent in FLE (p < 0.01), whereas the presence of clonic seizure (FLE; p = 0.07) and postictal nose-wiping (PCE; p = 0.05) showed only a trend to localize the seizure-onset zone. Myoclonic seizures, epileptic spasms, psychomotor seizures, atonic seizures, oral and manual automatisms, as well as vocalization and eye deviation appeared in both groups without significant differences in their frequency.
Conclusions:
Characteristic features described in adults' extratemporal epilepsies were frequently missing during childhood seizures, especially in infants and preschool children. Ictal features help only a little in differentiating childhood FLE from PCE. Nocturnal appearance and the type of aura have high localizing value; therefore an accurate history taking is still an essential element of pediatric presurgical evaluation.
More Related Videos
 10:22
Interictal High Frequency Oscillations Detected with Simultaneous Magnetoencephalography and Electroencephalography as Biomarker of Pediatric Epilepsy
Published on: December 6, 2016
 07:35
Behavioral Characterization of Pentylenetetrazole-induced Seizures: Moving Beyond the Racine Scale
Published on: July 8, 2025
Related Concept Videos
 01:22
Epilepsy ll: Types
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types:
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:20
Seizures l: Introduction