Related Experiment Video
Updated: Aug 16, 2026


Purification and Transplantation of Myogenic Progenitor Cell Derived Exosomes to Improve Cardiac Function in Duchenne Muscular Dystrophic Mice
Published on: April 10, 2019
The heart in muscular dystrophy
Larry W Markham1, Robert L Spicer, Linda H Cripe
1Cincinnati Children's Hospital Medical Center, Department of Pediatrics, Division of Pediatric Cardiology, Cincinnati, OH 45229, USA.

Insights
Pediatricians must monitor for heart issues in muscular dystrophy (MD) patients, as symptoms can be subtle. Early detection and treatment of cardiac involvement improve outcomes for children with MD.
Area of Science:
- Cardiology
- Neurology
- Pediatrics
Background:
- Muscular dystrophy (MD) is a group of genetic disorders characterized by progressive skeletal muscle weakness.
- Cardiac involvement is a common and serious complication of MD, significantly contributing to morbidity and mortality.
- Subclinical cardiac involvement is frequent, making early detection challenging.
Purpose of the Study:
- To emphasize the importance of vigilant cardiac monitoring in pediatric patients with MD.
- To highlight the need for early identification and management of cardiac complications.
- To discuss current and future therapeutic strategies for managing cardiac involvement in MD.
Main Methods:
- Review of clinical presentation and diagnostic approaches for cardiac involvement in MD.
- Discussion of noninvasive cardiac testing modalities.
- Analysis of current treatment strategies and their impact on disease outcomes.
Main Results:
- Cardiac involvement in MD patients can present with minimal or no overt symptoms.
- Thorough clinical evaluation, including interval history and physical examination, is crucial.
- Noninvasive cardiac testing aids in the early detection of subclinical cardiac dysfunction.
Conclusions:
- Healthcare professionals must maintain a high index of suspicion for cardiac involvement in all pediatric MD patients.
- Timely and appropriate cardiac evaluation and management can mitigate disease progression and improve survival.
- While genetic engineering offers future hope, current advancements in clinical care and supportive management significantly benefit affected children.
Abstract:
Pediatricians and other healthcare professionals need to be alert to the presence and progression of cardiac involvement in patients with MD. The signs and symptoms of cardiac involvement may be minimal, necessitating careful interval history, physical examination, and noninvasive cardiac testing. Available treatment strategies may reduce disease morbidity and mortality. It is reasonable to expect that a child who has skeletal muscle weakness from MD may have cardiac involvement, even if it is subclinical. Treatment of the muscular dystrophies through genetic engineering is a future dream. However, the improvements in clinical care, evaluation and treatment standards, and multidisciplinary supportive care are able to benefit the current generation of children.


Related Concept Videos
 01:21
Satellite Stem Cells and Muscular Dystrophy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:13
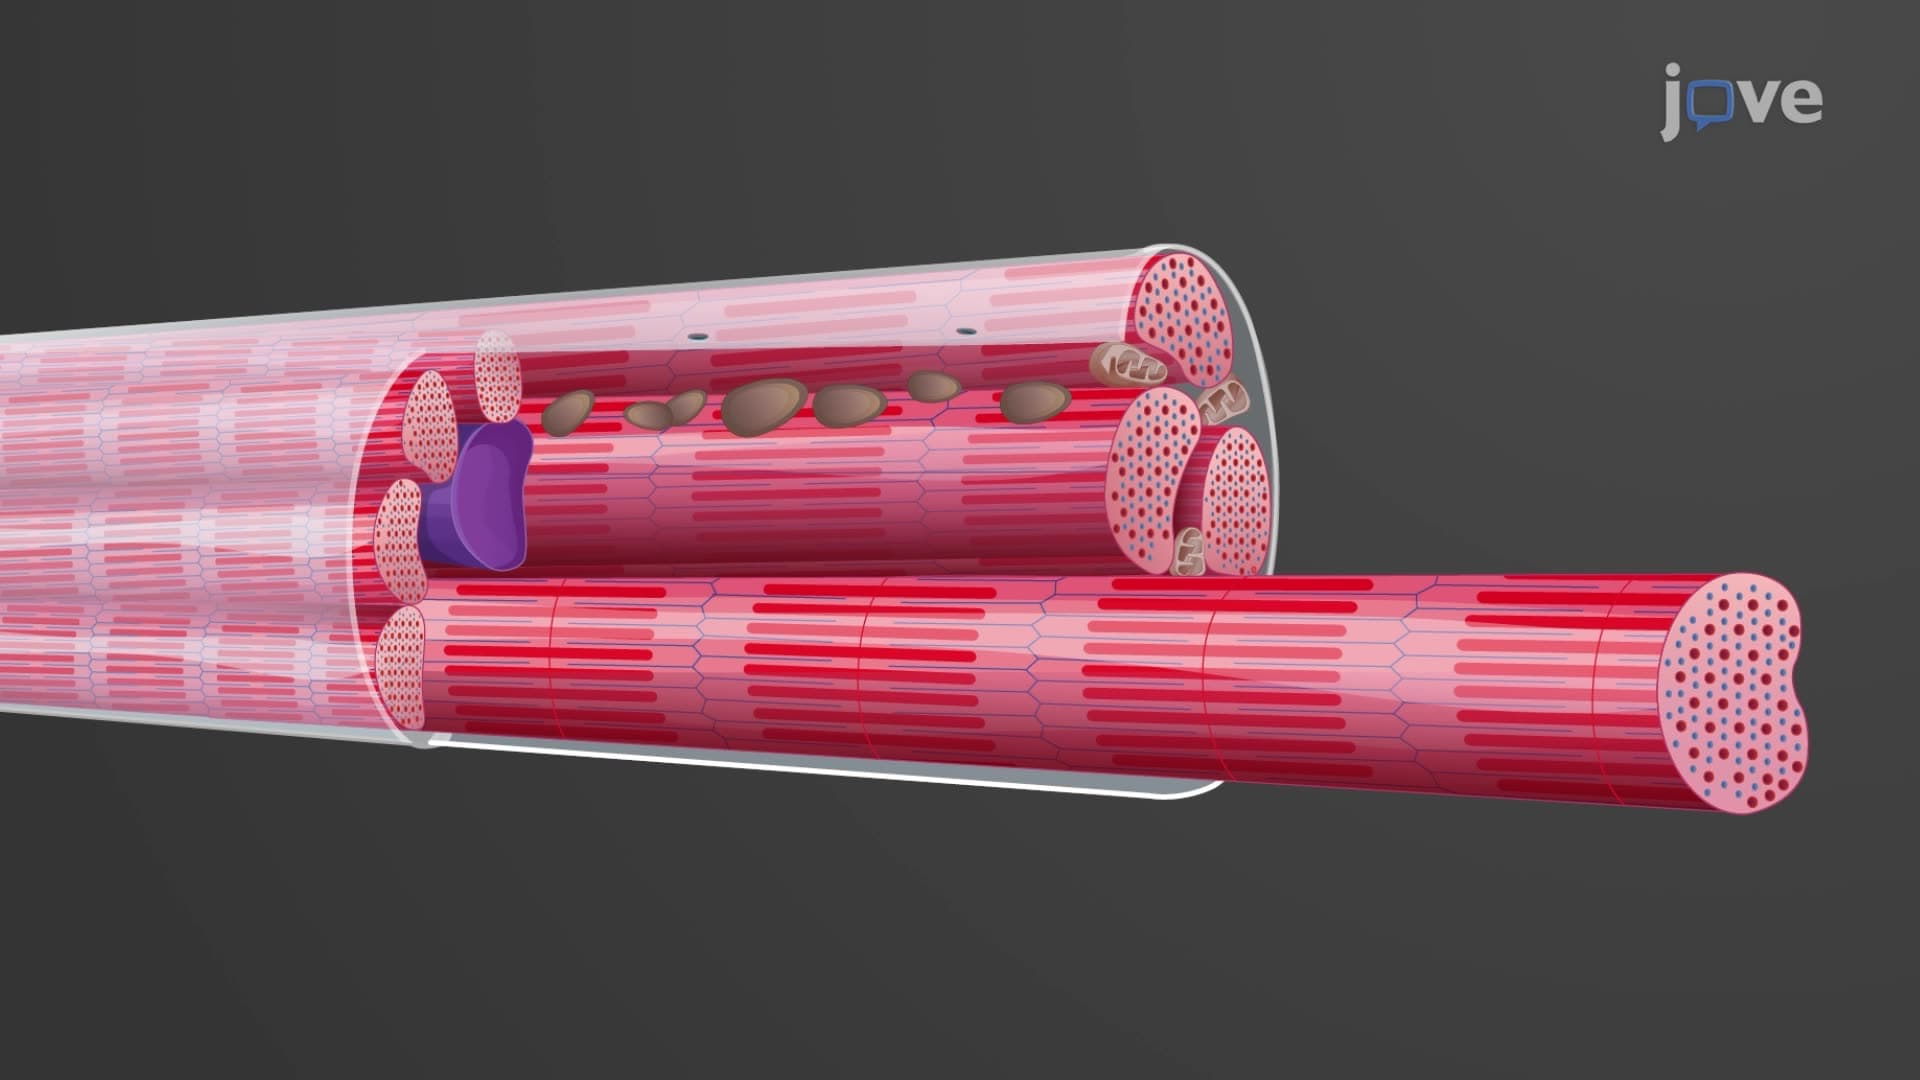
Structure of Cardiac Muscles
Compared to skeletal muscles, cardiac muscle cells are small and mostly have a single nucleus. Additionally, they are usually...
 01:29
Heart Failure II: Pathophysiology
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:27
Specialized Characteristics of Cardiac Muscles
Cardiac muscle cells are smaller than skeletal muscles, averaging 10–20 mm in diameter and 50–100 mm in length. However, they have large energy demands for continuous contraction and relaxation. This energy is almost exclusively derived from aerobic metabolism of energy reserves in...