Related Experiment Video
Updated: Aug 16, 2026

Drug Treatment and In Vivo Imaging of Osteoblast-Osteoclast Interactions in a Medaka Fish Osteoporosis Model
Published on: January 1, 2017
Effects of alendronate and calcitonin on bone mineral density in postmenopausal osteoporotic women. An observational
Miroslava Hejdova1, Vladimir Palicka, Zdenek Kucera
1Department of Social and Clinical Pharmacy, Faculty of Pharmacy in Hradec Kralove, Charles University in Prague, Heyrovskeho 1203, 500 05, Hradec Kralove, Czech Republic. hejdova@faf.cuni.cz

Objective:
Alendronate and calcitonin are antiresorptive drugs that were used for the treatment of postmenopausal osteoporosis and were shown to increase bone mineral density (BMD). However, the effect of both drugs in daily clinical practice may differ from that observed in clinical trials.
Method:
About 50 postmenopausal osteoporotic women were observed during their first year of treatment. Among them, 32 patients used alendronate and 18 used calcitonin. Lumbar spine and femoral neck BMD were measured by dual energy X-ray absorptiometry (DXA) at baseline and after 1 year of therapy. Biochemical markers (B-ALP--bone-specific alkaline phosphatase, OTC--osteocalcin and DPD/UCr--deoxypyridinoline/creatinine ratio) of bone metabolism were measured at baseline and 6 months later. Patient compliance was assumed by tablet counting and verified at interview. Each patient was further questioned about her attitude towards the treatment, as well as her dairy product intake, physical activity, use of other medications, smoking and social status.
Main Outcome Measure:
(1) Annual percent change in BMD in lumbar spine and femoral neck after the one-year treatment with either alendronate or calcitonin. (2) The change in biochemical markers of bone turnover.
Results:
The lumbar spine BMD significantly increased by 7.0% (P < 0.001), the femoral neck BMD by 4.3% (P < 0.01). OTC, B-ALP and DPD/UCr decreased significantly during the therapy with alendronate. Compliance with therapy was 79% (95% CI 68-90%). In the calcitonin-treated group, the lumbar spine BMD significantly increased by 3.1 % (P < 0.05), while the femoral neck BMD remained unchanged. OTC, B-ALP and DPD/UCr did not change significantly during the treatment with calcitonin. Compliance with calcitonin therapy was 87% (95% CI 63-110%). The annual change of BMD in both treatment groups was independent on all questioned factors.
Conclusion:
In daily practice, alendronate enhanced significantly BMD both in lumbar spine and femoral neck. Calcitonin showed increase only in the lumbar spine BMD.
Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:40
Bone Remodeling
 00:51
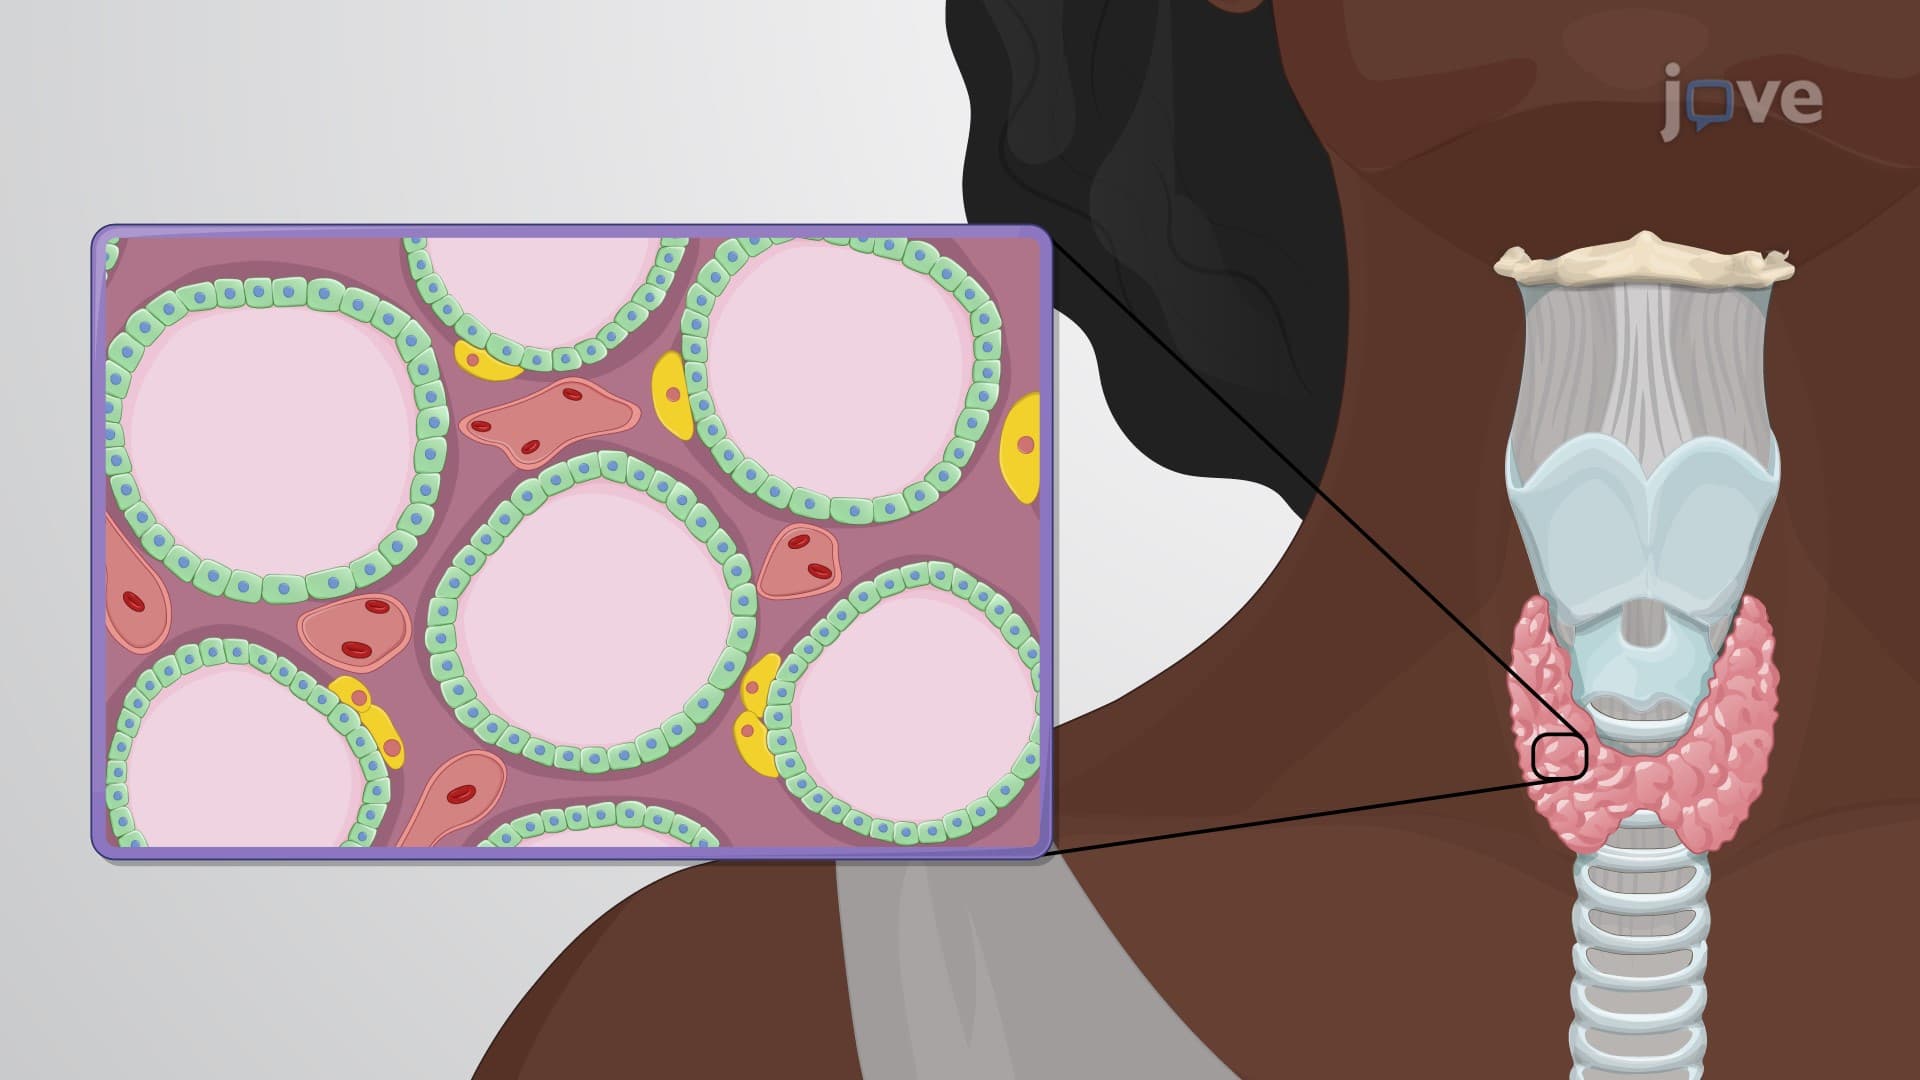
Synthesis and Functions of Calcitonin
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:21
Skeleton and Calcium Homeostasis