Related Experiment Video
Updated: Aug 16, 2026


Optocardiography and Electrophysiology Studies of Ex Vivo Langendorff-perfused Hearts
Published on: November 7, 2019
EC-coupling in normal and failing hearts
Jon Arne Birkeland1, Ole M Sejersted, Tore Taraldsen
1Institute for Experimental Medical Research, Ullevål University Hospital, University of Oslo, Oslo, Norway. j.a.birkeland@medisin.uio.no

Insights
Systolic heart failure involves impaired heart cell function, specifically altered calcium (Ca2+) handling. Reduced sarcoplasmic reticulum (SR) Ca2+ load, likely due to impaired SR Ca2+ ATPase (SERCA) function, contributes to this dysfunction.
Area of Science:
- Cardiology
- Cellular Biology
- Biochemistry
Background:
- Systolic heart failure stems from either reduced cardiomyocyte numbers or impaired contractile function.
- Myocardial failure, characterized by impaired cellular contractility, has an unknown pathophysiological basis but involves altered calcium (Ca2+) handling.
- Despite unaltered L-type Ca2+ current, sarcoplasmic reticulum (SR) Ca2+ load is reduced in human heart failure, potentially explaining decreased contractility.
Purpose of the Study:
- To investigate the underlying mechanisms of reduced SR Ca2+ load in systolic heart failure.
- To elucidate the role of specific cellular components, including RyR, SERCA, and NCX, in the pathophysiology of myocardial failure.
- To identify potential therapeutic targets for systolic dysfunction.
Main Methods:
- Review and synthesis of existing literature on calcium handling in heart failure.
- Analysis of proposed mechanisms for reduced SR Ca2+ load: RyR leak, SERCA impairment, and NCX upregulation.
- Consideration of findings from studies involving genetically modified models.
Main Results:
- Reduced SR Ca2+ load is a key feature of failing hearts, correlating with diminished contractility.
- Three primary mechanisms for reduced SR Ca2+ load are proposed: RyR leak, impaired SERCA function, and increased NCX function.
- Evidence suggests impaired SERCA function is a likely primary mechanism, while increased NCX function may be secondary but therapeutically relevant.
Conclusions:
- Impaired SR Ca2+ ATPase (SERCA) function is a probable primary cause of systolic dysfunction in heart failure.
- Modulating the Na+/Ca2+-exchanger (NCX) may offer therapeutic benefits.
- Further research, particularly using genetically modified models, is crucial for a comprehensive understanding of these mechanisms.
Abstract:
Systolic heart failure may be due to too few cardiomyocytes, or to reduced contractile function of the heart cells. In the latter situation the myocardial function is impaired and this condition is called myocardial failure. The pathophysiological mechanism behind this cellular defect is not known, but Ca2+ handling is altered. Although the most important trigger of sarcoplasmatic reticulum (SR) Ca2+ release, the L-type Ca2+ current, seems to be unaltered, SR Ca2+ load is reduced in human heart failure. This could explain the reduced contractility observed in failing hearts. Three possible mechanisms have been suggested to explain the reduction in SR Ca2+ load. They are leak through the SR Ca2+ release channel (RyR), impaired SR Ca2+ ATPase (SERCA) function and increased Na+/Ca2+-exchanger (NCX) function. Leak through RyR is not consistently found. Increased NCX function is probably secondary to a change in Ca2+ handling, and thus not a primary mechanism, but blockade of the NCX might have therapeutic potential. Reduced SERCA function is probably a primary mechanism for the observed systolic dysfunction, and further insight is to be gained through studies in genetically modified models.


Related Concept Videos
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:30
Cardiac Action Potential
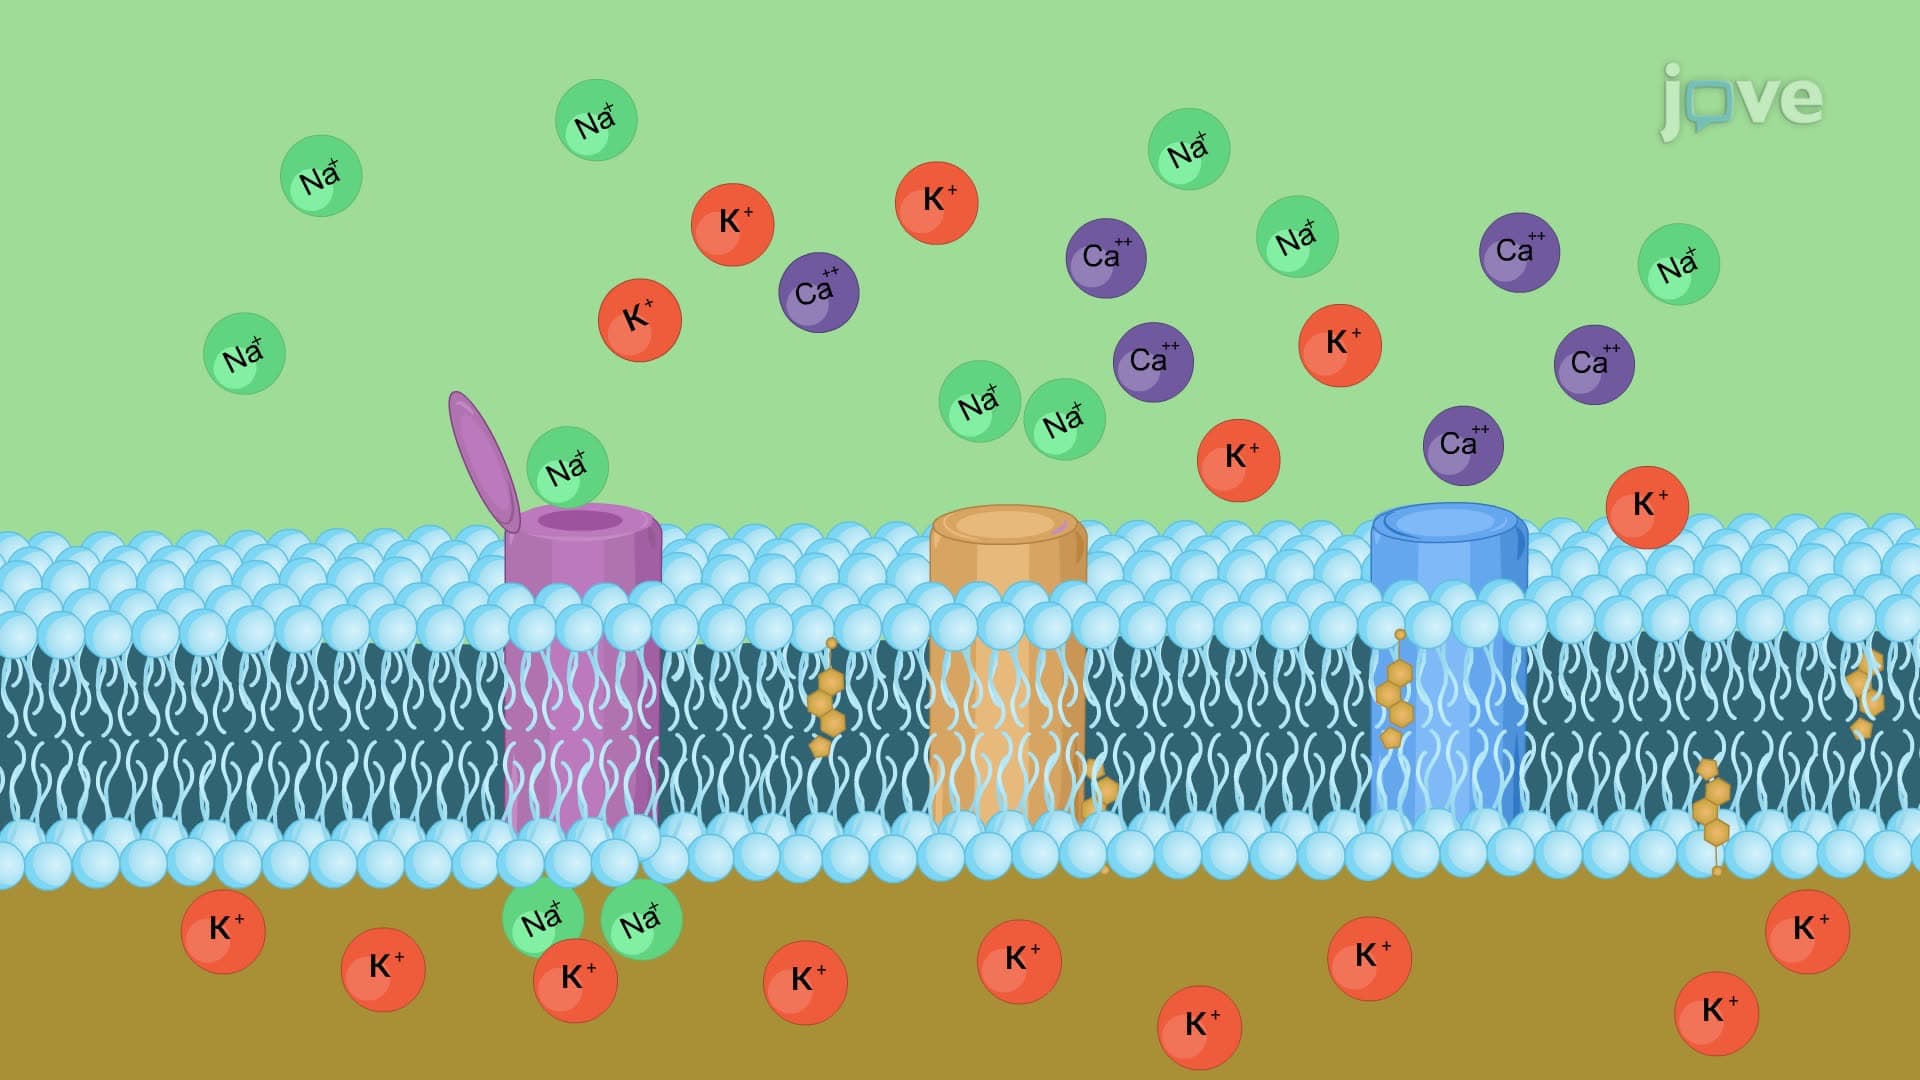
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:29
Heart Failure II: Pathophysiology
 01:28
Mechanism of Cardiac Arrhythmias