Related Experiment Video
Updated: Aug 16, 2026
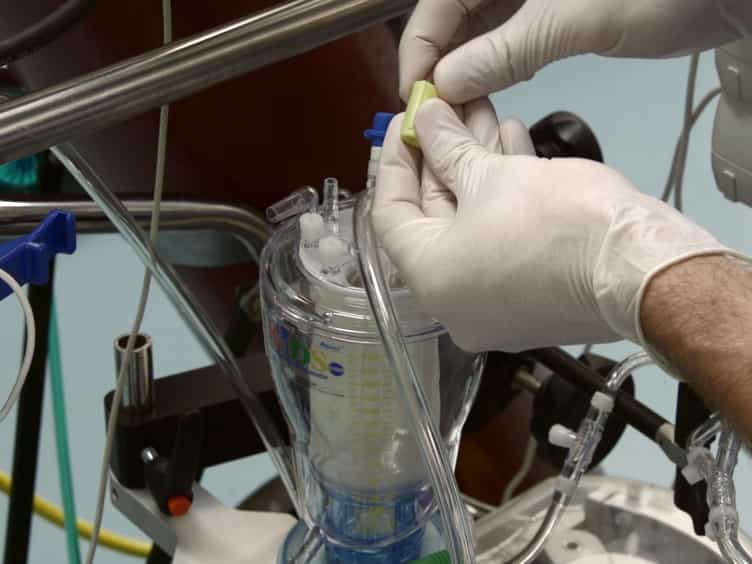

Normothermic Ex Vivo Kidney Perfusion for the Preservation of Kidney Grafts prior to Transplantation
Published on: July 15, 2015
Partial nephrectomy with perfusion cooling for imperative indications: a 24-year experience
Joachim Steffens1, Ulrich Humke, Manfred Ziegler
1Department of Urology and Paediatric Urology, St. Antonius-Hospital Eschweiler, Homburg/Saar, Germany. jsteffans.sah-eschweiler@clinet.de

Objective:
To report our 24-year experience with open nephron-sparing surgery for renal tumours, using cold ischaemia achieved by renal artery perfusion, as partial nephrectomy for imperative indications is a surgical challenge.
Patients And Methods:
From 1980 to 2004, open partial nephrectomy was performed in 717 patients; of these, 65 (9.1%) with a solitary kidney, synchronous bilateral tumours or renal failure in the opposite kidney (imperative indication) had surgery under cold ischaemia, achieved by continuous perfusion of Ringer's lactate at 4 degrees C through the renal artery, which was clamped and cannulated. The tumour was resected in a bloodless field, with biopsies taken from the tumour bed. Focusing on patients with an imperative indication and cold perfusion, we report our perfusion technique, and the ischaemia time, complication rate and cancer-specific survival rate of these patients.
Results:
The mean (SD, range) operative duration was 132 (103, 91-252) min and ischaemia time 49 (37, 31-71) min. The most common complications were postoperative haemorrhage in 19%, urinary fistula in 8% and acute renal failure in 6% of patients. There were no specific complications related to the perfusion technique (renal artery stenosis, renal artery or vein thrombosis). The mean (SD, range) long-term follow-up of 95 (71, 4.3-231) months showed increased but constant creatinine values (95 micromol/L before, 182 micromol/L after surgery; P < 0.05) with no need for long-term dialysis. The tumour-specific survival rate was 94%, 76% and 76% after 1, 5 and 10 years, respectively.
Conclusions:
Partial nephrectomy under cold ischaemia remains reserved for selected patients with renal tumours with an imperative indication. The technique provides excellent intraoperative visibility in an absolutely bloodless field, allows surgery with no pressure of time, and makes ex vivo workbench surgery with autotransplantation unnecessary. Perfusion cooling allows good tumour-specific long-term results, with stable residual kidney function sufficient to prevent dialysis.


Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Kidney Transplant I: Introduction