[Non-traumatic acute transverse spinal cord syndromes]
Related Experiment Video
Updated: Aug 6, 2026

Spinal Cord Lateral Hemisection and Asymmetric Behavioral Assessments in Adult Rats
Published on: March 24, 2020
1Neurologische Klinik und Poliklinik der Universität, Inselspital, Bern. christian.hess@insel.ch

Abstract:
Differential diagnosis of non-traumatic, acute transverse spinal cord syndromes should cover compressive myelopathy (mostly hematomas or tumors), inflammatory myelitis and vascular myelopathies. Since acute pathologies of the spinal cord primarily result in flaccid para- or tetraparesis accompanied by areflexia or hyporeflexia (spinal shock), acute polyradiculoneuritis and the cauda equina syndrome must also be weighed into the differential diagnosis. Paraplegia may ultimately also be of psychogenic origin. The clinical picture is characterized by the rapidity of progression, the possible involvement of pain, and the specific pattern of the deficits. When the latter occurs, localization of the rostrocaudal level and transverse spread are crucial factors. Depending on the affected structure, one differentiates between anterior spinal cord syndromes (anterior spinal artery syndrome, selective involvement of the anterior horn, centromedullary syndromes), long pathway syndrome (isolated in the posterior bundle or combined with pyramidal pathways) and the unilateral Brown-Séquard's syndrome. Infectious myelitis is usually caused by neurotropic viruses or mycoplasmata in conjunction with meningitis or encephalitis; these in turn either induce transverse myelitis accompanied by severe sensomotor deficits or chiefly affect the gray matter, then producing a pattern similar to anterior spinal artery syndrome. In the case of non-infectious inflammatory myelitis, one must differentiate between multiple sclerosis, acute disseminated encephalomyelitis (ADEM), idiopathic transverse myelitis and that of the neuromyelitis optica or Devic's disease. Symptomatic transverse myelitis can also be present in association with connective tissue diseases (e.g. SLE, Behçet's disease, Sjögren's syndrome) or sarcoidosis. Notably, when ischemic spinal infarcts are involved, their onset is frequently painful and their manifestation typically subacute, rather than apoplectiform.

Related Concept Videos
 01:54
The Spinal Cord
 01:16
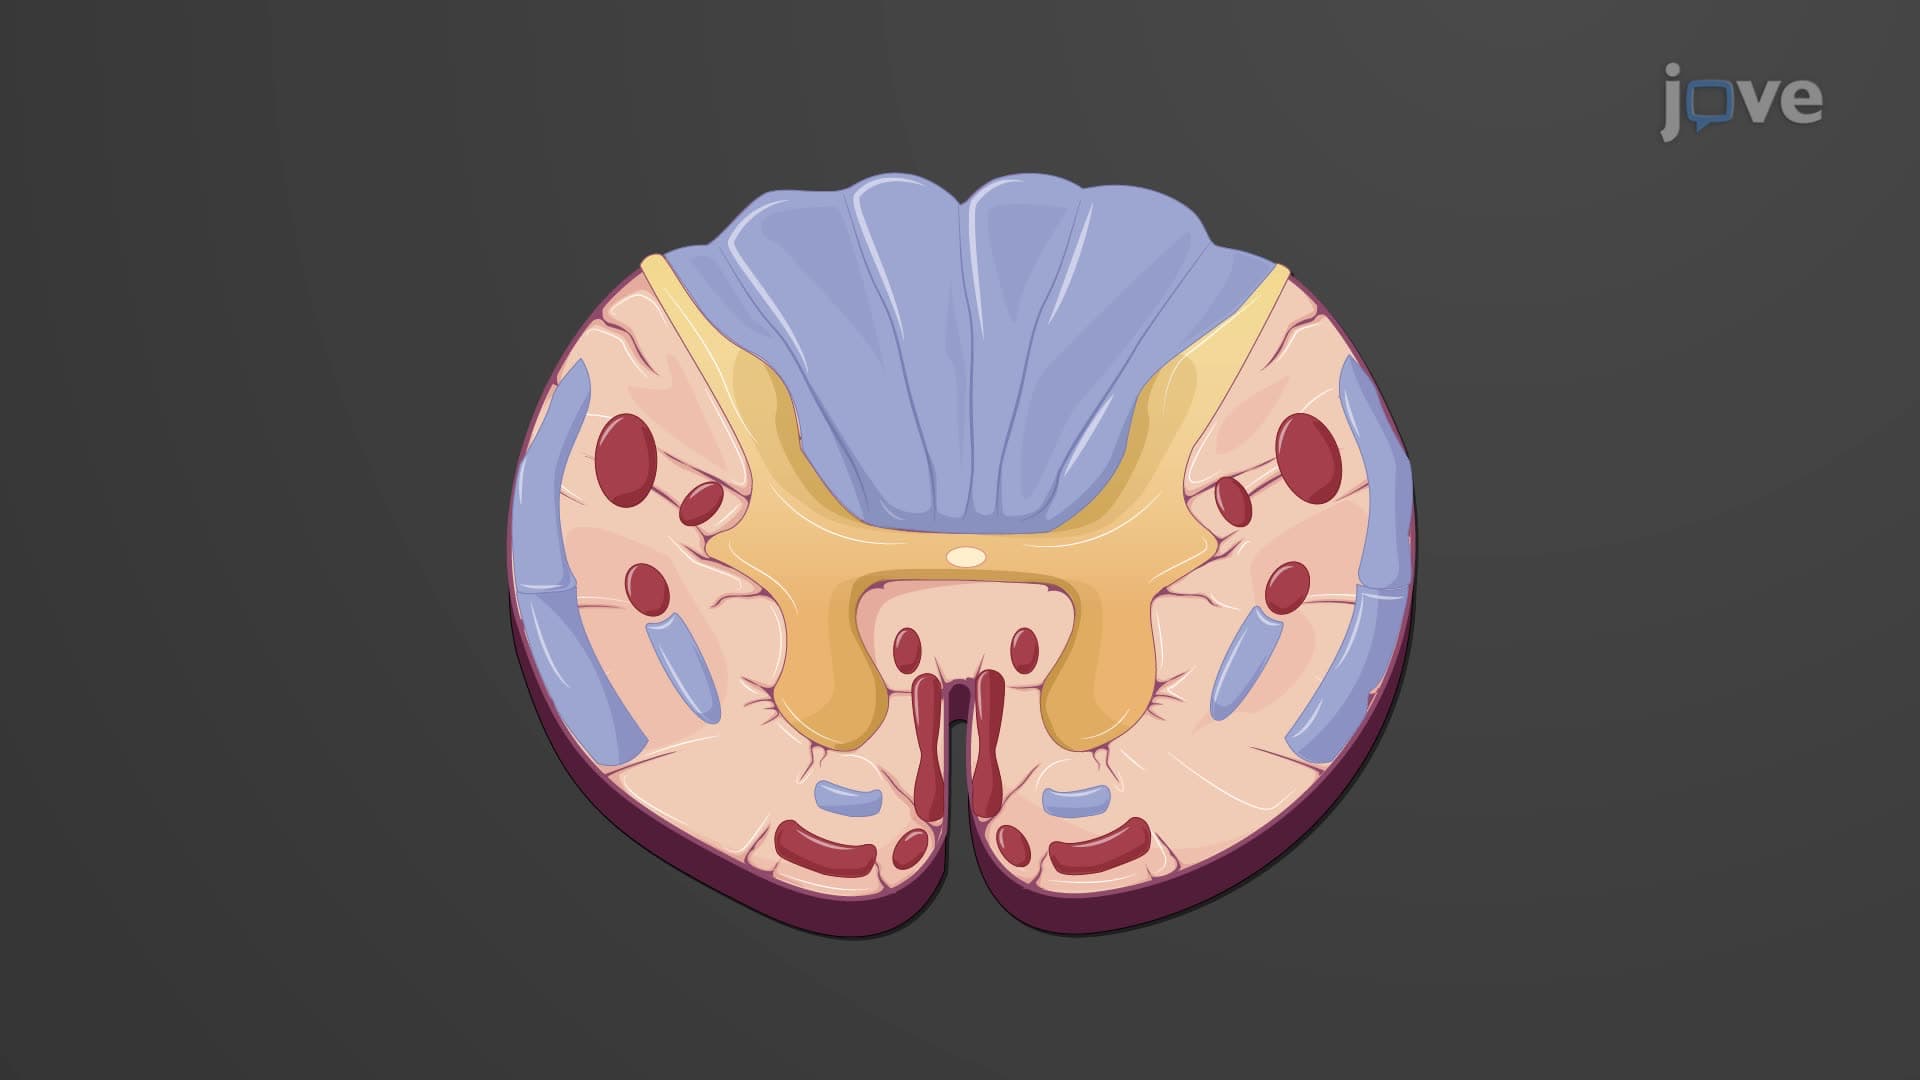
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray matter is...
 01:29
Tetanus
 01:14
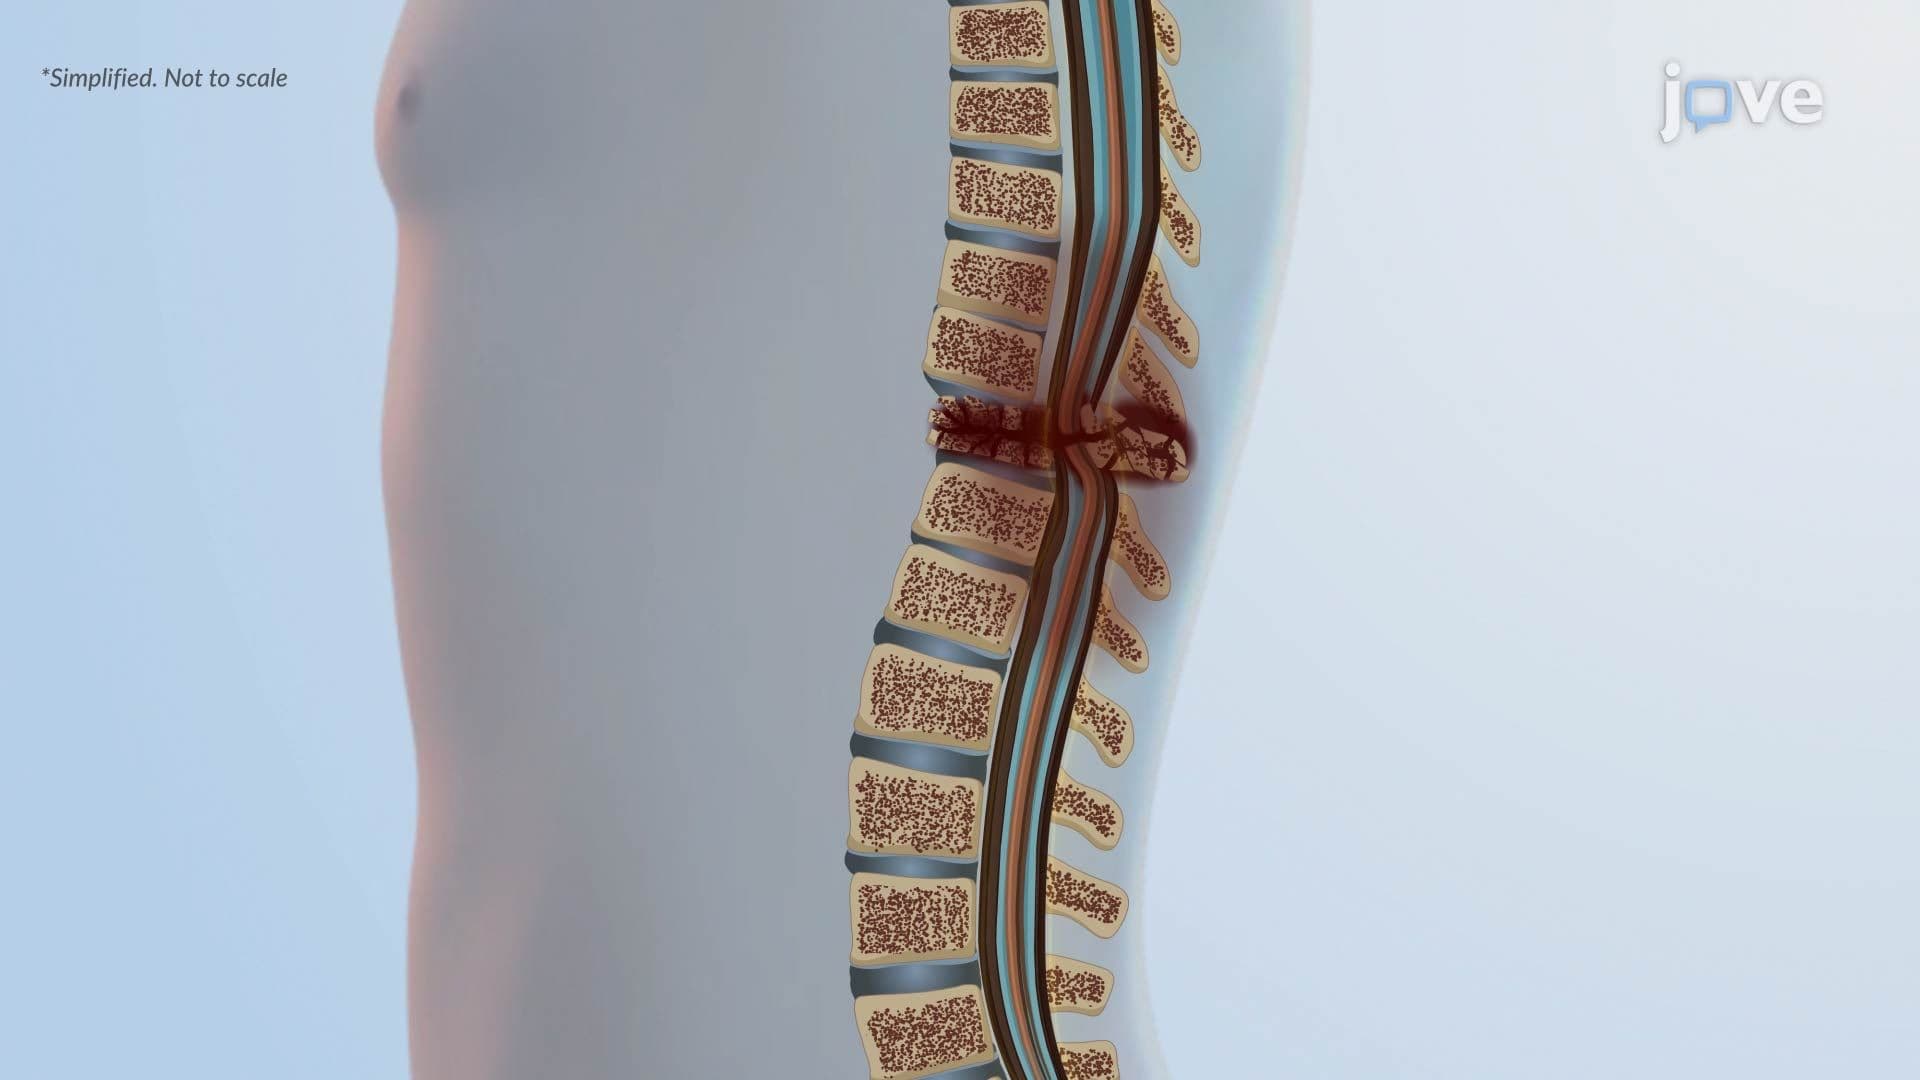
Spinal Cord Injury ll: Pathophysiology
 01:29
Herniated Intervertebral Disc l: Introduction
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology