Related Experiment Video
Updated: Aug 16, 2026


Purification of Hepatocytes and Sinusoidal Endothelial Cells from Mouse Liver Perfusion
Published on: February 12, 2018
Removal of P-cresol sulfate by hemodialysis
Andres W Martinez1, Natalie S Recht, Thomas H Hostetter
1Department of Medicine, Veterans Association, Palo Alto, California, USA.

Abstract:
Protein-bound solutes are poorly cleared by dialysis. Among the most extensively studied of these solutes is p-cresol, which has been shown to be toxic in vitro. This study examined the form in which p-cresol circulates and quantified its removal by hemodialysis. HPLC analysis of plasma from hemodialysis patients contained a peak whose mobility corresponded to synthetic p-cresol sulfate (PCS) but no detectable unconjugated p-cresol. Treatment with sulfatase resulted in recovery of this peak as p-cresol, confirming its identity. Subsequent studies compared the removal of PCS and another protein-bound solute, indican, to the removal of urea during clinical hemodialysis treatments. PCS and indican were 94 +/- 1% and 93 +/- 2% bound to plasma protein, respectively. Protein-binding caused a predictable decrease in measured dialytic clearance, which averaged 20 +/- 4 ml/min for PCS and 25 +/- 5 ml/min for indican as compared with 260 +/- 20 ml/min for urea. Volumes of distribution for the protein-bound solutes were greater than the plasma volume, averaging 15 +/- 7 L for PCS and 14 +/- 3 L for indican as compared with 37 +/- 7 for urea. Solute reduction ratios were 20 +/- 9% for PCS, 30 +/- 7% for indican, and 69 +/- 5% for urea. We conclude that p-cresol circulates in the form of its sulfate conjugate, PCS. PCS is poorly removed by hemodialysis because its clearance is limited by protein binding and the ratio of its volume of distribution to its clearance is high.


Related Concept Videos
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:30
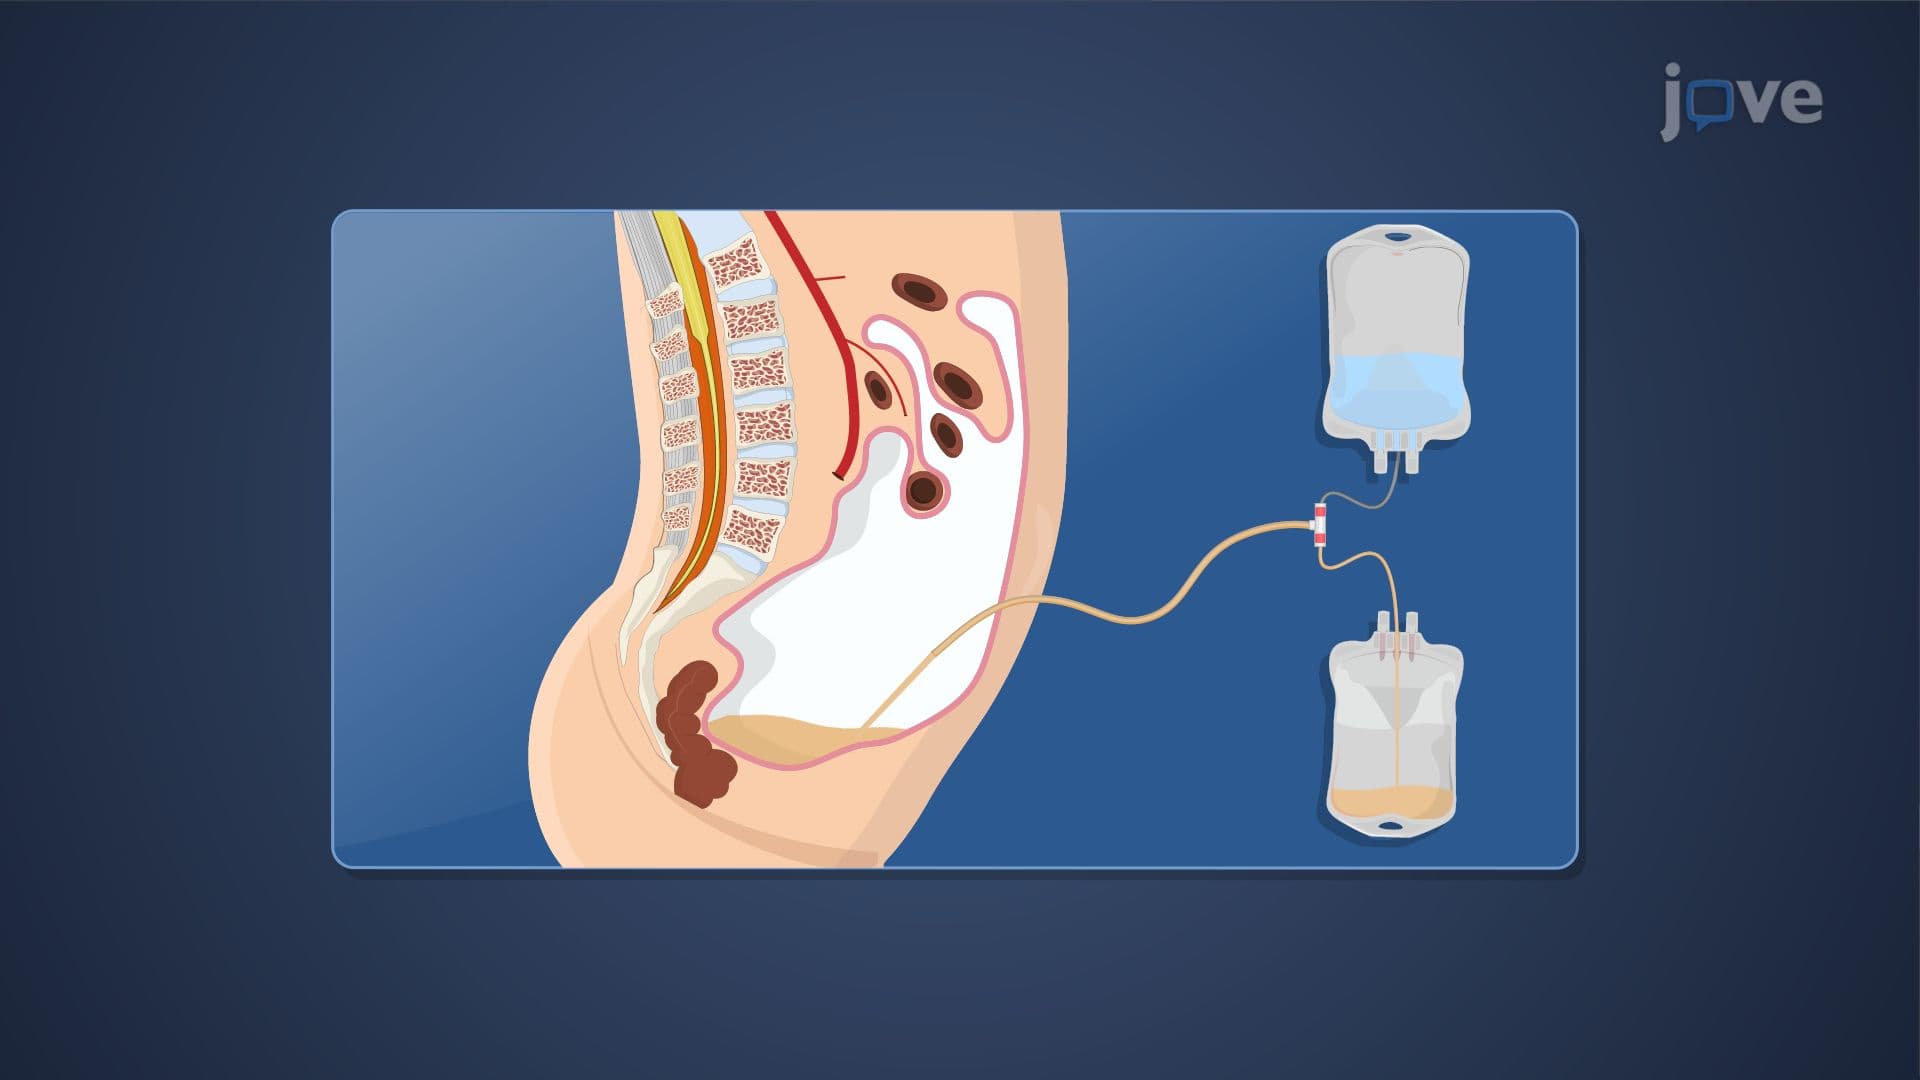
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:15
Dialysis
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:26
Enhanced Elimination of Poison
Antidotes serve a crucial role in counteracting the effects of poison by inhibiting enzymes responsible for producing harmful drug metabolites. In some cases, these toxic metabolites can be neutralized by endogenous cosubstrates, which are maintained at specific concentrations to prevent interaction with cellular macromolecules and subsequent cell death.
Renal excretion is the...