Related Experiment Videos

Diffuse idiopathic neuroendocrine cell hyperplasia causing severe airway obstruction in a patient with a carcinoid

Heiner Adams1, Thomas Brack, Peter Kestenholz

  • 1Department of Pulmonary Medicine, Zurich University Hospital, Zurich, Switzerland.

Related Concept Videos

Esophageal Strictures-I: Introduction01:30

Esophageal Strictures-I: Introduction

Esophageal strictures involve abnormal narrowing or tightening of the esophagus. They vary in length and severity, ranging from mild constriction to complete obstruction, and are classified as benign (noncancerous) or malignant (cancerous).
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
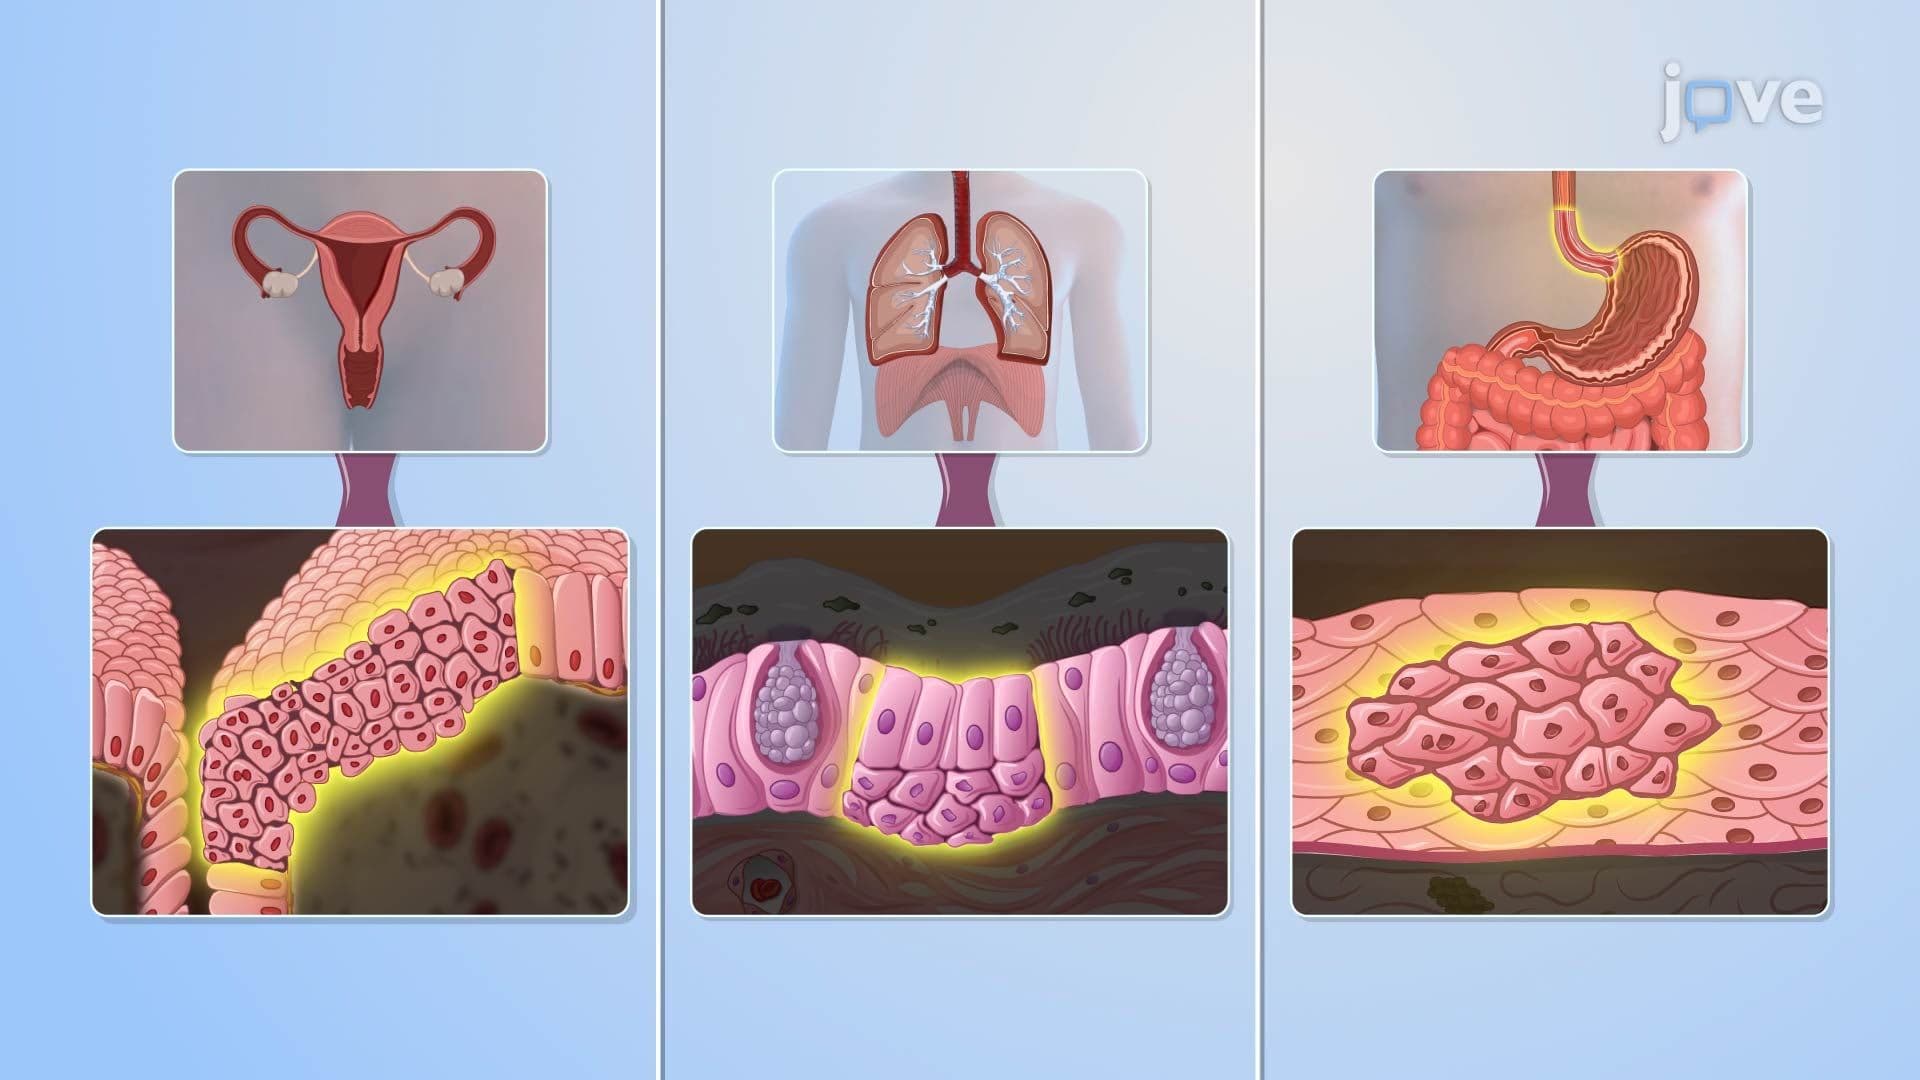
Cellular Adaptation IV: Dysplasia and Metaplasia01:24

Cellular Adaptation IV: Dysplasia and Metaplasia

DysplasiaDysplasia refers to abnormal changes in the size, shape, and organization of mature cells, characterized by pleomorphism, nuclear abnormalities, and increased mitotic activity. It commonly affects epithelial tissues, including the cervix, gastrointestinal tract, respiratory mucosa, and endometrium. Although it may occur alongside hyperplasia, dysplasia is not a true adaptive response but a preneoplastic change with potential to progress to cancer.When confined above the basement...
Esophageal Achalasia01:27

Esophageal Achalasia

Esophageal achalasia is a chronic neurogenic disorder characterized by impaired relaxation of the lower esophageal sphincter (LES) and absent or ineffective peristalsis in the distal esophagus. This leads to a functional obstruction without a physical blockage, despite significant disruption of esophageal motility.EtiologyAchalasia is caused by degeneration of the myenteric (Auerbach's) plexus, specifically the loss of inhibitory ganglion cells that produce vasoactive intestinal peptide (VIP)...
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features01:24

Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features

Chronic bronchitis is a key phenotype of chronic obstructive pulmonary disease (COPD), characterized by airway-centered inflammation and mucus overproduction. It develops from long-term exposure to harmful particles or gases, most commonly cigarette smoke, which triggers a persistent inflammatory response.Cellular and Structural ChangesInflammation initially affects the large bronchi and later the smaller airways, with infiltration by immune cells, including neutrophils, macrophages, and...
Trachea01:22

Trachea

The trachea, commonly known as the windpipe, is a vital part of the human respiratory system. It serves as a passageway for air to travel between the larynx and the bronchi, allowing oxygen to reach the lungs. Let's explore its anatomical features, dimensions, layers of the tracheal wall, associated muscles, and the functions of its parts.
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...

Chronic Obstructive Pulmonary Disease II: Emphysema01:23

Chronic Obstructive Pulmonary Disease II: Emphysema

Emphysema, a major phenotype of chronic obstructive pulmonary disease (COPD), is characterized by irreversible destruction of alveolar walls and permanent enlargement of distal airspaces. Unlike chronic bronchitis, which primarily affects the airways, emphysema predominantly involves the lung parenchyma, where structural damage leads to airflow limitation.PathophysiologyIt most commonly results from prolonged exposure to cigarette smoke and other toxic gases, particularly cigarette smoke.
