Related Experiment Video
Updated: Aug 16, 2026

Chronic Intermittent Ethanol Vapor Exposure Paired with Two-Bottle Choice to Model Alcohol Use Disorder
Published on: June 23, 2023
Long-term use of benzodiazepines in participants with comorbid anxiety and alcohol use disorders
Timothy I Mueller1, Maria E Pagano, Benjamin F Rodriguez
1Southern Arizona VA Health Care System, University of Arizona Health Sciences Center, Department of Psychiatry, Tucson, Arizona 85723, USA. timothy.mueller@med.va.gov

Background:
Although the only widely accepted role for benzodiazepines in alcohol dependence is the treatment of withdrawal syndromes, they are frequently prescribed outside of this clinical setting. There is little empirical evidence to guide the rational use of benzodiazepines in the common clinical situation where anxiety disorders are comorbid with alcohol use disorders (AUD). Since January 1989, the Harvard Anxiety Research Program has naturalistically monitored the prospective clinical course of people with anxiety disorders, some of whom had a history of AUD. Earlier research showed that the use of benzodiazepines was not significantly associated with the presence or absence of a history of an AUD over the first year of follow-up. This report extends that investigation.
Methods:
Using standard parametric analytic methods, patterns of benzodiazepine use (routinely prescribed medication and as-needed [PRN] use) among participants receiving benzodiazepine treatment was prospectively examined over the course of 12 years. Differences in benzodiazepine usage patterns were examined in each year of follow-up between participants who did (n=120) and did not (n=425) have a new episode of AUD. Using proportional hazards regression analysis, benzodiazepine usage levels were examined as predictors of recovery and recurrence of AUD. Additionally, random-effects regression analyses were used to examine the patterns of benzodiazepine use before and after the onset of a prospectively observed episode of AUD.
Results:
Benzodiazepine usage levels remained stable for the full sample over the course of the 12 years. Benzodiazepine use did not distinguish participants who had a new AUD from those who did not. Over the 12 years of follow-up, participants who had an AUD used more PRN medication in years five to eight. This difference reached statistical significance but was not clinically significant. Benzodiazepine usage levels did not predict recovery or recurrence in AUD subjects. Neither the total dose nor the PRN usage of benzodiazepines was significantly associated with the onset of AUD, but when combined into a measure of any benzodiazepine use, a relationship between increased use and the onset of AUD emerged.
Conclusions:
For participants in the Harvard Anxiety Research Program with comorbid alcohol dependence and anxiety disorders, there was little association between the use of benzodiazepines and the occurrence of a new AUD. Neither was there a temporal relationship between the use of benzodiazepines and the onset of a new AUD. Whether or not this finding extends to a broader patient population or a group of people who present to addictions treatment awaits further investigation.

Related Concept Videos
 01:29
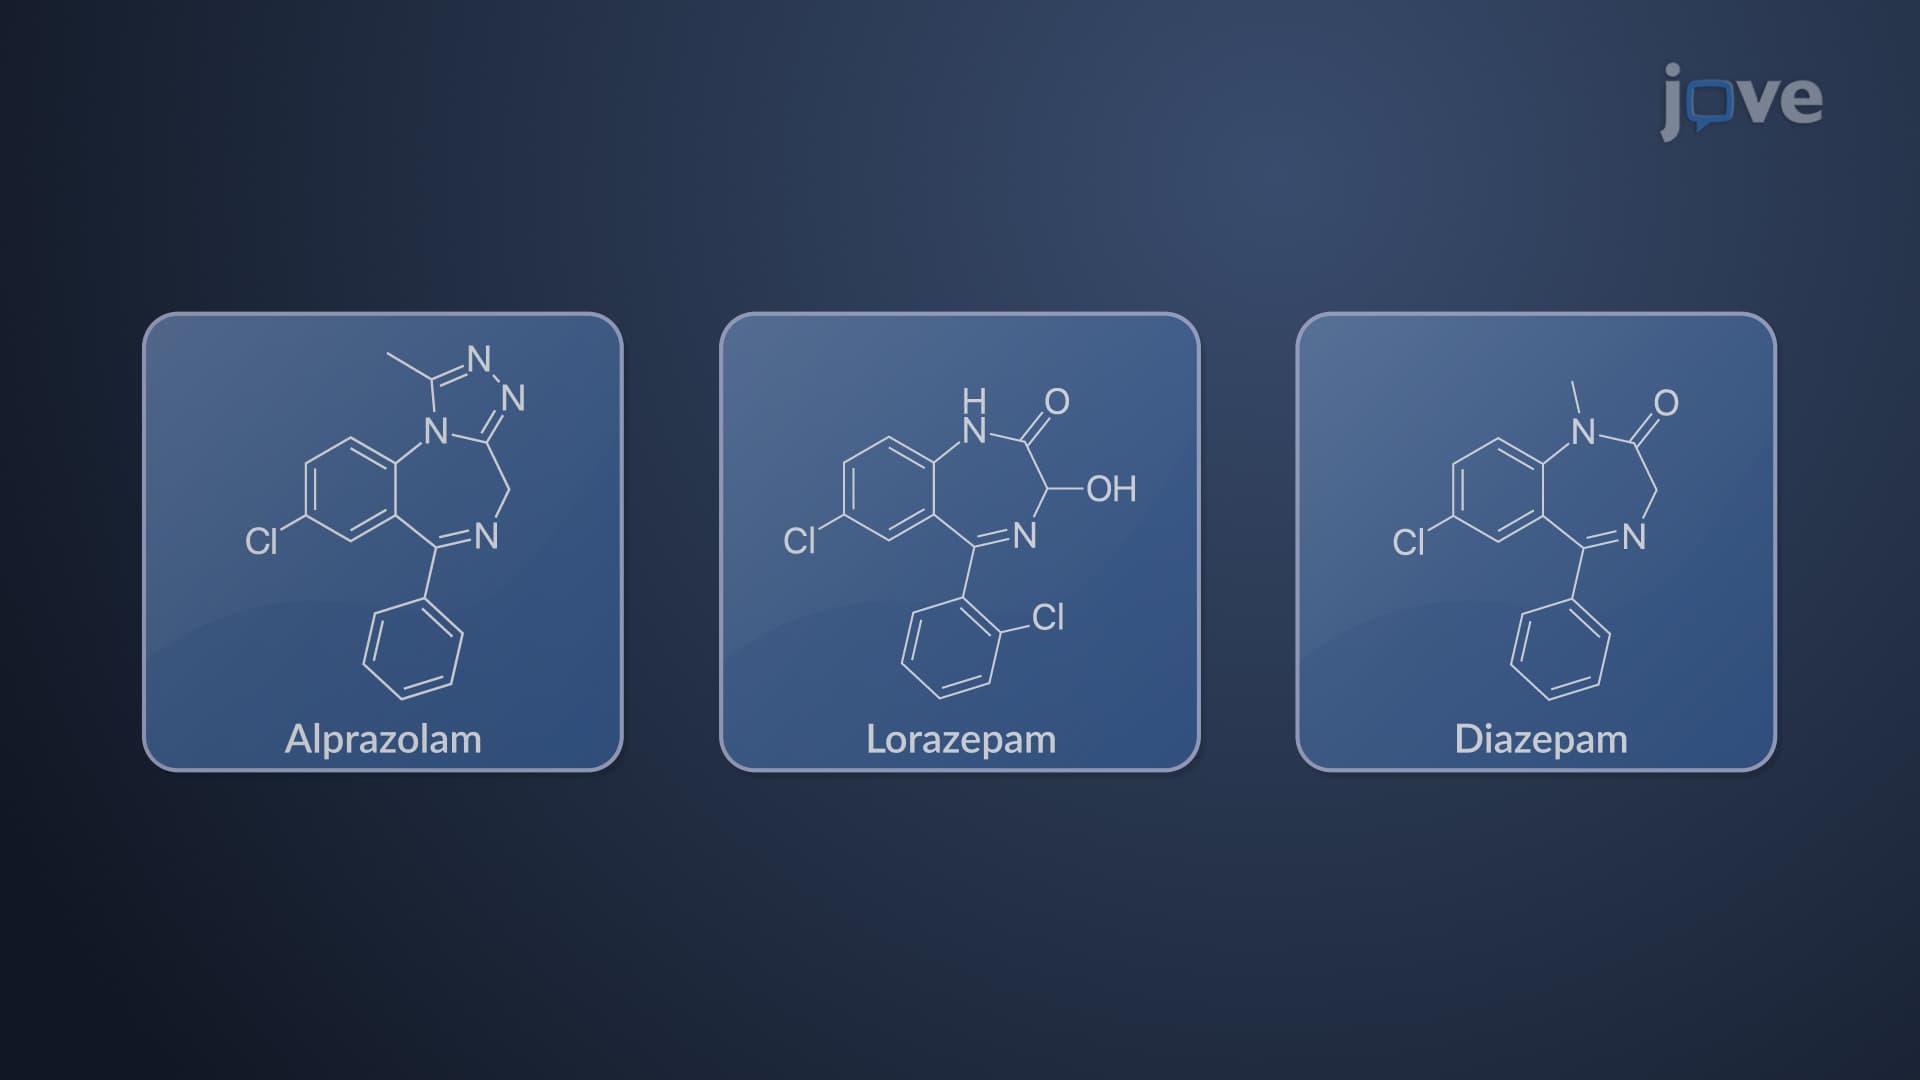
Anxiolytic Drugs: Benzodiazepines and Buspirone
 01:14
CNS Depressants: Barbiturates and Benzodiazepines
 01:19
Sedatives and Hypnotics Drugs: Benzodiazepines
Benzodiazepines work by enhancing the effects of the inhibitory neurotransmitter GABA. They bind to the GABAA receptor, increasing its affinity for GABA, which opens chloride...
 01:26
Anxiolytic Drugs: Overview
Primary Types of Anxiolytic Drugs
1. Benzodiazepines:
Benzodiazepines bind to the GABA-A receptor in the brain, enhancing GABA's interaction. This action reduces neurotransmission, effectively blocking anxiety-associated limbic circuitry.
 01:27
CNS Depressants: Alcohol and Nicotine
 01:28
Depressants
Alcohol is a common depressant that can induce a sense of relaxation and reduced inhibition at low doses. Contrary to its occasional...